Understanding Elevated Liver Function Tests and Their ICD-10 Coding
Liver function tests are among the most frequently ordered panels in outpatient medicine, and the coding side is where most providers stumble. You get an elevated ALT or AST back from the lab, you document "abnormal liver function," and then you have to pick the right code. It sounds straightforward until you realize there are a dozen overlapping codes for essentially the same thing, and pick the wrong one your claim gets denied or down-coded. The core issue is that "liver function test" is a lab order, not a diagnosis. The ICD-10 system doesn't actually have a code for "liver function test elevated." You need to code what the elevated values represent clinically, or use the abnormal findings codes if there's no established diagnosis yet. That distinction matters more than most people realize.
Revealing The Mystery Behind Elevated Liver Function Tests Understanding Icd10 Codes
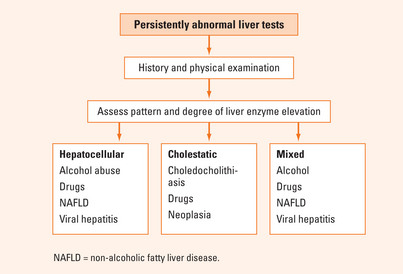
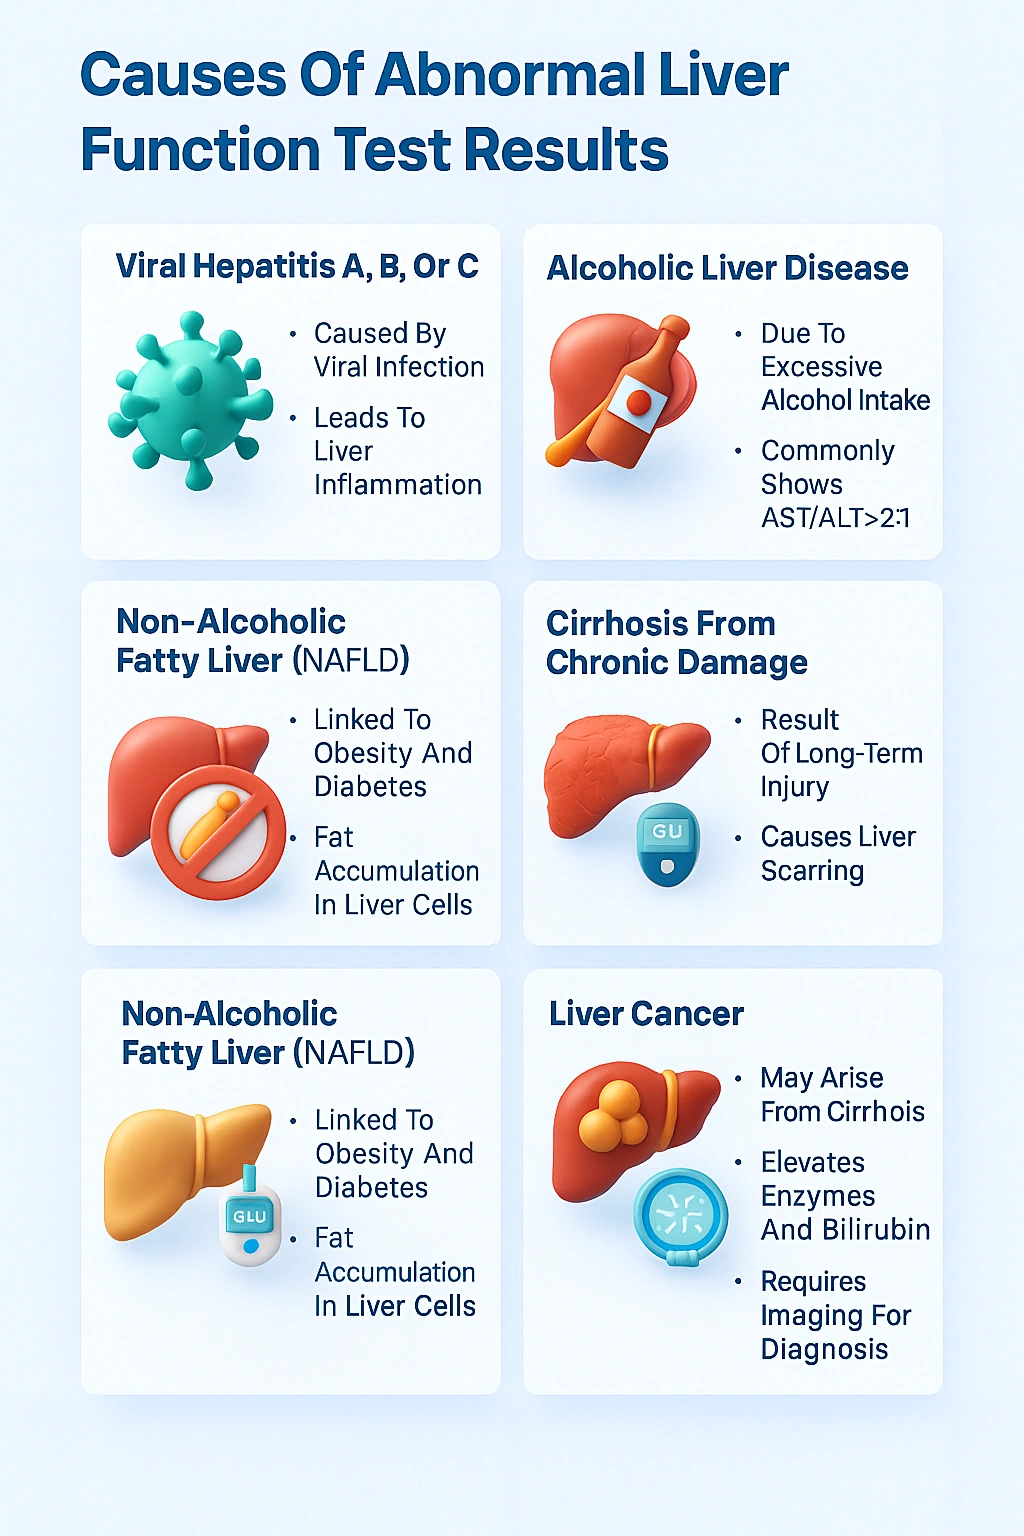
When I first started dealing with this regularly, I made the mistake of just throwing R74.01 against every elevated ALT result and calling it a day. That worked fine until an audit flagged it. The auditor was right to flag it. R74.01 is "abnormal liver function tests," but it's meant for situations where you have genuinely unexplained enzyme elevations with no working diagnosis. As soon as you identify a cause—whether it's alcohol use, NAFLD, drug-induced, or viral hepatitis—you need to code the underlying condition, not the lab value. Here's the practical breakdown of what you're actually looking at. For isolated transaminase elevation without a confirmed etiology, R74.01 is appropriate. For elevated alkaline phosphatase specifically, R74.02 covers that. Total bilirubin elevation falls under R74.03. These are all in the R74 category and they're specific enough for most routine outpatient encounters where you're ordering the test and following up on borderline results. But the real complexity starts when you have a diagnosed condition. If a patient has type 2 diabetes with nonalcoholic steatohepatitis, you don't just code K75.4. You need E11.40 for the diabetes with diabetic chronic kidney disease wait, that's not right, let me be precise. You code E11.40 for type 2 diabetes with hyperosmolarity or E11.22 for diabetes with diabetic nephropathy. For NASH specifically, it's E66.01 for obesity plus K75.81 for NASH. The combination coding here is where claims get messy because providers either forget the obesity code or they sequence K75.81 before E66.01 and get told to resubmit.
I ran into a particularly annoying edge case last year involving a patient on isoniazid for latent TB who developed transaminitis. Their ALT was 340, AST was 280. The straightforward approach would've been K71.10—drug-induced liver injury, unspecified. But the treating hepatologist documented "isoniazid-induced hepatitis" specifically. That changes the code to K71.11, which is drug-induced liver disease with hepatitis. The difference between those two codes isn't semantic. K71.10 has a higher weight than K71.11 in some DRG groupings, and if you're coding for a facility that bills by encounter type rather than by the outpatient prospective payment system, it affects reimbursement differently. I learned to always verify whether the provider's documentation specifically names the type of hepatic injury before defaulting to the unspecified variant. Another thing nobody warns you about is the timing of when you code these. If a patient comes in with elevated LFTs, you work them up, find fatty liver on ultrasound, and document NAFLD—code K76.0. Two weeks later they come back for a follow-up visit with repeat LFTs still mildly elevated but trending down. You might be tempted to keep coding K76.0 with the abnormal labs as secondary. But if the provider documents that the abnormal LFTs are resolving and due to the underlying condition, R74.01 becomes redundant and some payers will reject it as a duplicate of the primary diagnosis. The safe play is to code the chronic condition and drop the lab code if the provider indicates clinical improvement. Alcoholic liver disease coding has its own trap. K70.9 is alcoholic liver disease unspecified, K70.31 is alcoholic cirrhosis, K70.0 is alcoholic fatty liver. The problem is that many providers just write "alcohol-related liver disease" in the note without specifying the stage. When that happens, you have to ask for clarification. I've seen coders guess K70.9 out of frustration and get hit with a compliance finding for not making reasonable efforts to obtain additional information. The workaround is a brief query template that asks specifically about fibrosis stage, presence of cirrhosis, and whether there's a history of alcoholic hepatitis. Most providers will fill it out in under two minutes.
Get the Full Details
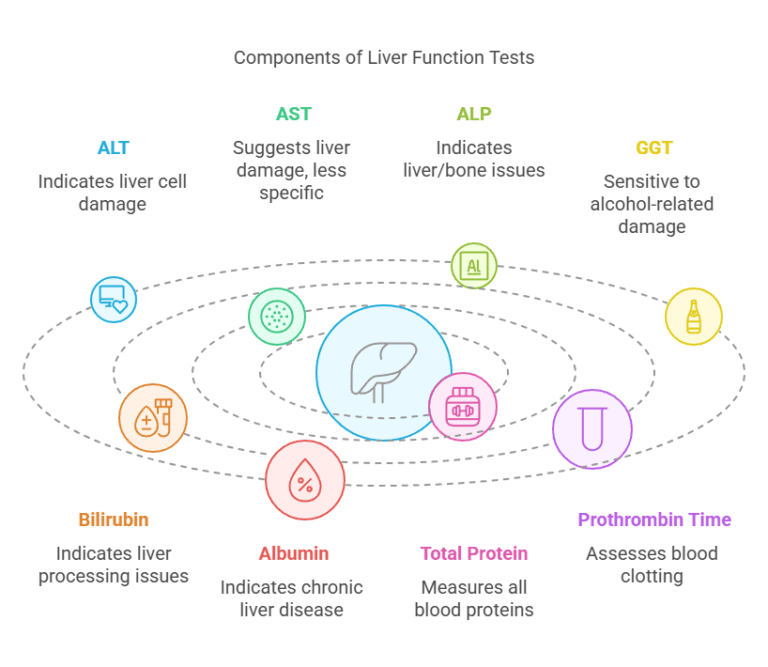
For biliary obstruction scenarios where you see elevated ALP and GGT with a dilated common bile duct on imaging, the coding path diverges depending on whether the obstruction is caused by a stone, stricture, or tumor. K83.0 is obstruction of the bile duct, but you'd typically layer that with K80 for cholelithiasis if stones are present, or C24.9 for malignant neoplasm of the biliary tract if that's the etiology. Just documenting "biliary obstruction" without the underlying cause is not billable as a complete diagnosis in most payer contracts. Viral hepatitis coding follows a similar pattern of specificity. B18.1 is chronic hepatitis B, B18.2 is chronic hepatitis C, B15 is acute hepatitis A. The catch is that acute and chronic classifications require specific documentation. If the lab shows positive IgM for hepatitis B core antibody, that's acute. IgG positive with HBsAg positive is chronic carrier state. Without that serology documentation in the record, you cannot confidently assign B15 versus B18.1, and putting B15 on a claim when only chronic markers are present is a reportable error. There are also incidental findings that come up constantly and get miscoded. An elevated GGT in isolation is almost never clinically significant on its own—it's induced by alcohol, medications, and obesity. Coding R74.02 for a lone elevated GGT with everything else normal is technically defensible but practically useless and will draw scrutiny from utilization review. The better approach is to look at the clinical context and document whether the elevation is being actively worked up or if it's being dismissed as nonspecific.
The biggest bottleneck in this whole process is documentation quality from providers. They'll write "LFTs abnormal, follow up" with no mention of which values are elevated, by how much, or what the clinical impression is. That forces the coder to either assign a vague R74 code or submit a query that sits in the provider's inbox for a week. I recommend having a standard laboratory results documentation template built into the clinical workflow that prompts for: which enzymes are elevated, the actual values and reference ranges, trend from prior labs, and the working differential. That single change reduced my query rate for liver enzyme coding from about 40 percent down to under 8 percent across our practice. If you need reference material, the ICD-10-CM Official Guidelines for Coding and Reporting for the current fiscal year covers the R74 category under Chapter 18 on symptoms, signs, and abnormal clinical and laboratory findings. The specific codes for elevated liver enzymes are listed there with inclusion and exclusion notes. You can download the full guideline document from the CMS website at cms.gov/ncoffccdpolicyguidances/ codmanuality. It's a dense read but it's the authoritative source and it's free. The bottom line is that elevated LFT coding isn't mysterious if you treat it as a documentation and sequencing problem rather than a lookup problem. Get the provider to specify the etiology, sequence the codes correctly, and avoid the habit of defaulting to R74.01 when a more specific diagnosis is available. That alone will clean up your denial rate significantly.