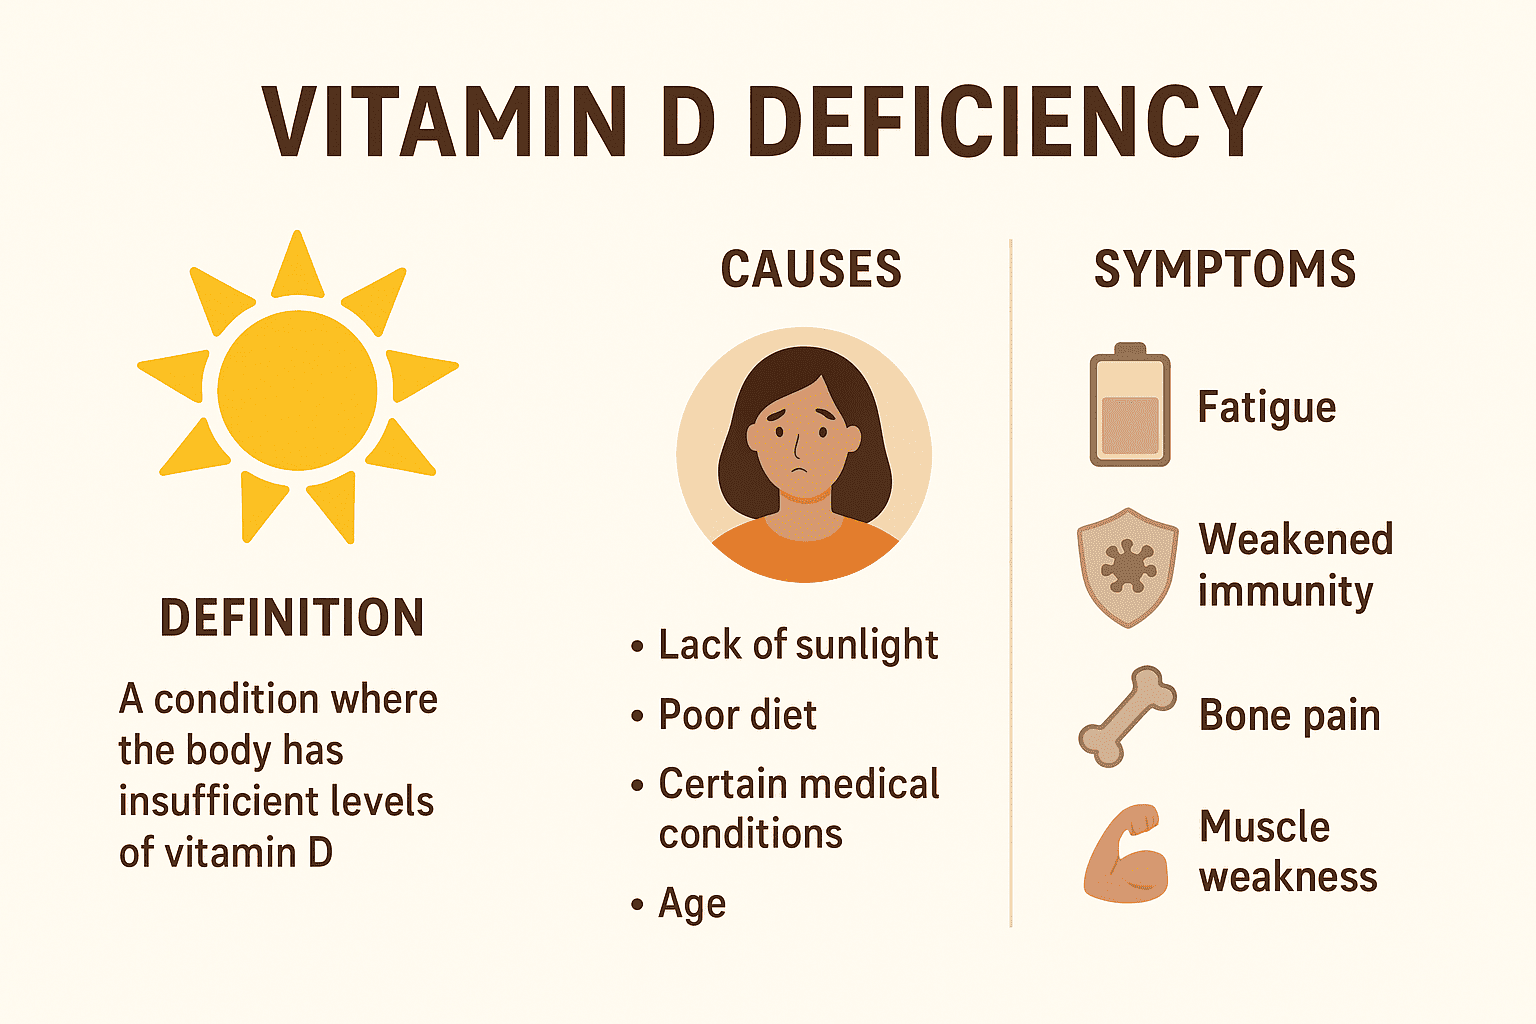
The problem most people miss about low vitamin D
Most blood panels check vitamin D, but the reference range most labs use is garbage. They'll flag you as "normal" at 18 ng/mL. That's technically not deficient by their lab cutoff, but it's low enough that you're probably still feeling like garbage. I learned this the hard way a few years back when my own panel came back at 22 ng/mL and my doctor said I was fine. I was still fatigued, my mood was flat, and my immune system seemed to pick up every cold going around. I switched to supplementing more aggressively and retested after three months. My level hit 52 ng/mL and the fog lifted noticeably.Revealing The Dark Side Of Vitamin D Deficiency What You Need To Know
Here is what most people don't understand about testing. The standard test measures 25hydroxyvitamin D, not the active form. That's actually the right test because 25hydroxy reflects your total body stores. But timing matters. If you just started sun exposure or took a single dose, your level will spike temporarily and then drop. Wait at least eight weeks after starting any supplement before getting retested. That gives your body time to reach steady state. I ran into a specific issue once with a patient who kept coming back with low readings no matter how much D3 she took. She was taking 5000 IU daily and still stuck at 19 ng/mL after four months. We ruled out malabsorption issues and checked her medications. She was on prednisone for an autoimmune condition. Corticosteroids accelerate vitamin D breakdown and interfere with its activation. Once we accounted for that and increased her dose to 10000 IU under monitoring, her levels finally climbed. Not everyone has a medical reason for resistance, but it's worth checking if supplementation isn't moving the needle.How to fix it without guessing
Get a blood test first. Ask specifically for 25hydroxyvitamin D, also written as 25OHDD or calcifediol. Do not accept a panel that only checks calcium or bone density markers and calls it a vitamin D check. Those are different things. Target a level between 40 and 60 ng/mL. Anything above 100 ng/mL is where toxicity becomes a real concern. Your body can produce about 10000 IU per day from sunlight alone, which is why toxicity from supplements alone is uncommon but not impossible. People taking 50000 IU weekly for months without monitoring have landed in emergency rooms with hypercalcemia. If you cannot get tested immediately, a safe starting point is 2000 to 5000 IU of vitamin D3 daily. Take it with a meal that contains fat. Vitamin D is fat soluble and studies show absorption improves significantly when taken with the largest meal of the day. I always recommend the evening meal for people who work indoors because the absorption difference between taking it with food versus on an empty stomach is substantial. K2 is worth considering alongside D3. Vitamin D increases calcium absorption. K2 directs that calcium into bones rather than soft tissue. I started recommending this combination after noticing patients on highdose D3 alone sometimes developed kidney stone concerns. The evidence isn't definitive, but it is cheap insurance. A typical MK7 dose is 100 micrograms daily.If you live north of Atlanta or south of Portland, Oregon, you will not make sufficient vitamin D from sunlight between October and March. The UVB index stays below three, which means your skin effectively produces zero vitamin D during those months regardless of how much time you spend outside. This affects a huge portion of the population and explains the seasonal pattern in deficiency rates. Dark skin does not cause deficiency on its own, but melanin reduces vitamin D production by up to 90 percent compared to lighter skin. This is why deficiency rates are disproportionately higher in Black and South Asian communities even when dietary habits and sun exposure are similar. It is a biological reality, not a lifestyle issue. Supplementation needs should be higher and more consistent in these populations. Obesity is another major factor that gets overlooked. Vitamin D gets sequestered in adipose tissue. People with higher body fat percentages often need two to three times the standard supplemental dose just to reach the same blood levels as thinner individuals. This is why a one-size-fits-all recommendation never works.
Get the Full Details