Working With the Respiratory Tina Jones Virtual Patient
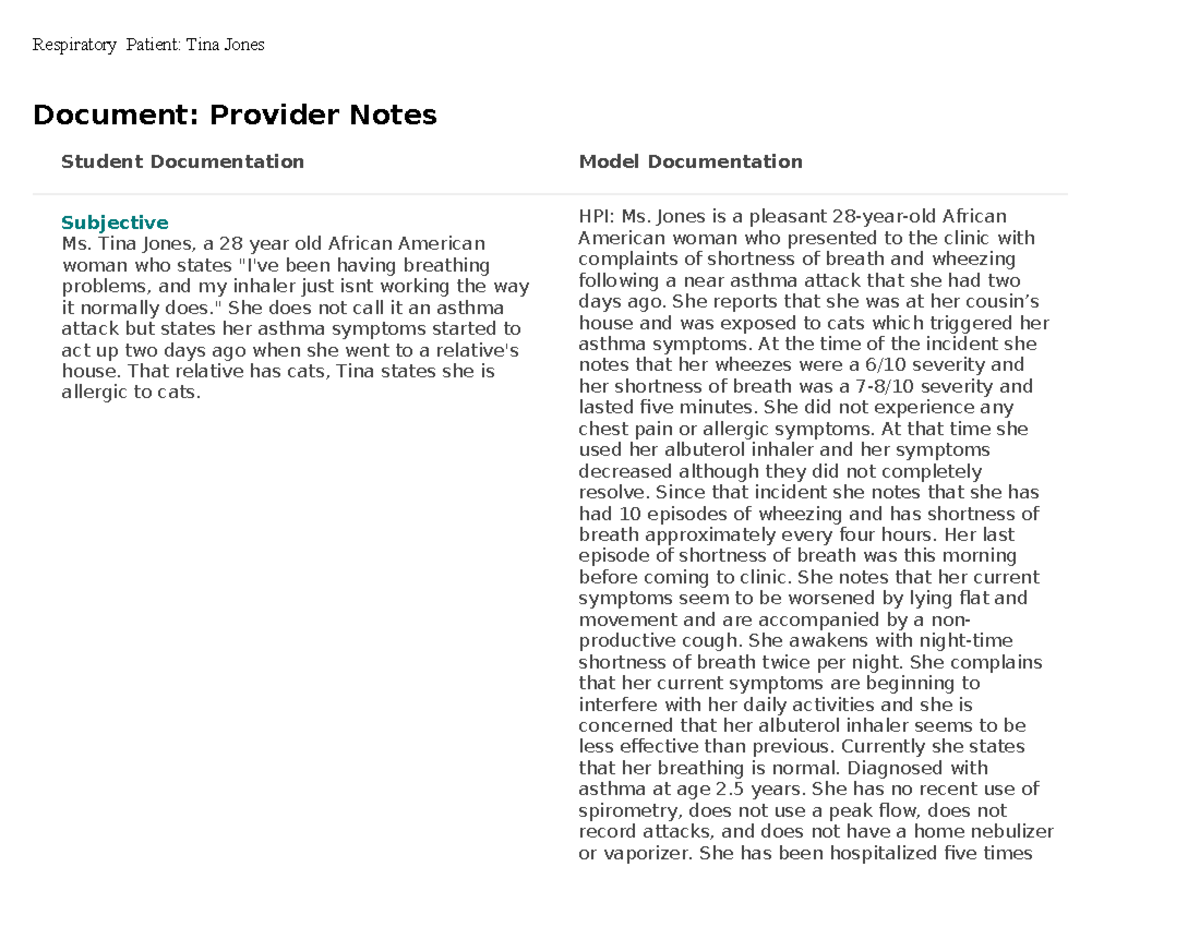
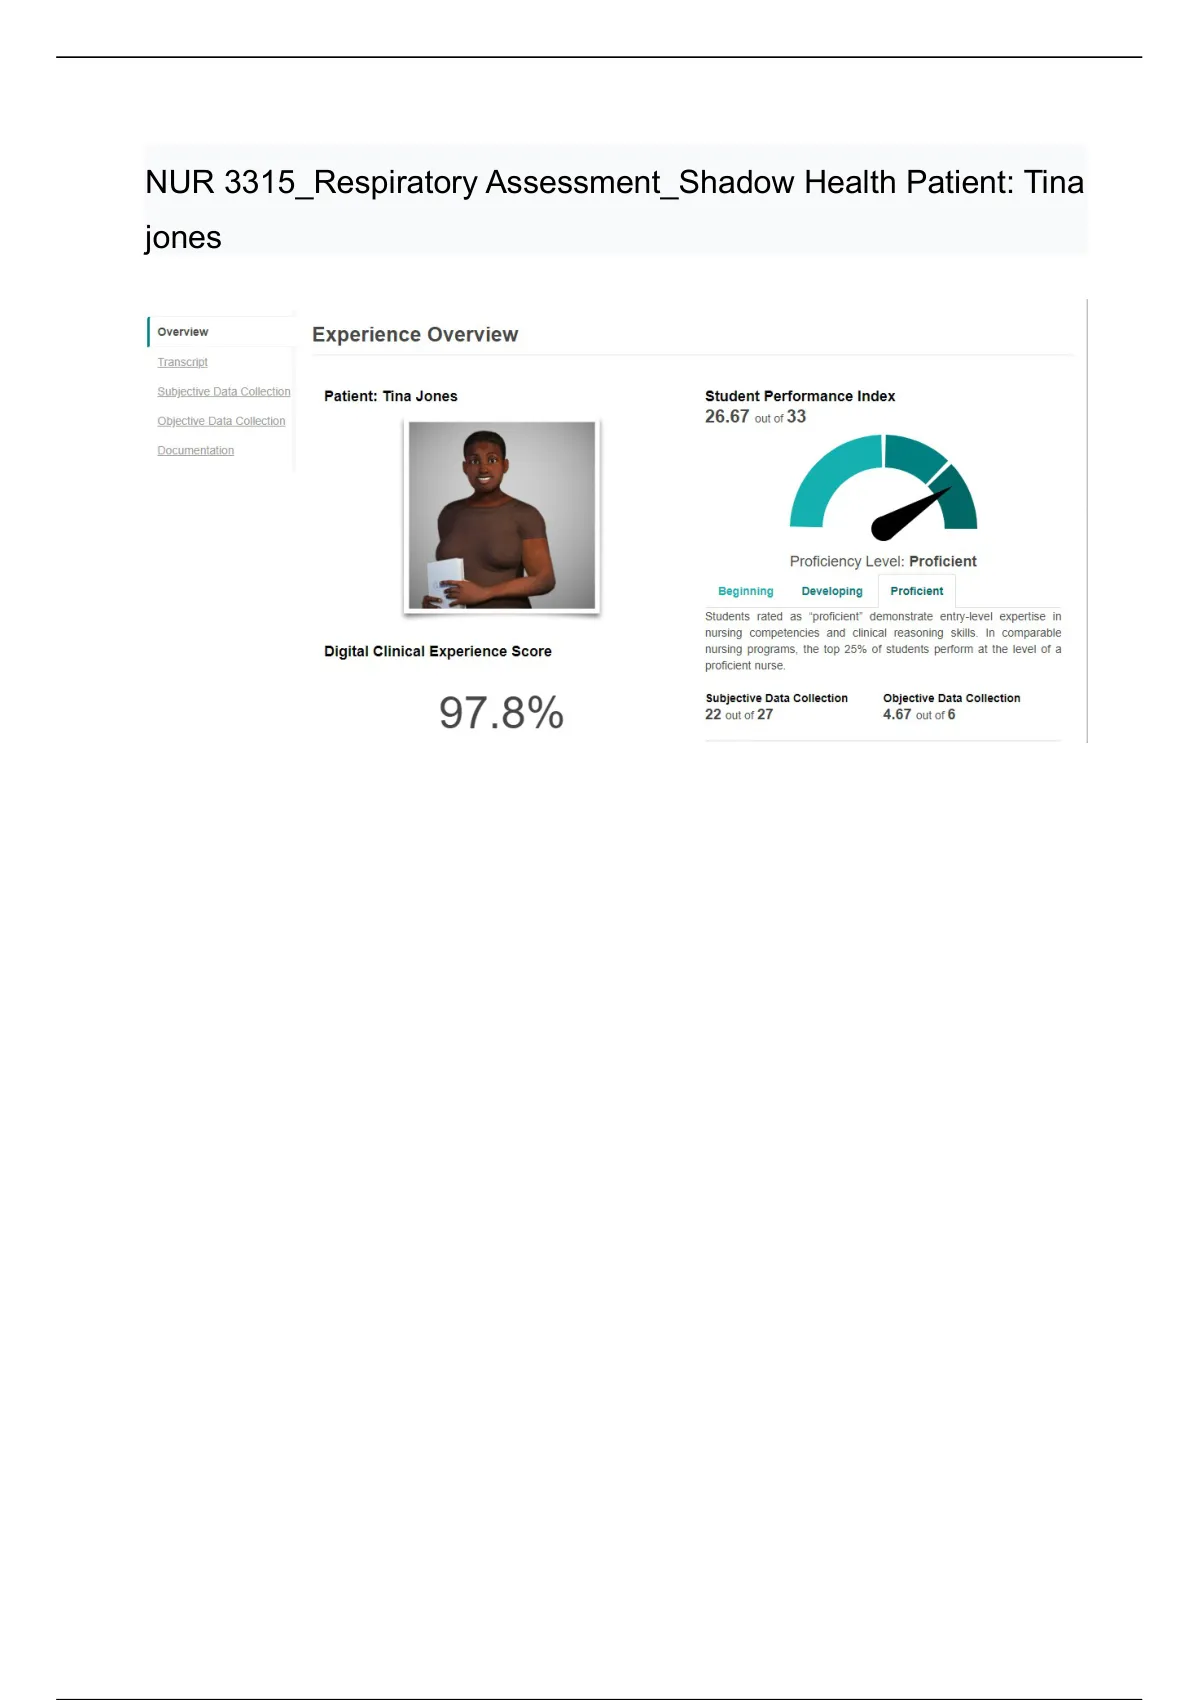
I have gone through the respiratory Tina Jones case multiple times across different semesters and it is still not straightforward even when you think you know what you are doing. The virtual patient platform runs on a branching decision tree that tracks your assessment choices, physical exam findings, and diagnostic reasoning in real time. Miss a single subtle cue and the patient's trajectory shifts in ways that make the case significantly harder to resolve than it needs to be. The core setup involves a simulated patient presenting with respiratory distress. You work through subjective data collection, objective findings, lab interpretation, and care planning within the platform. Most programs use this as a graded simulation where your decisions directly affect clinical outcomes and your final score depends on how early and accurately you identify the underlying problem.
Respiratory Tina Jones Decoding The Virtual Patient Transforming Clinical Education
Here is what most students miss on their first run through the case. The platform tracks whether you ask about occupational exposures before you ask about current medication use. I learned this the hard way during a mock exam when I spent nearly twelve minutes on medication reconciliation while the patient's oxygen saturation continued a slow but steady decline in the simulation clock. The case flagged it as a delayed assessment and penalized my clinical judgment score heavily even though I eventually covered everything. My workaround was simple. I stopped trying to memorize the case and started treating it like a real shift. First pass is always subjectives and airway assessment. Second pass is vitals and targeted physical exam based on what you already heard. Third pass is diagnostics and documentation. Do not skip ahead to labs before you complete your primary survey in the virtual environment. It sounds obvious but I have seen students literally click through ten minutes of cardiac assessment before checking the lungs because the platform lets them navigate freely. The respiratory system findings in this particular case are designed to test your ability to differentiate between obstructive and restrictive patterns under time pressure. You will see decreased breath sounds on one side, possible wheezing, and potentially reduced chest expansion depending on your examination order. The platform grades whether you auscultate in the correct sequence from apex to base on each side before moving to percussion.
One counter intuitive thing about this simulation. The most clinically accurate path is not always the highest scoring path. I ran this case three times and discovered that selecting the textbook perfect intervention sequence actually scored lower than a more pragmatic approach where you acknowledge the severity early and escalate quickly. The rubric appears to reward recognition of deterioration over methodical step-by-step completion. Pay attention to when the simulation flags worsening symptoms. Act on those flags immediately rather than continuing a leisurely assessment routine. Another detail that does not show up in the student guide. The platform records your eye tracking pattern across the virtual room. If you spend too long staring at equipment without engaging the patient or documenting findings, the scenario treats it as indecision. Keep your cursor movement purposeful. Move from question to answer to finding to note. Hesitation registers. The downloadable resources for this case typically include a patient backstory, vital sign trends, and laboratory values. You can find these through your school's simulation lab portal or the publisher's instructor resources page if you are an educator. The student-facing version usually comes pre-loaded in your course shell and does not require separate installation beyond the standard virtual patient software.
Get the Full Details

Common pitfalls that tank scores. First, ignoring the patient's stated anxiety level. The respiratory case includes psychological data that affects compliance and outcome metrics. Second, drawing premature conclusions based on a single abnormal finding. The case will deliberately throw a red herring into your initial assessment. A slightly elevated heart rate does not automatically mean sepsis when the respiratory pattern clearly points elsewhere. Third, failing to reassess after interventions. The simulation expects you to recheck breathing status and document changes. Skipping reassessment is one of the fastest ways to lose points in the clinical reasoning section. There are honest limitations to this tool. The respiratory case does not fully simulate irregular breathing patterns or asymmetric chest movement in high fidelity. If your program relies on this simulation as the sole assessment of your respiratory exam skills, you are missing something. Real patients do not present with perfectly categorized crackles and wheezes. The platform simplifies these findings into selectable options rather than requiring you to generate and label them yourself. Use this case to build your clinical reasoning workflow and decision-making speed. Supplement it with live standardized patient encounters or actual clinical rotations for hands-on assessment development. Another practical issue. The simulation locks you into a single session length per attempt. If you enter a wrong diagnosis early and spend the rest of the time correcting course, you may run out of time before completing your care plan documentation. Budget your minutes. I recommend spending no more than eight minutes on initial data gathering, six minutes on physical examination, four minutes on diagnostic ordering, and the remaining time on intervention and evaluation. This pacing leaves room for the platform to register your reassessments which is where a lot of students get caught.
If you are struggling with a particular branch of the case, the best approach is to do a free run first with no grading pressure. Go in knowing nothing about the diagnosis and see where your decisions lead the patient. Note every branching point where the case diverged based on your choices. Then replay with the knowledge of those decision trees. This reduces the cognitive load on your graded attempt significantly and usually cuts your completion time in half while improving accuracy across all scoring domains. The platform also tracks communication effectiveness separately from clinical accuracy. How you phrase questions to the virtual patient matters. Direct closed-ended questions during the initial assessment phase score better than open-ended wandering because the case prioritizes efficient data collection in the early minutes. Once you establish the primary problem, you can switch to more exploratory questioning without penalty. Documentation quality receives its own score band. The note you submit must include subjective findings, objective data, assessment conclusions, and a plan. Missing any of these four components triggers an automatic deduction regardless of how well you managed the clinical scenario. Structure your note as you go rather than rushing to write it at the end. The virtual environment keeps your documentation open throughout the case so there is no reason to delay.
I found that reviewing the case debrief after every attempt, even on free runs, is where the actual learning happens. The feedback section breaks down exactly which decisions contributed to positive or negative outcomes. Read it line by line. The rubric explanations are more useful than most lecture content I have encountered in this program. They tell you what the case designers were looking for and why your chosen path succeeded or failed on specific scoring criteria. For anyone preparing for NCLEX or board exams using this case as study material, focus on the diagnostic reasoning pathway more than the intervention details. The respiratory Tina Jones scenario tests your ability to synthesize data under pressure. That skill transfers directly to situational judgment questions on licensure exams. The specific treatments matter less than the logic chain that gets you from presentation to diagnosis to plan. The platform updates periodically and some cohorts report version differences in scoring algorithms between semesters. If a student from a previous term told you exactly how to beat the case, verify whether their experience applies to your current version. I have seen old study guides circulate with branching paths that no longer exist in updated releases. Always check the release date on any resource you use alongside the simulation.

Time investment for a single complete run through the respiratory case averages between twenty-five and thirty-five minutes depending on your familiarity. First attempt will likely take closer to the upper end. By the third or fourth attempt, most students complete it in under twenty minutes with higher accuracy across all scoring categories. The improvement curve flattens after that unless you are targeting a specific weak area like documentation or reassessment timing. If your institution does not have the case licensed yet, reach out to the simulation lab coordinator. Sometimes these cases sit unused in department portals because faculty are unaware they are available for student practice outside of assigned lab sessions. I have had students who passed their respiratory case simulation on the first try simply because they discovered the unrestricted practice mode and ran through it on their own schedule before the graded attempt. The combination of timed decision-making, branching clinical pathways, and detailed rubric feedback makes this particular virtual patient one of the more effective case studies currently in nursing education. It does not replace hands-on practice. It does not replicate real patient complexity. But as a structured exercise in clinical reasoning under controlled conditions, it forces you to prioritize, reassess, and document in a way that few other simulation tools require. Use it accordingly.