DevOps in healthcare is messier than most people expect
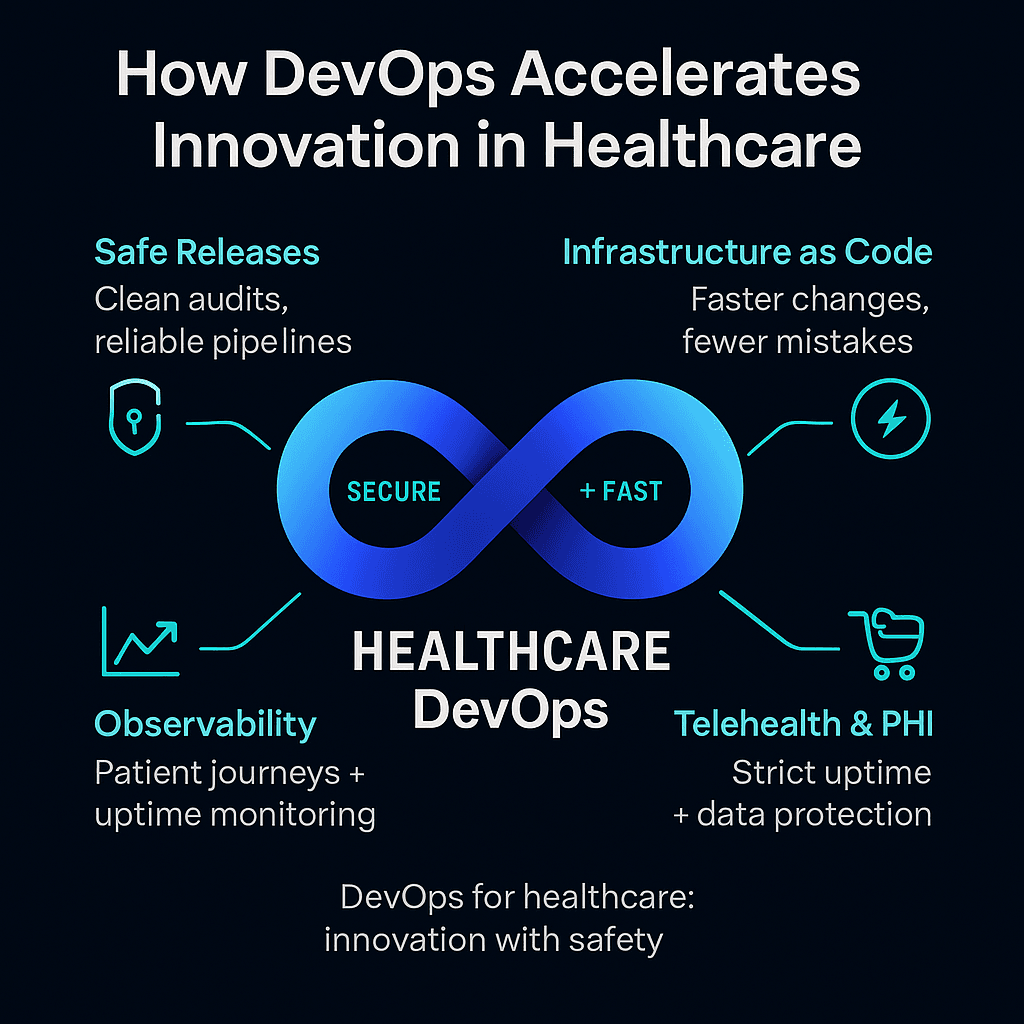
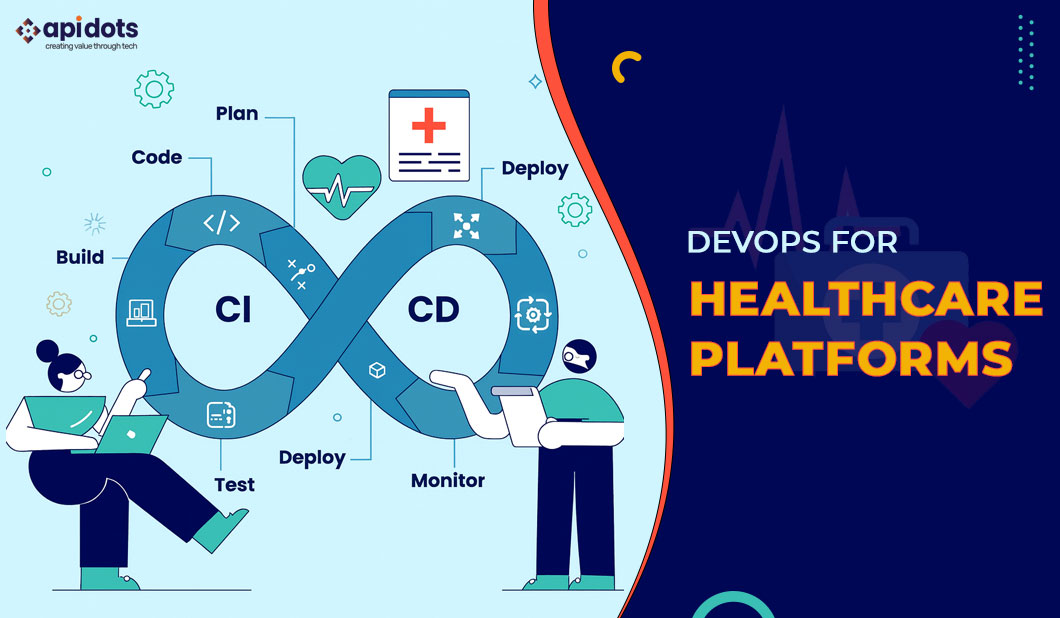
When I first started reading into how DevOps principles actually translate to clinical and hospital environments, I kept hitting walls. The literature is full of glossy case studies from tech-forward health systems, but the real work is far less photogenic. There is an online guide called Transforming Healthcare With DevOps that has circulated through various free repositories, and I spent considerable time going through it alongside trying to apply those ideas in a mid-sized regional health network. The resource is not a single unified book. It is a collection of articles, implementation notes, and workflow diagrams that have been pulled together and shared at no cost across several platforms. The core idea is straightforward: apply CI/CD pipelines, infrastructure as code, and monitoring practices to healthcare IT systems. That sounds simple. It is not. I found the most useful section early on, where it breaks down the difference between traditional waterfall deployments in hospitals and iterative DevOps-style releases. The key takeaway is that most healthcare organizations treat their application deployment process like a ceremonial event rather than an operational routine. You schedule it months out, you get change advisory board approval, you build a frozen window, and then you pray nothing breaks during the 4 AM rollout. DevOps flips that by treating deployments as everyday events.
How the guide structures its approach
The material is organized around five pillars: culture and collaboration, automation of testing, continuous delivery pipelines, infrastructure standardization, and feedback loops from clinical staff. Most free summaries stop there, but the deeper sections get into the actual mechanics. I spent the most time on the pipeline architecture diagrams for integrating EHR system updates, because that is where theory collides with reality. One thing the guide handles well is explaining why automated testing in healthcare is fundamentally different from automated testing in other industries. In a SaaS company, a failed test means a user sees a broken button. In a hospital, a failed test means a medication order could route to the wrong dosage. The guide walks through how to build staged testing environments that mirror production data without violating HIPAA constraints. This is where I ran into my first real problem. I was setting up a test pipeline that mirrored a cardiology application deployment, and I kept hitting issues with de-identified data that still carried enough metadata to create re-identification risk. The solution was not in the main text of the guide but in the appendix. I had to implement a tokenization layer that stripped NPI numbers, zip codes, and dates before the data ever touched the staging environment. Once that was in place, the pipeline moved from taking three days of manual prep to about forty-five minutes of automated setup.
What beginners miss about healthcare DevOps
The most common mistake I see people make is assuming that adopting DevOps tools automatically creates a DevOps culture. You can install Jenkins, Docker, and Terraform today and still have exactly the same siloed organization tomorrow. The guide touches on this but does not drive hard enough on the political reality of healthcare IT. Nurses do not care about your deployment frequency. Physicians will not adopt a new tool unless it reduces their click count, not increases it. I learned this the hard way when we pushed a fully automated CI/CD pipeline for a nursing documentation module and barely anyone used it because the release had not been vetted through the usual committee process that gave them trust. Another counter-intuitive point is that more automation does not always mean faster releases in healthcare. Sometimes the slowest step is the manual compliance review that must happen before code touches a production system. I worked with a team that reduced their deployment time from two hours to twelve minutes through automation, but the actual release cadence stayed at once a month because the compliance sign-off was the bottleneck. The fix was not more pipelines. It was getting compliance officers integrated into the feedback loop so they could review code changes incrementally rather than in bulk at the end.
Get the Full Details

The practical workflow from the guide
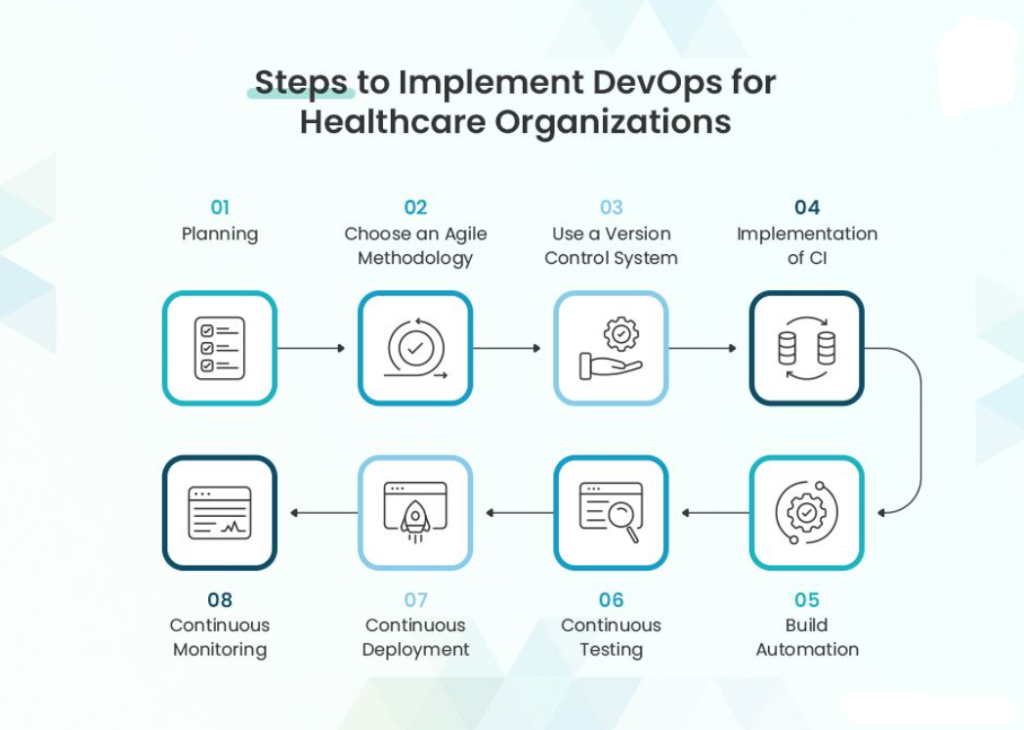
If you are working through this material on your own, here is the sequence that actually works in practice. Start by mapping every existing deployment process in your environment. I found that most teams had three or four hidden deployment paths that were undocumented and running on individual laptops. You cannot automate what you cannot see. Next, pick one low-risk application to serve as your pilot. Not the EHR. Not the billing system. A internal scheduling tool or a non-critical reporting dashboard. Build the pipeline end to end with automated unit tests, integration tests, and a rollback mechanism. The guide recommends using containerized environments for this, and I agree, but I would add that you should keep the container image registry behind your firewall from day one. Do not rely on public registries for anything near protected health information. Then expand. The guide suggests a quarterly rollout plan for additional systems. In my experience, this timeline is optimistic if you have legacy systems involved. A system built on older frameworks may require a strangler fig pattern where you gradually replace components rather than doing a full lift and shift. I have seen teams waste six months trying to containerize a monolithic .NET application that should have been rewritten instead.
Where the resource falls short
I need to be direct about the limitations. The free version of this guide covers the technical side reasonably well but underplays the regulatory complexity. It mentions HIPAA and FDA guidelines in passing, but it does not give you a compliance checklist you can actually use. If you are working in a regulated environment, you will need to supplement this with guidance from your legal and compliance teams, or you will find yourself at a dead end during audit season. The guide also assumes a level of engineering maturity that most healthcare organizations do not have. There are very few hospitals with a dedicated platform engineering team. Most are running on a skeleton crew of generalist sysadmins who are already handling patching, access management, and helpdesk escalations. Telling them to adopt GitOps and Kubernetes is not a realistic first step. Start with basic scripting and version control before you jump to orchestration. For organizations that are behind on this curve, I would recommend starting with the simpler sections of the guide and pairing that with basic training in Python scripting and Ansible before attempting the advanced pipeline configurations. There are also free resources from AWS and Azure that cover healthcare compliance patterns that complement what this guide provides.
What actually moves the needle
The section on feedback loops is the most valuable part of the material, even though it gets the least attention. The idea is that clinical staff need a direct channel to report deployment issues, and those reports need to flow back into the development pipeline within days, not quarters. I set up a simple Slack-based incident reporter that tagged the on-call engineer and automatically created a ticket in the tracking system. Within three months, our mean time to recovery dropped from roughly eight hours to under two for minor deployment issues. The guide does not mention something I think is important: the role of change management in maintaining these systems. DevOps in healthcare is not a one-time implementation. It is an ongoing operational model that requires dedicated staffing. If you treat it as a project with an end date, it will fail. The teams that kept this going were the ones that hired or reassigned people specifically to own the pipeline infrastructure rather than expecting existing staff to absorb it as a side responsibility. The free guide is a solid starting point for anyone looking to understand how DevOps applies to healthcare. It is not complete, and it will not walk you through every compliance gate you will hit, but the technical foundation it lays out is sound. The real work happens after you finish reading, when you are sitting in front of a legacy system that was never designed for automated deployment and trying to figure out which part to touch first.