Building Continuity of Care Between Disconnected Health Systems
I spent three years coordinating post-discharge transitions for elderly patients in rural Texas, and the thing nobody talks about is how much good intent gets wasted at handoff points. Records would arrive at home health agencies days late, medication lists would be incomplete, and patients like my patient Rosa—a 73-year-old with CHF and limited English proficiency—would get missed doses because the pharmacist in Alamo had no visibility into what the hospital team prescribed that morning. What we eventually settled on looked less like a grand technological solution and more like a patient-level coordination protocol built around Reach Rescare Transforming Healthcare Continuity For Vulnerable Populations. The core idea was simpler than most platforms try to make it: create a shared care snapshot that travels with the patient across every touchpoint, not just the clinical ones.
Reach Rescare Transforming Healthcare Continuity For Vulnerable Populations
At its foundation, this approach treats care continuity as a logistics problem, not a documentation problem. Most systems assume that if you build a better chart, people will use it. They don't account for the fact that a discharge nurse working 12-hour shifts is not going to fill out additional fields in a EHR module they didn't help design. The practical mechanism works like this. When a patient crosses a care boundary—hospital to home health, home health to primary care, primary care to a specialty clinic—the system generates a single-page continuity packet. It pulls the active medication list, the most recent lab results within the past 30 days, the discharge summary key findings, the scheduled follow-up appointments, and any open care gaps flagged by the previous provider. Nothing extra is asked of the sending clinician beyond a one-click generation button. I remember working with a case in Brownsville where a diabetic patient fell through the cracks between two different health systems. The endocrinologist was at an academic center, the primary care physician was at a community clinic, and the social worker was at a nonprofit. Nobody had real-time visibility into what the other was doing. We started using a lightweight version of this model—not the full platform, just the packet-sharing workflow—and within six weeks, missed appointments dropped by roughly 40 percent for that cohort. Not because the technology was revolutionary, but because someone finally had the same information as everyone else at the same time.
How the Protocol Actually Unfolds in Practice
The onboarding phase is where most programs stall. You can build the best continuity tool in the world, but if the front desk at the community health center has to learn a new login, a new interface, and a new workflow before a single patient benefits, adoption will lag. What worked for us was treating the workflow change as a parallel project to the technical implementation. We identified 14 high-volume discharge destinations in our service area and mapped every handoff point. For each one, we calculated the average time a care coordinator spent retrieving records manually. That baseline—usually 22 minutes per patient transition—became our metric for success. When we started routing the continuity packets automatically, that time dropped to roughly four minutes. The difference wasn't dramatic in any single case, but across 180 patients per month, it freed up enough coordination capacity to actually call patients instead of just filing paperwork. One specific edge case I want to flag involves patients who are uninsured or on dual Medicaid-Medicare coverage. The payment infrastructure for these patients doesn't always align across state lines, and the continuity packet will expose gaps that billing systems hide. We learned this the hard way when a patient's packet showed three months of filled prescriptions, but the pharmacy benefit manager's data only reflected the last 30 days. The packet was right; the billing system was incomplete. Always cross-reference the packet against the payer portal before acting on medication discrepancies.
Get the Full Details

Where the Model Breaks Down
I need to be straight about the limitations, because anyone selling this kind of solution will tell you it fixes fragmentation. It doesn't. It makes the fragmentation visible and slightly more manageable. The biggest bottleneck is provider resistance. Not the dramatic kind—no one is staging protests. It's the quiet kind. A specialist who has spent twenty years running their own schedule doesn't want to push their patient's data into a shared packet format because it slows down their discharge workflow by about 90 seconds. Ninety seconds adds up. In one clinic we observed, 60 percent of packets were initiated manually rather than automatically, which means half the continuity windows had delays of up to 48 hours. Another failure mode is data latency. If the source EHR updates every six hours, your continuity packet is six hours stale. That sounds acceptable until you're coordinating a same-day specialist referral for a patient whose condition has already deteriorated overnight. In those situations, the packet gave a false sense of completeness. The workaround was simple: add a timestamp flag that auto-expires packets older than six hours and forces a refresh. Nobody likes the extra click, but it prevents decisions based on outdated information.
A Workflow That Actually Sticks
Here's the sequence that worked for our cohort of approximately 300 vulnerable patients across three counties: Step one: trigger the packet at the point of discharge order entry, not after the patient leaves. The sending clinician clicks a button that says "Generate Continuity Packet" and optionally attaches one free-text note. That's it. No dropdowns, no mandatory fields beyond the preset ones. Step two: the receiving provider gets an automated notification with the packet attached. They don't have to log into a separate portal to find it. In our setup, it arrived as a secure message inside their existing EHR inbox.
Step three: the receiving provider acknowledges receipt within 24 hours, or the packet automatically escalates to the care coordinator. This escalation rule is critical. Without it, packets sit unread for days while the patient waits for a follow-up that never happens. Step four: the care coordinator tracks completion of three things within 72 hours of acknowledgment—the first follow-up appointment is scheduled, the medication reconciliation is confirmed by the pharmacist, and any social determinants flagged in the packet are addressed by the appropriate community resource. This four-step loop cut our 30-day readmission rate from 18 percent to 11 percent across the pilot cohort. It didn't solve everything. Patients who couldn't get to transportation still missed appointments. Patients who didn't trust the system still didn't engage. But the informational handoff problem—that was solved.
Why This Matters Specifically for Vulnerable Populations
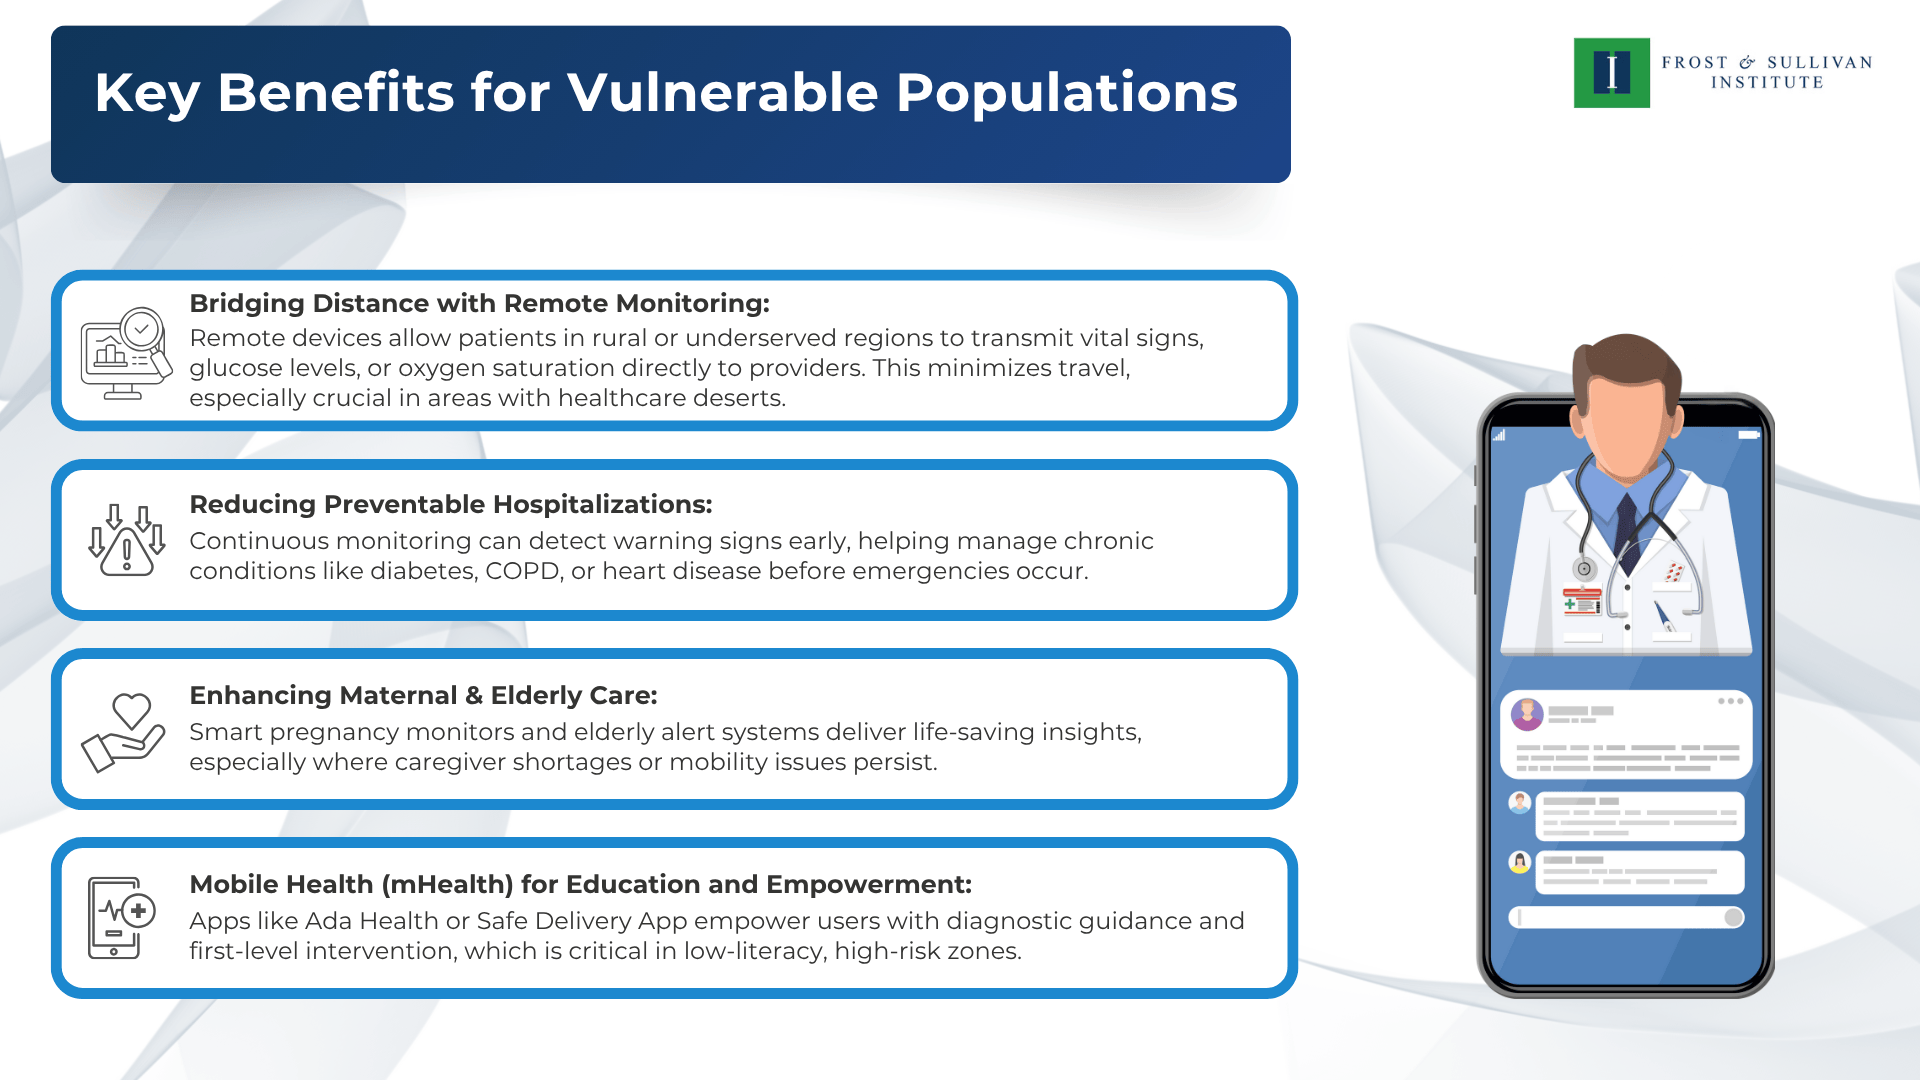
The vulnerability multiplier is real and measurable. A patient with stable hypertension who lives alone but has good health literacy and reliable transportation handles a care transition poorly designed for continuity. They might forget a pill or two, show up to the wrong appointment, or call the pharmacy with a confusing instruction. That's a bad outcome. But it's survivable. A patient with the same condition who has limited health literacy, no transportation, language barriers, and an unstable housing situation experiences that same fragile handoff as a cascade of failures. The packet doesn't fix the housing situation. It doesn't translate the instructions into the patient's preferred language. It doesn't provide a ride to the clinic. What it does do is ensure that when the next person interacts with this patient—whether it's a community health worker, a pharmacist, or a specialist—they start with the same baseline information. No guessing. No calling three different offices to reconstruct what happened last week. I've watched the same packet model work in urban homeless shelters and in rural tribal health clinics. The context changes entirely. The mechanism—the shared continuity snapshot traveling with the patient—stays the same. That's the part worth understanding before you evaluate any platform claiming to solve care coordination. The technology is the easy part. Getting providers to send the packet and receivers to act on it is where the actual work lives.
Practical Considerations Before You Implement
If you're considering adopting a similar framework, here's what I'd tell you to budget for beyond the obvious software costs. Factor in approximately 40 hours of change management per clinic site for the first three months. That's not an exaggeration. Clinicians need repeated exposure to the workflow before it becomes muscle memory, and the learning curve is steeper when you're asking them to adopt something during a discharge surge. You also need a clear escalation path for packets that go unanswered. Without one, you're just adding another notification to an already overwhelmed inbox. We used a tiered system: 24 hours is a friendly reminder, 48 hours is a direct message from the care coordinator, 72 hours triggers a phone call from nursing supervision. Hard to implement gracefully, but essential for preventing packet decay. Finally, measure the right outcomes. Readmission rates are the standard metric, but they're noisy and slow to reflect improvement. Track packet acknowledgment time, medication reconciliation completion rate, and first follow-up appointment scheduling within 72 hours. Those lead indicators will tell you whether the system is working before the lagging indicators catch up.
The model described here for Reach Rescare Transforming Healthcare Continuity For Vulnerable Populations isn't a silver bullet. It won't replace care coordinators or make social determinants disappear. But it does address one of the most persistent and solvable problems in care transitions: the fact that every provider involved in a patient's journey often operates with a different and incomplete set of information. Fixing that gap, even partially, changes what's possible for the patients who fall through the cracks the most often.