How Rapid Strep Testing Actually Works at a Pharmacy
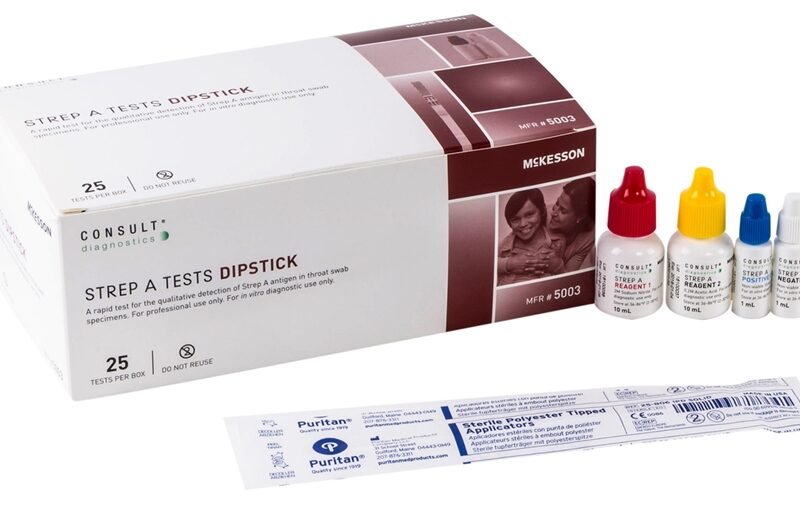
The process is straightforward in theory and mostly consistent in practice. You walk into a CVS with a sore throat, check in at the pharmacy counter, and wait. The pharmacist or tech takes a swab, presses it against the QuickVue+ or similar rapid antigen detection card, and waits five to ten minutes. A single line means negative. Two lines mean positive. There's no ambiguity for most patients, but there is plenty of room for error if the collection technique is poor. I ran tests at a pharmacy for about three years before moving into laboratory management, and I learned quickly that the biggest source of false negatives isn't the test kit itself—it's how the swab is collected. I had a patient who tested negative twice, both times reading clean in five minutes. We switched to a throat culture, and that came back positive for Group A Streptococcus. The issue wasn't the reagent. It was that the first two swabs barely made contact with the posterior pharynx. They dragged across the tongue and uvula instead. The bacteria live deep on the tonsillar surfaces and the back wall of the throat, not on the visible pink tissue at the front of the mouth. A proper swab requires firm pressure against both tonsillar pillars while the patient says "ah." Without that contact, you are testing saliva, not pus or exudate where the bacteria actually concentrate.
Rapid Strep Test At Cvs Speed Accuracy And What Patients Need To Know
Speed is the main selling point. A rapid strep test at CVS typically gives you results in about ten minutes from the moment the swab touches the card. Compare that to a throat culture, which requires a lab run and takes forty-eight to seventy-two hours for a final result. For patients who want to know immediately whether they need antibiotics, the rapid test delivers on that promise. The trade-off is that speed comes with slightly lower sensitivity compared to a culture, especially in certain populations. Accuracy varies by patient demographic and by the specific assay being used. Modern rapid strep tests at retail locations generally sit in the eighty-five to ninety-five percent sensitivity range. That means roughly five to fifteen percent of true strep infections will test negative. Specificity runs higher, usually above ninety-five percent, meaning a positive result is very likely correct. False positives are uncommon. False negatives are the real concern. Sensitivity drops further in pediatric patients. Children and young teenagers have higher baseline rates of asymptomatic strep carriage, and their bacterial loads can be lower at the moment of testing. Many clinical guidelines now recommend that any negative rapid strep test in a child under sixteen should be followed up with a throat culture. Adults with classic symptoms—a sudden severe sore throat, fever above one hundred and one, tender anterior cervical lymph nodes, and absence of cough—can often be treated based on a positive rapid test alone without a confirmatory culture. That is one of the more overlooked distinctions. Adults and children are not treated the same way in this context, and the testing algorithms reflect that.
Another factor that most patients don't consider is prior antibiotic use. If you have already taken even a single dose of amoxicillin or azithromycin before the test, the bacterial load on your tonsils drops significantly, and the rapid test may return negative simply because there is not enough antigen to detect. I once had a patient bring me a negative rapid test result after already finishing a three-day course of antibiotics prescribed by his primary care doctor the day before. We sent a culture anyway, and it was positive. The rapid test had been fooled by the partial treatment. If you are about to get a strep test, tell the pharmacist exactly what medications you have taken recently, including any leftover antibiotics you might have started on your own. The test itself detects group A streptococcal carbohydrate antigen through a lateral flow immunoassay. The swab is rubbed against a proprietary buffer that lyses the bacterial cells and releases the group A carbohydrate. That extract flows along the test strip, and if the antigen is present, it binds to labeled antibodies and produces a visible colored line. The entire mechanism is standard lateral flow technology, the same principle used in pregnancy tests and many at-home COVID tests. The chemistry is reliable when the sample contains adequate bacteria. It is not reliable when the sample is too dilute or contaminated with normal oral flora that interferes with the migration pattern. I encountered one edge case that still comes up occasionally. Some patients present with a very mild sore throat and minimal redness, making it nearly impossible to locate exudate or inflamed tissue on the tonsils. The swab comes back clean by visual inspection, and the test reads negative. But these patients can still have early strep pharyngitis before the bacterial load has peaked. In my experience, the workaround here is to either repeat the swab the next day when symptoms have progressed or skip the rapid test entirely and send a culture from the start. Cultures grow the bacteria overnight and can detect lower colony counts than an antigen test. If a patient is persistent about wanting answers and has moderate to severe symptoms despite a negative rapid test, a culture is the safer bet.
Get the Full Details
Cost and insurance are worth noting. Most CVS pharmacy locations offer strep testing through their MinuteClinic or walk-in wellness services, and many accept insurance directly. A rapid strep test without insurance typically runs between thirty and sixty dollars at retail locations, depending on your state and the specific service provider. With insurance, your copay is usually in the ten to twenty-five dollar range. Some plans require a referral or a prior visit to a primary care provider before the pharmacy will bill the claim. It varies by carrier and by state pharmacy regulations, so calling ahead and confirming coverage can save you an unexpected bill. Preparation for the test is minimal. Do not eat, drink, or chew gum for at least fifteen minutes before the swab, because food and saliva can dilute the sample and reduce sensitivity. Do not use throat sprays or mouthwash right before the test, as those products can kill surface bacteria and produce a false negative. If you are on liquid antibiotics or have just finished a course, mention it before the swab is taken. The results themselves are immediate for rapid tests. Positive results usually trigger a conversation about antibiotic options right then and there. Negative results in symptomatic patients often come with a recommendation to follow up if symptoms persist beyond forty-eight to seventy-two hours, since some strep infections progress slowly enough to miss the initial rapid test window. Pharmacists and nurse practitioners at these clinics are not diagnosing in the traditional sense—they are screening and referring when the clinical picture doesn't match the test result.
One counter-intuitive point that people rarely consider: a negative rapid strep test does not mean you are free of strep. It means the test did not detect antigen at a concentration above its threshold. The threshold is arbitrary and depends on the kit's validated cutoff. Some patients clear the antigen quickly even while the infection is still active, leading to that false negative scenario. A culture remains the reference standard precisely because it grows the organism rather than just detecting its proteins. If you have strong clinical suspicion and a negative rapid test, the culture is not an overreaction. It is the appropriate next step. The overall experience at a CVS is generally efficient. You can walk in without an appointment at participating locations, and the test takes less time than most coffee runs. The limitations are real but manageable if you understand them. The test is fast, it is reasonably accurate for obvious cases, and it is an effective triage tool. It is not a definitive rule-out in every situation, and it is not a substitute for clinical judgment when symptoms are atypical or when prior treatment may have altered the bacterial load.