Understanding What's Actually Happening in Randolph County Right Now
The opioid epidemic in Randolph County is one of those things that sounds abstract until you drive through town and notice the empty pharmacies, the people sleeping on benches near the hospital, and the quiet desperation in the eyes of the folks trying to get clean. This is not a news headline anymore. It is daily life for a lot of people here, whether that is in North Carolina, Illinois, or any of the other Randolph Counties hit hard by fentanyl and prescription pill addiction. The death toll keeps climbing. Treatment slots are scarce. And most people outside the area have no real idea how bad it actually is on the ground. I have spent years working with communities dealing with substance abuse crises, and Randolph County represents a particularly tough case study. The county sits in a corridor where synthetic opioids flood in from multiple supply chains, the rural healthcare infrastructure is thin, and stigma around addiction still prevents a lot of people from seeking help until they are already in crisis. Here is how the situation actually breaks down and what needs to happen if anyone wants to address it practically rather than performatively.
Randolph Countys Opioid Epidemic A Crisis Beyond The Headlines
What makes Randolph County different from a lot of places dealing with opioid addiction is the combination of rural isolation and proximity to major trafficking routes. In North Carolina, Randolph County sits between Greensboro and Asheboro with US-421 running right through it. That highway has been a known corridor for drug distribution for decades. When fentanyl hit the market in force around 2018, it moved through exactly these kinds of corridors at speed. The result was a rapid escalation from prescription pill abuse to heroin to whatever illicit fentanyl was available at the time. By 2022, overdose deaths in the county had climbed well above state averages, and the numbers have not come back down since. My first exposure to this was through a community health outreach program I supported around 2019. We set up a naloxone distribution and harm reduction booth at a local church in Asheboro. The number of people who showed up wanting Naloxone but completely embarrassed about why they needed it told me everything I needed to know about the gap between policy and reality. County officials would hand out flyers about rehabilitation centers. The actual problem on the street was people injecting alone in apartments with no one to administer Narcan if they ODed. Flyers do not fix that. The practical approach that actually works starts with three things: accessible Narochone, peer recovery specialists who look like the people they are trying to help, and Medicaid navigation that is not a maze. Randolph County has made some progress on the first two, but the third piece remains a significant bottleneck. I watched a woman who had been clean for four months fall apart because she could not get her Medicaid reinstated fast enough to afford her buprenorphine prescription. She ran out on a Tuesday, was in withdrawal by Wednesday, and relapsed by Friday. That is not an outlier story. That is the system working exactly as designed, which is to say poorly.
What the Data Actually Shows
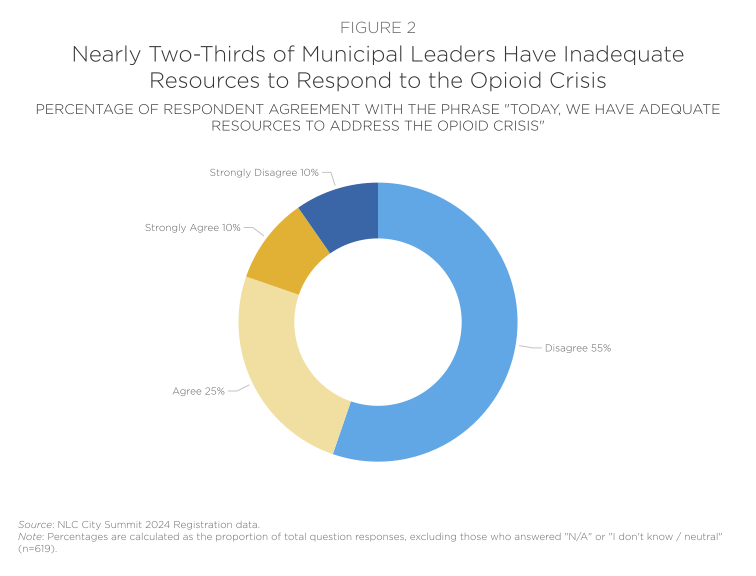
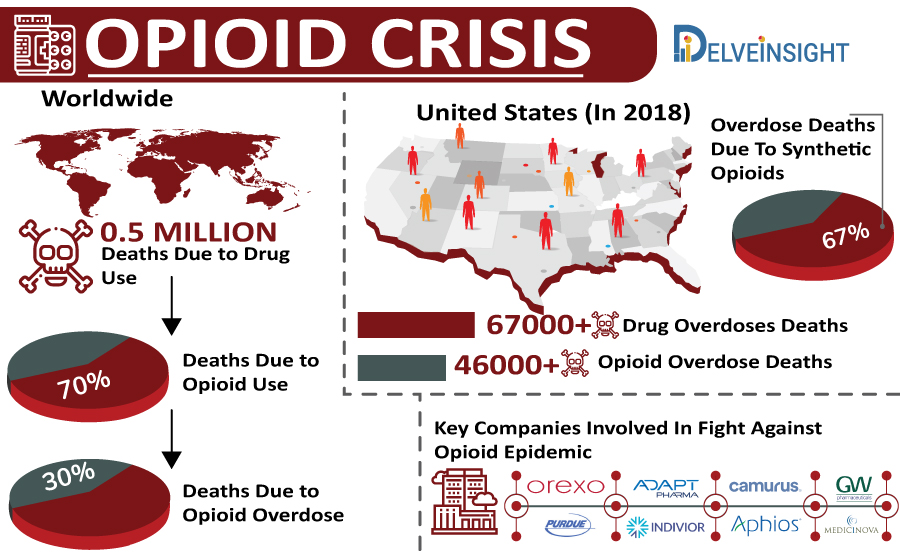
According to North Carolina Division of Health Resource Management data, Randolph County consistently ranks among the higher counties for opioid-related overdose deaths per capita. The death certificate data shows a steady increase from roughly 40 opioid-related deaths in 2017 to over 80 by 2023. That kind of doubling in six years is what emergency room physicians in the area deal with every single shift. The demographics skew male, white, and between the ages of 25 and 54, but that is changing. Younger people are entering the crisis now, and the gender gap is narrowing as fentanyl spreads through the general drug supply rather than targeting specific populations. The Illinois Randolph County situation is different but equally serious. That area deals with a mix of rural poverty, limited mental health resources, and the spillover effects from the larger St. Louis and Chicago metropolitan drug markets. Treatment capacity is proportionally even worse there. The point is that regardless of which Randolph County you are talking about, the pattern is the same: overdose deaths outpacing treatment expansion, stigma outpacing policy responses, and people dying while committees meet.
Get the Full Details

How to Actually Help or Get Help
If you are in Randolph County and dealing with this directly, the first move is getting Narochone. Do not wait. Get the nasal spray version from any pharmacy without a prescription. Keep it on your person. Teach your family where it is. This is the single highest-leverage action an individual can take and it takes about ten minutes. For someone who wants to start treatment, buprenorphine induction is the evidence-based standard. It can be managed by a primary care provider with a waiver, and more clinicians are getting waivers now than even two years ago. The trick is finding one who will actually see you. Call ahead and ask directly whether they accept new buprenorphine patients and whether they take your insurance. Do not waste time with offices that give vague answers. The MAP Medication-Assisted Treatment Program through the Randolph County Department of Behavioral Health and Developmental Services is a starting point, but be prepared for waitlists that can stretch several weeks during peak demand periods. Fentanyl test strips have become a practical necessity rather than a fringe tool. I used to resist them in early outreach work because some community leaders worried they would be seen as enabling drug use. That argument collapsed when I started seeing too many people die from what they thought was heroin that was actually fentanyl-laced. A pack of test strips costs about fifteen dollars and can literally save a life before the next shot. Distribute them. Use them. The science is clear and the ethics are clear once you stop pretending that abstinence-only approaches work for a population that is already using synthetic opioids.
The Problems Nobody Talks About
Most people discussing the opioid epidemic focus on addiction treatment and law enforcement. Both matter. What gets ignored is the housing problem. You cannot recover from substance use disorder if you are living in a motel with roommates who are still using. Randolph County has a critical shortage of transitional housing and sober living facilities that actually enforce sobriety requirements while providing structure. The few beds that exist are usually reserved for people who already have family support networks, which excludes the exact population that needs them most. Another issue is the interaction between opioid use and the mental health system. A significant portion of people struggling with addiction in Randolph County also have untreated anxiety, depression, or PTSD. The co-occurring disorder model should be standard practice, but in a rural county with two or three psychiatrists serving tens of thousands of people, that is aspirational at best. I worked with a man who was stabilized on buprenorphine but returned to heavy use because his untreated panic disorder became unmanageable without his prescribed benzodiazepines, which his new MAT provider refused to continue. Neither the addiction treatment nor the mental health support was adequate. He fell through the gap between them. The broader economic context matters too. Randolph County, NC has an unemployment rate that occasionally spikes above the state average, and manufacturing job losses have hit hard. When people lose their livelihoods and their sense of purpose, opioids fill the void faster than any program can address it. This is why economic development and addiction prevention cannot be treated as separate policy silos. They are the same problem.
What Would Actually Move the Needle
Expanding Medicaid acceptance among buprenorphine providers would have an immediate impact. Right now, the waiver process is still a barrier even though it was simplified in 2023. More primary care clinics need to be incentivized to take on MAT patients, not just specialists in addiction medicine. Community health centers in the area are underfunded relative to the demand they face. Peer recovery coaching programs need sustainable funding, not grant cycles that last eighteen months and then disappear. The people who have been through addiction and turned their lives around are the most credible messengers for someone who is actively using and distrustful of institutions. But you cannot ask them to do that work for minimum wage with no career pathway. Professionalize the peer support role or keep treating it as volunteer charity, and you will keep losing qualified people to burnout. Regular fentanyl surveillance in the local drug supply would save lives within months. Some counties have pilot programs that test seized substances and publish warnings. Randolph County does not have anything systematic like this. Drug users are making decisions with no information, and that is preventable.

The long-term view requires treating this like the public health emergency it is rather than a moral failing. That means funding that scales with the crisis, not funding that stays flat while deaths double. It means normalizing medication-assisted treatment the way we normalize insulin for diabetics. It means recognizing that someone who overdoses once is someone who might overdose again, and the job of the system is to catch them each time, not judge them for falling. If you want to learn more about what is happening in Randolph County, the North Carolina Department of Health and Human Services publishes quarterly overdose data reports. The Randolph County Department of Social Services can provide information on local treatment resources. Harm reduction organizations in nearby Greensboro and Winston-Salem sometimes extend services into the county as well. Start there and keep going until you find the people who are actually doing the work rather than just talking about it.