Working With Blood Type Inheritance in Practice
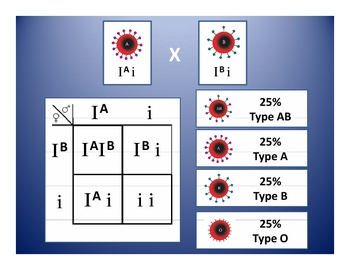
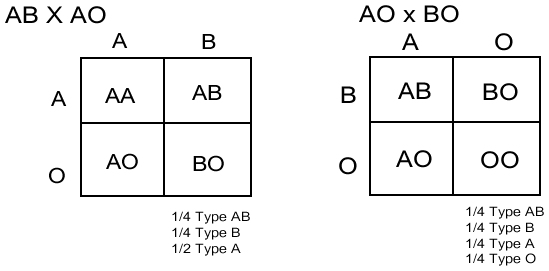
The ABO system works because you inherit one allele from each parent, and those alleles combine to determine your phenotype. The three main alleles are A, B, and O, where A and B are codominant and O is recessive. When I first started running these calculations for clients who needed paternity screening estimates or transplant compatibility previews, I quickly learned that the Punnett square approach is fast but easily misleading if you don't account for the underlying genotypes first. Here is how the basic method works. Take two parental genotypes, lay them out on a grid, and fill in the possible combinations. A parent with genotype AO crossed with a parent who is BO gives you four cells: AB, AO, BO, and OO. That means the possible blood types among offspring are A, B, AB, and O, each at roughly 25 percent probability. That part is straightforward. The trouble starts when people skip the genotype step and go straight from phenotype to the square. I had a case last year where a client brought me a mother typed as A and a father typed as B, asking what blood type their child could be. She assumed the answer was just A, B, AB, or O at equal odds. The problem is that both parents could carry hidden O alleles, or one could be carrying a cis-AB allele, or the typing itself could have been done with a weak subgroups that standard reagents miss. I ran the standard square first, which gave the four expected phenotypes. Then I asked for the parents' red cell and serum testing details. It turned out the mother was actually a weak A subgroup, A2, which changed the predicted distribution of A subtypes in the offspring and flagged a potential discrepancy for any future transfusion scenario. The workaround was running a confirmatory panel with anti-A1 lectin and checking the father's secretor status before finalizing the report. Without that extra step, the family would have walked away with an incomplete picture.
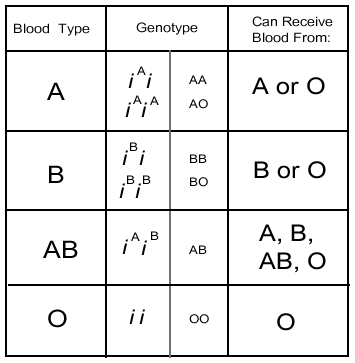
One common mistake is treating blood type as a simple dominant-recessive trait across the board. A and B are not simply dominant over O in the way people imagine. They are codominant with each other, and O is recessive to both. That means a person with type AB has the genotype AB, not AA or BB, and they can only pass A or B to their children, never O. Another mistake is assuming that two O parents cannot have an AB child. Under normal circumstances that is correct, but rare exceptions exist due to cis-AB alleles or the Bombay phenotype, both of which break the standard Punnett square assumptions entirely. The Rh system adds another layer. The D antigen is the main driver of positive or negative status, and it follows a simpler dominant-recessive pattern. A parent who is DD will always pass a D allele, while a parent who is Dd passes D or d with equal chance. Two Dd parents can produce a dd child, which is Rh negative, at about a 25 percent rate. People often forget that Rh typing is separate from ABO typing, and combining them without clear notation leads to garbled predictions. I always write the full genotype, such as AO Dd, before drawing any square, because mixing the systems visually creates errors faster than doing the math twice. Edge cases are where this method shows its limits. Chimerism, recent bone marrow transplants, and certain leukemias can alter blood typing results without changing the person's underlying genetics. I once worked with a patient whose routine ABO type came back as a mix of two patterns after a transplant. Running a Punnett square on those results would have produced nonsense. The fix was using buccal swab DNA for genotyping instead of relying on serology, which is slower and more expensive but avoids the trap entirely. If you are doing this for legal or medical decisions, serology alone is not always enough.
There is also the issue of gene frequency in different populations. In some Asian populations, the O allele is extremely common, which shifts the probability distributions compared to European groups where A and B are more frequent. If you are using a generic Punnett square without considering population allele frequencies, your percentage estimates can be off in ways that matter for genetic counseling. A quick lookup of regional allele frequencies takes about five minutes and usually changes the confidence intervals enough to be worth the effort. If you want to practice this yourself, there are free online calculators that handle ABO and Rh together. I typically use the ones that let you input full genotypes rather than just phenotypes, because the phenotype-only entry fields force assumptions that are often wrong. The calculators do not replace careful genotyping, but they cut the manual square work from around ten minutes per case to about a minute once you have the right inputs. The takeaway is that Punnett squares for blood type are a useful starting point, not a final answer. They work well for basic classroom problems and quick family planning estimates. They break down when you encounter weak subgroups, cis-AB, Bombay phenotype, chimerism, or transplant-related typing changes. In those situations, you need molecular testing or at least a more complete serological workup. Knowing when to stop at the square and when to dig deeper is the difference between a guess and a reliable result.
Get the Full Details