Why Probiotics Make You Feel Worse Before They Help
I started taking probiotics on a recommendation from a functional medicine practitioner after dealing with chronic bloating and irregular bowel movements for years. Within 48 hours, I was gassed, achy, and running to the bathroom every hour. I almost wrote off the entire category as pseudoscience before realizing I had made several fundamental mistakes that anyone new to this should avoid. The common explanation you'll find online is the Herxheimer reaction, or die-off. The theory goes that when beneficial bacteria are introduced, they kill off harmful organisms faster than those pathogens can release their toxins, triggering flu-like symptoms. This oversimplifies what's actually happening. The reality involves several distinct mechanisms that operate differently depending on your baseline gut state. The primary culprit in most cases is bacterial fermentation activity in parts of the intestine where it shouldn't be happening at full capacity. When you introduce concentrated strains of Lactobacillus or Bifidobacterium, those organisms begin metabolizing available carbohydrates and producing short-chain fatty acids, hydrogen, carbon dioxide, and sometimes trace amounts of other byproducts. If your small intestine already has a compromised mucosal barrier or slow transit time, this sudden increase in fermentation creates osmotic pressure and distension that feels unmistakably awful. Bloating, cramping, and loose stools are the standard triad.
A secondary mechanism involves competitive exclusion dynamics. The introduced strains displace resident microbes that have already adapted to your particular gut environment. This displacement triggers immune signaling through toll-like receptors and stimulates local production of cytokines, particularly IL-8, which can increase intestinal permeability transiently. You feel this as general malaise, brain fog, and sometimes low-grade fever. It's not die-off. It's your immune system noticing that the neighborhood just got a new tenant.
Strain-Specific Reactions That Most Guides Ignore
Not all probiotics produce the same side effect profile. This is the single most important factor that beginner guides consistently underplay. Lactobacillus acidophilus and Lactobacillus plantarum tend to be better tolerated because they are native to the small intestine and their metabolic byproducts are relatively mild. Lactobacillus casei, on the other hand, is more likely to trigger histamine release in sensitive individuals because certain strains produce histidine decarboxylase, an enzyme that converts dietary histidine into histamine directly in the gut lumen. If you have any degree of histamine intolerance or DAO enzyme deficiency, taking a L. casei-dominant probiotic is like pouring gasoline on a smoldering fire. Bifidobacterium infantis is generally well-tolerated and has the most robust clinical evidence for IBS-related symptoms. But Bifidobacterium lactis can cause significant gas production in people who also have underlying SIBO because it ferments rapidly in the small bowel where carbohydrates shouldn't be sitting long enough to be fully broken down. The strain designation matters more than the genus. Lactobacillus rhamnosus GG has a completely different side effect profile than Lactobacillus rhamnosus HN001. If a product label just says "Lactobacillus" without the specific strain identifier, you are buying a lottery ticket and hoping you don't win the wrong prize.
Get the Full Details

Practical Protocol That Actually Works
Start with a single strain at half the recommended dose for two weeks. If you tolerate that, move to the full dose. If you do not tolerate that, switch to a different strain entirely rather than pushing through the symptoms. Most people push through because they've invested money in the product and want to believe it's working. It isn't working if your quality of life has dropped. Pushing through just extends the duration of your discomfort. I spent three weeks cycling through five different probiotic formulations before I landed on one that didn't make me miserable. The first batch was a broad-spectrum product with 16 strains at 50 billion CFU. That was the mistake. The second was a single-strain L. plantarum 299v at 10 billion CFU and I took the full dose immediately. That also made me sick. The version that finally worked was Saccharomyces boulardii CNCM I-745, a beneficial yeast probiotic that doesn't colonize the gut but passes through and modulates immune function and pathogen adhesion. I started at 250mg every other day for a week, then moved to daily. Zero gastrointestinal distress. The bloating I'd been managing with diet alone improved within three weeks of consistent use. S. boulardii is worth considering specifically because it sidesteps the bacterial fermentation problem entirely. Yeast-based probiotics don't compete with your native bacteria in the same way and they don't produce the same gas byproducts. They are not a cure-all, but they are a reliable fallback when bacterial probiotics fail.
When Probiotics When Gut Health Backfires Why Some People Feel Sick After Taking Them Signals Something Deeper
If symptoms persist beyond two weeks on a low dose of a well-tolerated strain, you likely have an underlying condition that probiotics alone cannot resolve and may actually aggravate. Small intestinal bacterial overgrowth is the most common misdiagnosed condition in this space. People with SIBO already have excessive bacteria in the small intestine. Adding more bacteria on top of that is analogous to adding water to an already overflowing sink. The result is not improvement. It is increased distension, altered motility, and worsening symptoms. The clinical marker for SIBO is a positive glucose or lactulose breath test showing an early rise in hydrogen or methane above baseline within 90 minutes of ingestion. Methane elevation specifically indicates methanogen overgrowth, formerly classified as constipation-predominant IBS but now recognized as a distinct pathophysiological entity. People with methane-dominant SIBO are especially sensitive to probiotic introduction because the methanogens are archaea, not bacteria, and most probiotic products contain no organisms that meaningfully target them. Another condition often missed is bile acid malabsorption. If your terminal ileum isn't reabsorbing bile acids efficiently, introducing probiotics can alter bile acid metabolism further and trigger urgent diarrhea. This is distinguishable from probiotic intolerance because the diarrhea typically occurs within 30 to 60 minutes of dosing rather than developing gradually over hours.
What to Avoid
Do not combine probiotics with prebiotics in the initial testing phase. Prebiotics like inulin, FOS, and GOS are fermentable fibers that feed both beneficial and problematic bacteria indiscriminately. When your gut is in a vulnerable state, adding prebiotics to a probiotic protocol multiplies the fermentation load and turns a manageable side effect profile into a severe one. Many commercial probiotic products include prebiotic fibers in their formula, which means you may be consuming them without realizing it. Check the ingredient list for chicory root extract, inulin, or oligofructose. These are prebiotics disguised as filler. Do not take probiotics on an empty stomach if the formulation is not enteric-coated. Stomach acid kills a significant portion of non-protected organisms before they reach the intestine, and the dying cells release endotoxins that can trigger localized inflammatory responses. Enteric coating delays dissolution until the pill reaches the more alkaline environment of the small intestine, increasing viable colony-forming units by approximately 10 to 100-fold depending on the coating quality.

Realistic Expectations
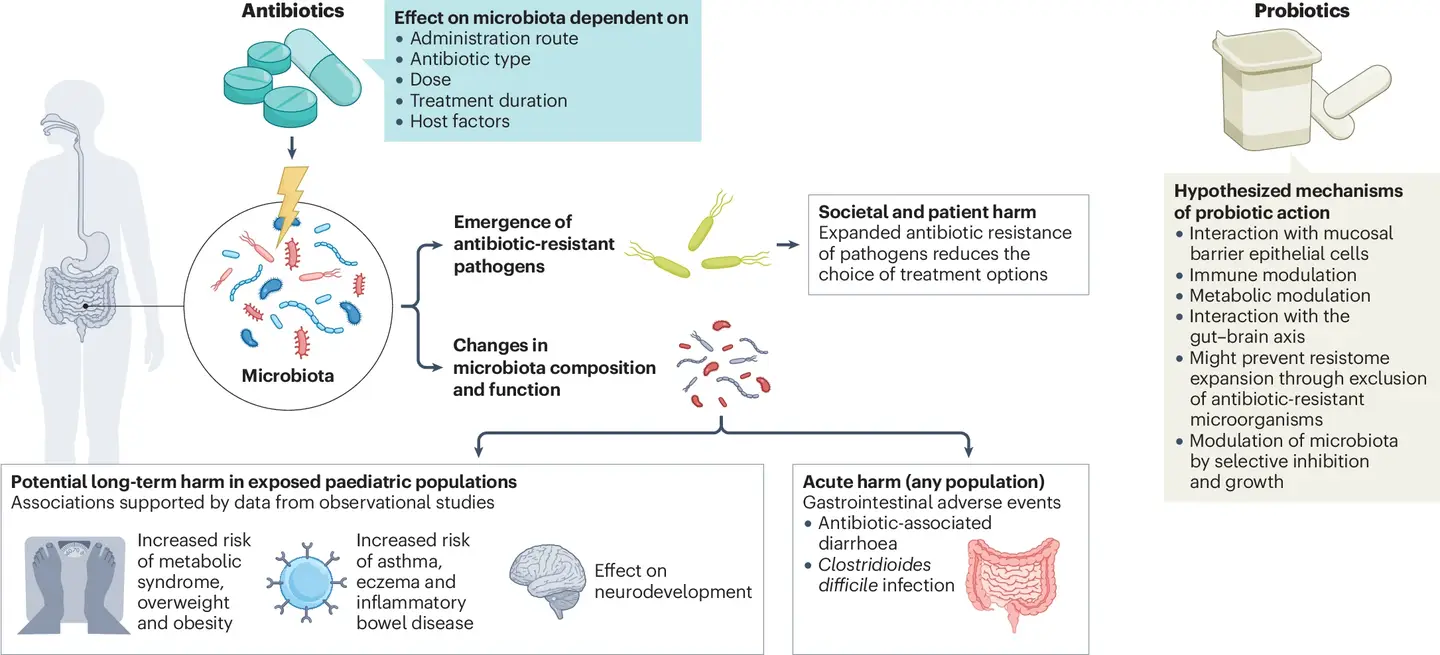
Probiotics are not a treatment for gut dysfunction. They are a modulatory tool that works for some people with some conditions and does nothing for everyone else. The clinical evidence supports their use primarily for antibiotic-associated diarrhea, where they reduce the risk by about 60 percent compared to placebo. For IBS, the evidence is strain-specific and modest at best. For leaky gut, there is no standardized clinical test and no consensus on what constitutes improvement. For SIBO, probiotics are generally contraindicated during the active overgrowth phase. If you want a pragmatic starting point that avoids the most common failure modes, begin with S. boulardii at a low dose, monitor your symptoms for 14 days, and only then consider introducing a bacterial strain if needed. Keep a daily log of bloating severity on a 1-to-10 scale, stool consistency using the Bristol Stool Chart, and any systemic symptoms like headaches or fatigue. This data will tell you whether you are responding positively, negatively, or not at all before you've spent a year and a half cycling through products that don't match your physiology.