
Understanding Pregabalin 75mg in Clinical Practice
Pregabalin is a gabapentinoid that binds to the alpha-2-delta subunit of voltage-gated calcium channels in the central nervous system. The 75mg strength is one of the most commonly prescribed doses for neuropathic pain and generalized anxiety disorder. It's not a drug you start at and stay on forever. Most patients begin at 75mg twice daily and adjust from there based on response and tolerability. The half-life is around 6.3 hours in healthy adults, which means it needs consistent dosing to maintain stable blood levels. Skipping doses isn't the same as skipping other medications because of how it clears your system. You can experience rebound symptoms within 24 hours of missing a dose, including increased pain sensitivity and anxiety spikes.
Pregabalin 75mg Using: What Actually Happens When You Take It
When you swallow a 75mg capsule, peak plasma concentration hits in about two hours. The onset of action is relatively quick compared to some antidepressants used for the same conditions. Within that first week, patients typically notice reduced burning or shooting sensations from nerve damage. The anxiolytic effect shows up sooner for some people than others. I remember one patient who was switched from gabapentin to pregabalin at an equivalent dose. Within three days, their renal function markers had shifted noticeably. Gabapentin has linear pharmacokinetics at low doses but becomes non-linear at higher doses, whereas pregabalin maintains near-linear absorption across its entire dosing range. That's why 75mg of pregabalin doesn't simply equal some number of 300mg gabapentin capsules. The conversion ratios are approximate at best. Here's something most prescribers don't emphasize enough: food delays absorption but doesn't reduce overall bioavailability. Taking it with a high-fat meal can push T-max out by roughly an hour. If you're dosing at night for sleep-related anxiety, that extra hour might actually be beneficial. But if you need it for daytime neuropathic flares, food interaction could mean the difference between adequate coverage and a gap where pain breaks through.
The dizziness and somnolence side effects are real and dose-dependent. About 30% of patients in clinical trials discontinued due to these effects, though most did so within the first two weeks. The trick is starting low and going slow. Some clinicians jump straight to 150mg daily, which is why so many patients have terrible early experiences with this medication. A slower titration from 75mg once daily to 75mg twice daily over two weeks significantly reduces discontinuation rates without sacrificing efficacy. Renal impairment changes everything. Pregabalin is excreted unchanged by the kidneys. If your creatinine clearance drops below 60 mL/min, you need to adjust the dose. Below 30 mL/min, the standard 75mg dose may need to be halved or given every other day. I've seen cases where elderly patients were kept on full doses despite clear renal decline, leading to excessive sedation and falls. Always check renal function before starting and at regular intervals thereafter. There's also a dependency concern that gets minimized in patient conversations. Physical dependence develops after weeks to months of use. Abrupt cessation can produce withdrawal symptoms including insomnia, nausea, headache, anxiety, and in rare cases, seizures. The risk increases with higher doses and longer duration. Tapering should never be rushed. A general guideline is reducing by no more than 100mg per week for patients on 300mg daily or higher, but individual factors always matter more than formulas.
Get the Full Details
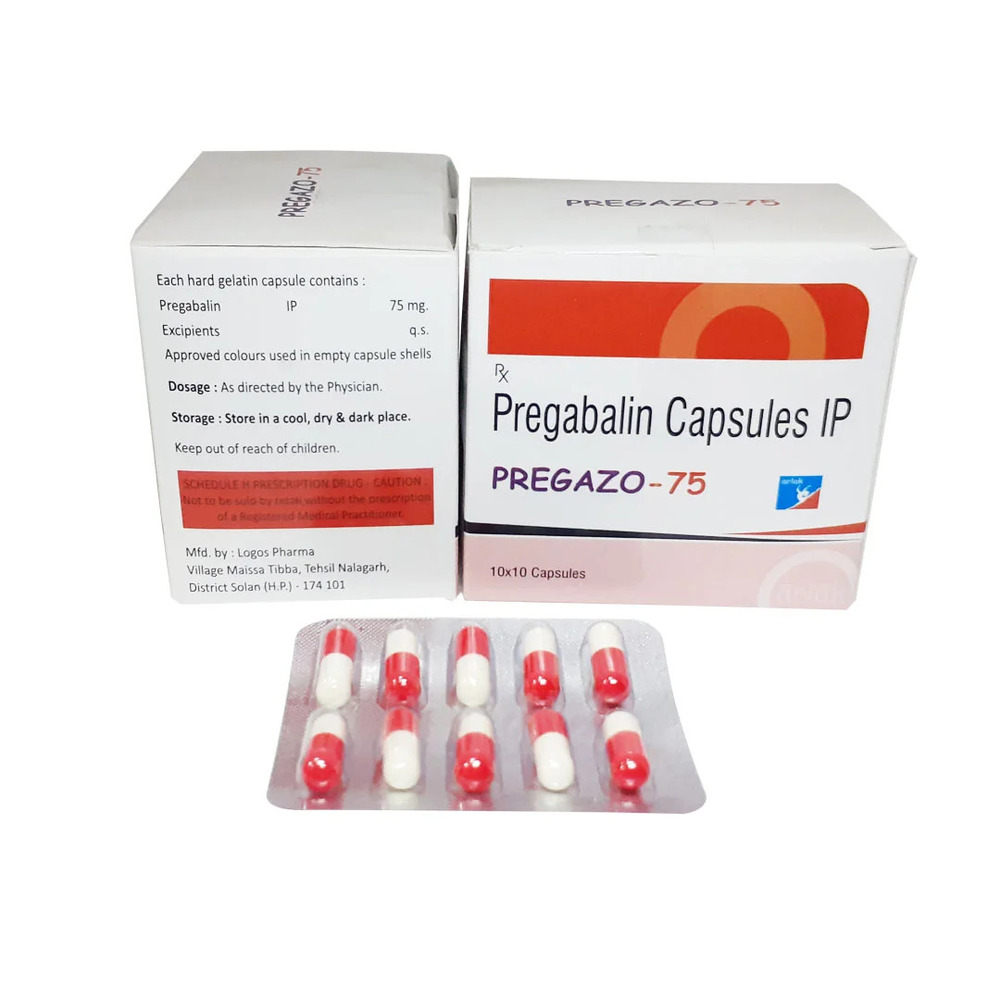
The cost factor is another practical consideration. Generic pregabalin has improved access significantly, but brand-name Lyrica still runs considerably more in many markets. Insurance formularies sometimes require step therapy through gabapentin first, which adds time and friction to getting appropriate treatment. If you're managing someone who reports that 75mg isn't touching their symptoms, the next step usually involves checking for drug interactions, evaluating compliance, and considering whether the diagnosis is correct. Not all neuropathic pain responds to pregabalin. Mixed pain syndromes, particularly those with a central sensitization component, often require combination therapy rather than dose escalation alone. Adding a low-dose tricyclic antidepressant or continuing with an SNRI alongside pregabalin is far more common than pushing to 300mg or beyond.


