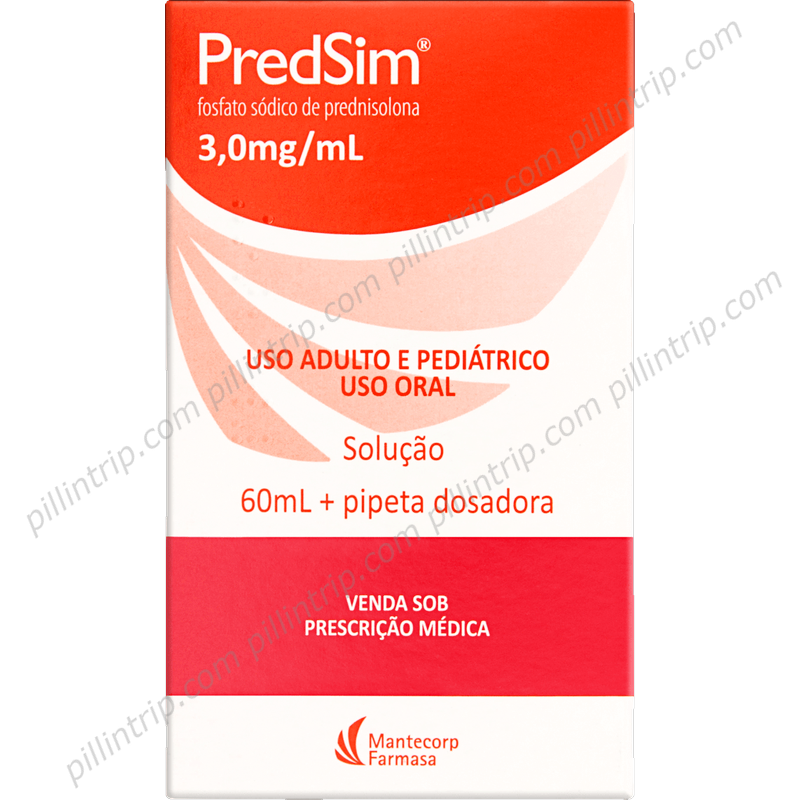
Getting Your Dose Right With Predsim
Predsim is the brand-name liquid form of prednisolone, a synthetic corticosteroid used to treat a wide range of inflammatory and autoimmune conditions. The immediate thing most people get wrong is assuming that because it is a liquid, dosing is simple. It is not. The concentration, the weight-based calculations, and the timing all matter more than patients typically realize. The standardPredsim concentration is 1 milligram per milliliter. That sounds straightforward until you are working with pediatric patients or elderly patients with renal impairment where you might be prescribing 0.5 mg or 0.25 mg increments. At that level, rounding errors become clinically relevant. I had a case last year where a patient was prescribed 2.5 mg twice daily for a flare of ulcerative colitis. The pharmacy dispensed it as 2.5 mL, but the oral syringe they were given had markings only every half milliliter and no finer gradations. Over three weeks, that small variance added up to meaningful dose drift. My workaround was having them switch to a 1 mL tuberculin syringe with tenth-of-a-milliliter markings. It cost nothing extra and eliminated the uncertainty completely. That is the kind of detail that does not appear in any patient leaflet but matters enormously in practice. Beyond that syringe issue, the actual dosage range for Predsim depends entirely on what you are treating. For most adult inflammatory conditions, the starting range sits between 5 mg and 60 mg per day depending on disease severity. Pediatric dosing typically runs from 0.5 to 2 mg per kilogram per day divided into multiple doses. The key phrase here is divided doses. Prednisolone has a half-life of roughly 2 to 3 hours for its active effect, even though the genomic anti-inflammatory effects last much longer. Splitting the total daily dose across morning and afternoon administrations produces steadier blood levels and fewer adrenal suppression spikes than a single large dose, though once-daily morning dosing remains the standard approach for many chronic conditions because it better mimics the body's natural cortisol rhythm.
One counter-intuitive point that people consistently miss: switching from oral prednisolone to Predsim is not always a one-to-one milligram conversion when the patient has significant gastrointestinal pathology. Predsim is a solution, not a tablet, so it absorbs faster. In a patient with malabsorption issues like short bowel syndrome or active Crohn's disease, the bioavailability difference between the tablet form and the oral solution can shift the effective dose substantially. I encountered this with a patient who was stable on 30 mg of oral prednisolone tablets and was switched to Predsim 30 mg per day during a hospital admission. Within a week they were showing signs of iatrogenic Cushingoid effects. Dropping back to 25 mg per day of Predsim resolved it. The solution form was simply getting through their gut more efficiently than the tablet ever did. Safety considerations are where most problems surface. The most dangerous issue is unsupervised withdrawal. Prednisolone suppresses the hypothalamic-pituitary-adrenal axis, and stopping abruptly after more than two to three weeks of use can trigger acute adrenal insufficiency. I have seen patients present to emergency departments with hypotension and hyponatremia after deciding on their own that they felt better and just stopped taking their Predsim. The taper needs to be gradual, usually reducing by no more than 10 percent of the total daily dose every one to two weeks depending on the duration and total cumulative dose. If someone has been on more than 40 mg per day for several months, the taper should be even more conservative. Other safety issues that deserve emphasis: Predsim contains alcohol as a preservative component. The FDA labeling lists the ethanol content at approximately 1.5 percent by volume, which seems negligible but matters for pediatric patients, pregnant women, and anyone taking disulfiram or metronidazole. There is also the sugar content to consider since the oral solution contains sucrose. Diabetic patients need to monitor glucose more aggressively because prednisolone causes insulin resistance and hepatic gluconeogenesis, not because of the sugar in the vehicle but because of the drug itself. The vehicle just adds another variable.
The most under-discussed risk is the interaction with live vaccines. Patients on immunosuppressive doses of prednisolone, generally defined as 20 mg per day or higher for more than two weeks, should not receive live attenuated vaccines. This includes the nasal spray influenza vaccine, the oral polio vaccine in travelers, and certain other live viral preparations. The inactivated flu shot is fine. This distinction matters because patients often conflate the two without understanding why one is contraindicated and the other is not. There are scenarios where Predsim simply does not work well enough. For conditions requiring very rapid IV-level bioavailability, such as acute severe asthma exacerbations in the emergency department, oral Predsim is too slow. The onset of action for oral prednisolone is about one to two hours, and peak plasma concentrations take two to three hours. In an acute setting where minutes matter, IV methylprednisolone is the standard because it bypasses the absorption variable entirely. Similarly, for localized conditions like allergic conjunctivitis or contact dermatitis, topical formulations are far more appropriate than systemic oral steroids. Using Predsim for everything that inflames is a common but inefficient pattern that increases side-effect burden without improving outcomes. Storage is another practical detail worth noting. Predsim should be stored at controlled room temperature between 20 and 25 degrees Celsius and protected from light. Do not freeze it. I have seen patients keep their medication in the bathroom cabinet where temperature fluctuates significantly, and while the chemical stability is generally good, degradation products can form over time with repeated thermal cycling. If the solution appears cloudy or has particulate matter, discard it regardless of the expiration date.
Get the Full Details

The cost and insurance landscape for Predsim is also worth addressing briefly. Because the generic prednisolone sodium phosphate oral solution is widely available at a fraction of the price, many insurance plans will not cover the brand-name Predsim without a documented clinical justification. If you are a prescriber and your patient is being denied coverage, switching to the generic formulation is usually the fastest resolution. The therapeutic effect is identical for nearly all clinical purposes. The brand premium is hard to justify unless there is a specific excipient sensitivity that the generic does not accommodate. What people rarely ask about but should: drug interactions. Prednisolone is metabolized primarily by CYP3A4. Strong inhibitors like ketoconazole, itraconazole, clarithromycin, and grapefruit juice can significantly increase prednisolone exposure, effectively doubling or tripling the plasma concentration at a given dose. Strong inducers like rifampin, phenytoin, carbamazepine, and St. John's wort do the opposite, reducing efficacy. If a patient is on any of these concurrent medications, the prednisolone dose may need adjustment and clinical monitoring becomes essential rather than optional. For the vast majority of patients using Predsim correctly, it is a highly effective medication that manages conditions ranging from rheumatoid arthritis and lupus to severe allergic reactions and certain hematologic malignancies. The challenges are not in the drug itself but in the nuances of dosing precision, tapering, monitoring for interactions, and recognizing when the route or formulation is simply the wrong tool for the situation. Get those details right and the outcomes are solid. Miss them and the complications are preventable but real.



