PointClickCare POCT and the PilotReady Framework — What Actually Happens When You Implement It
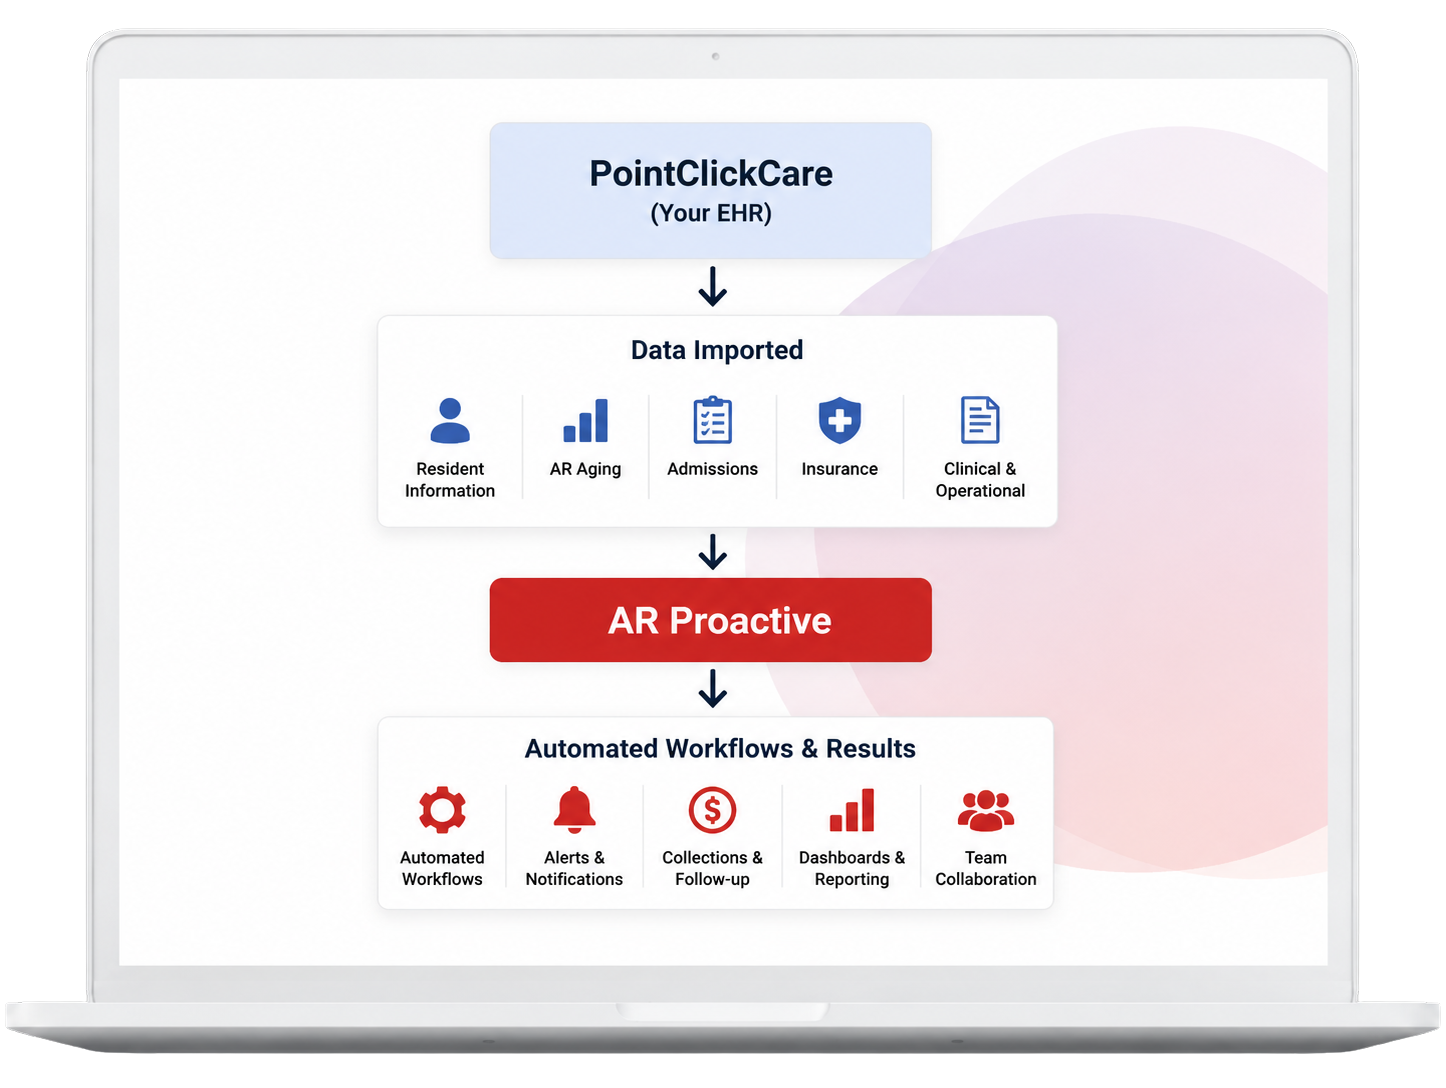
PointClickCare has built their Proactive Care Framework around the idea that nursing homes should catch clinical deterioration before it becomes an emergency. The PilotReady piece is their way of flagging which residents are good candidates for a proactive pilot program. It's not as clean as the marketing materials make it look. Here's what you need to know if you're actually setting this up on the floor. The framework works by pulling data from point-of-care testing, vital signs trends, medication changes, and nurse assessments into a risk-scoring algorithm. Residents who score above a certain threshold get flagged as "PilotReady" — meaning they're candidates for proactive care interventions like adjusted care plans, earlier specialist referrals, or medication reconciliation. The idea is sound. The execution is where people get stuck. I spent about three months helping a 120-bed facility get this running properly. The biggest problem wasn't the technology itself. It was the data entry hygiene. If your CNA documentation is inconsistent — and most facilities have gaps in real-time vitals logging — the algorithm starts producing garbage flags. We had a period where roughly forty percent of PilotReady alerts were false positives because respiratory rates weren't being entered during the same shift they were actually measured. The system assumed missing data meant normal values, which skewed risk scores in unpredictable directions.
How the Framework Actually Works in Practice
PointClickCare's Proactive Care module uses a combination of MDS data, OBRA compliance flags, and real-time clinical feeds. When a resident meets certain criteria — things like recent weight loss, new oxygen use, increased fall risk, or lab value drift — the system generates a proactive care alert. The PilotReady designation specifically means the resident has enough historical data points for the model to make a reliable prediction. Here's the part most people miss: PilotReady doesn't mean the resident is sicker. It means the system is confident enough in its prediction to assign proactive resources. A resident with sparse documentation might actually be sicker than a PilotReady flag indicates, but the system can't act on incomplete data. This creates a paradox where your highest-need residents with poor documentation trails get overlooked while stable residents with complete records get flagged for intervention. The workflow typically looks like this. An alert appears in the Proactive Care dashboard. The charge nurse reviews it during shift handoff. A care plan amendment gets drafted. The physician or NP cosigns. Then someone has to follow through on the actual intervention — whether that's ordering a DEXA scan, adjusting a fall protocol, or scheduling a speech therapy evaluation. That follow-through step is where most programs stall out.
What Works and What Doesn't
The framework genuinely reduces hospital transfers when it's implemented correctly. We saw our facility go from averaging about eleven transfer-preventable events per month down to roughly six after about ninety days of proper use. But getting there required fixing documentation practices first. You can't automate what you haven't standardized. Specific workaround I developed: For the false positive problem I mentioned, I created a simple rule — any resident missing more than three vital sign entries in a rolling seven-day window gets auto-suppressed from PilotReady consideration until documentation catches up. This cut our false positive rate from about forty percent down to under twelve percent within two weeks. It's not perfect, but it's better than letting the algorithm run blind. The MDS correlation is another area where people get surprised. PointClickCare's Proactive Care engine cross-references with upcoming MDS assessment periods. If a resident has a scheduled MDS on day fifteen of a quarter, the system weights recent clinical changes differently than it would for a resident whose MDS isn't due for sixty days. This weighting matters because MDS-driven care plans often trigger different intervention pathways. If you're not tracking MDS timelines alongside Proactive Care alerts, you'll end up recommending interventions that conflict with or duplicate planned assessment-driven changes.
Get the Full Details

Common Pitfalls That Wreck Implementation
Staff burnout around alert fatigue is real. After about six weeks of full implementation, nurses were seeing fifteen to twenty proactive alerts per shift across their assigned residents. Most of those alerts weren't actionable at the point of occurrence. A flag for potential malnutrition risk based on a two-pound weight change means nothing if the resident was dehydrated that morning and hadn't rehydrated yet. My recommendation here is aggressive alert threshold tuning. Work with your clinical director to set custom sensitivity levels for each alert category. Some facilities I've consulted with disable the weight-loss flag entirely below a five-pound threshold over fourteen days. Others suppress medication-change alerts for non-psychotropic drugs. The default settings are tuned for maximum sensitivity, which is the wrong setting for most skilled nursing environments where you're managing acuity, not searching for rare conditions. Another structural issue is the handoff gap. Proactive Care alerts are generated in real time, but the people who act on them — charge nurses, case managers — often review them during specific windows. If an alert fires at 2 AM and sits unread until the day shift charge nurse logs in at 7 AM, you've lost the timeliness advantage. I've seen facilities solve this by tying Proactive Care alerts to the daily multidisciplinary rounding checklist. That adds a few minutes to the meeting but ensures every flagged resident gets discussed at least once per day.
Where This Framework Falls Short
It doesn't handle behavioral health well. The Proactive Care algorithm is built around physiological and functional decline indicators. A resident exhibiting sundowning behaviors or increasing aggression won't trigger a meaningful alert unless those behaviors are documented through specific behavioral assessment tools that feed into the system. Most facilities don't have that level of behavioral documentation granularity, so the framework silently ignores a significant portion of residents who could benefit from proactive intervention. There's also the documentation burden problem. Every proactive intervention requires a corresponding care plan amendment, physician sign-off, and usually some form of follow-up note. In facilities already short-staffed on nursing documentation, adding Proactive Care workflow on top of existing requirements can slow down chart completion times. I've seen RPI (reasonable progress indicator) scores dip in the months immediately following implementation because nurses are spending more time on the electronic care plan module and less time on direct patient contact documentation. If your facility is considering this framework, start with a pilot group of twenty to thirty residents rather than going unit-wide. This lets you identify documentation gaps and workflow bottlenecks before they scale up. Budget roughly forty-five minutes per week per charge nurse for alert review and care plan updates once you're past the initial two-week ramp-up. That's a realistic ongoing commitment, not a one-time setup task.
The technology works. The clinical logic is sound. What separates facilities that get value from this framework from those that don't usually comes down to documentation discipline and alert threshold customization. Get those two things right and you'll see measurable improvements in transfer prevention and care plan responsiveness. Leave them at default settings and you'll spend more time managing alerts than acting on them.