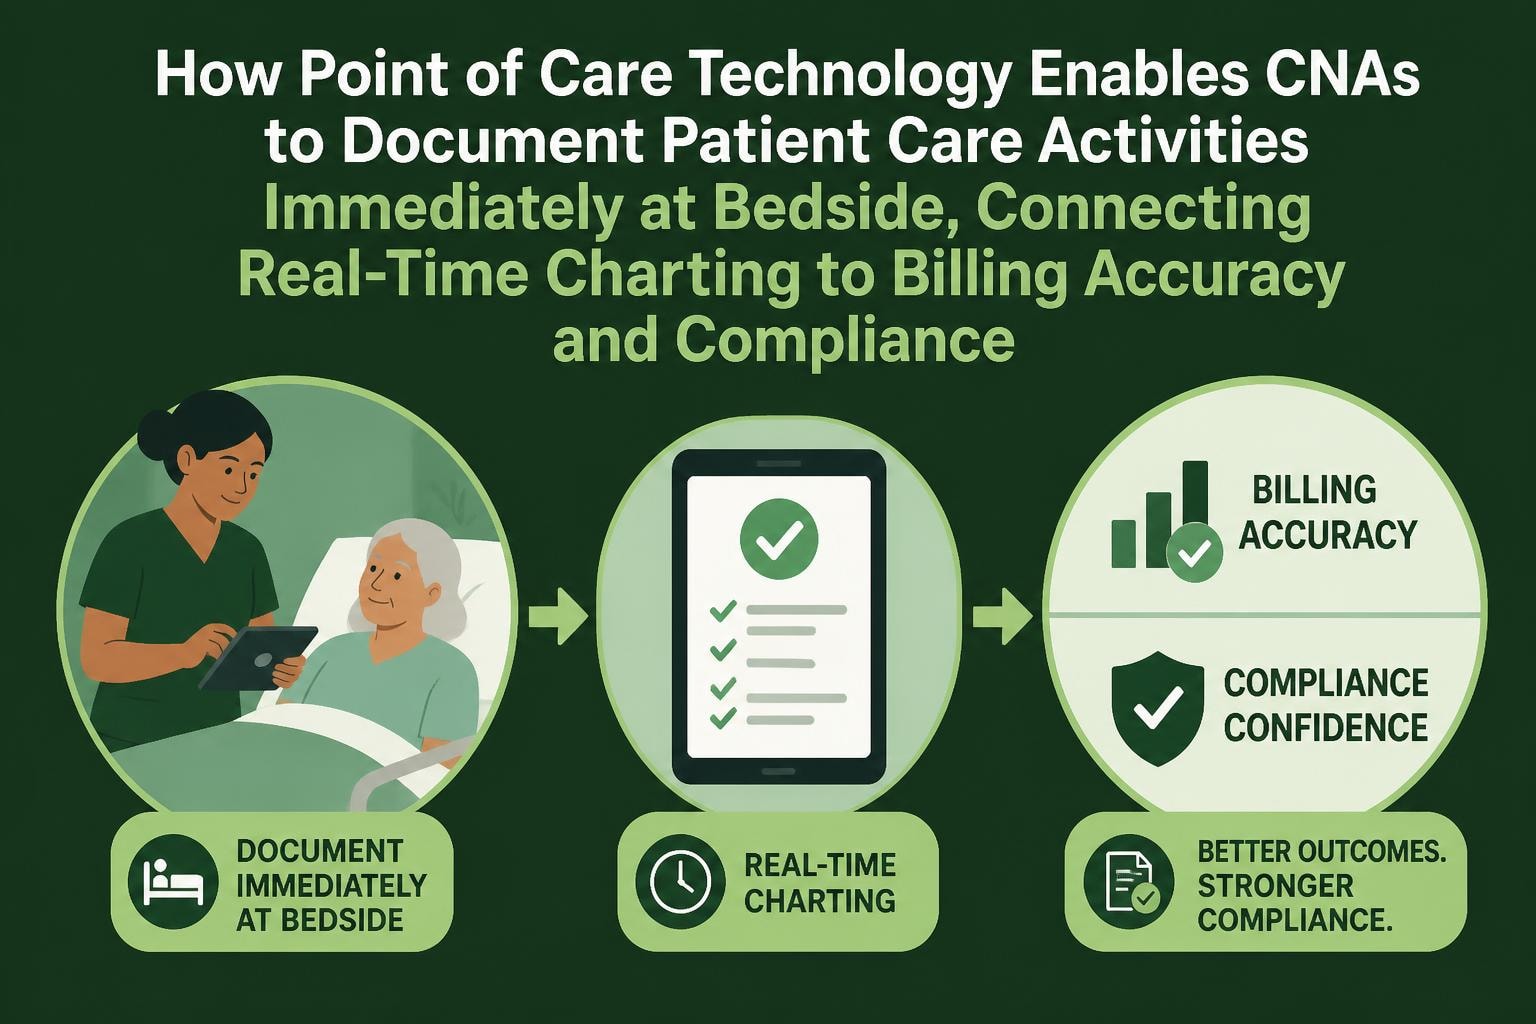
Pointclickcare CNA 25: What Actually Happens When You Use It on a Shift
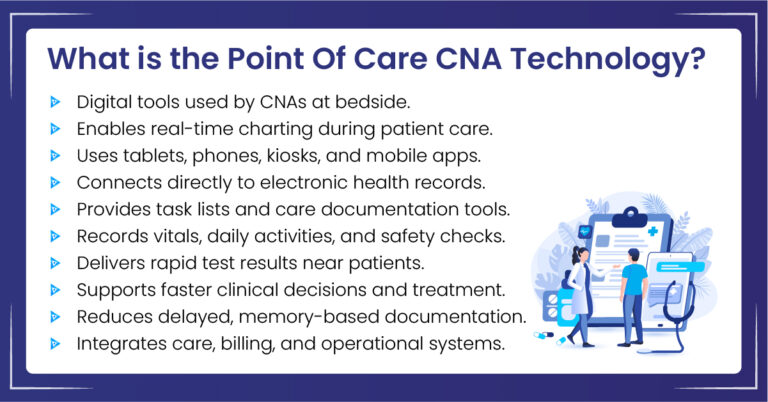
Pointclickcare is a cloud-based electronic health record platform widely used in skilled nursing facilities and long-term care. The CNA 25 module is the front-line documentation tool that certified nursing assistants use during their shifts to record vitals, intake and output, hygiene, mobility, and behavior observations. It replaced the paper flow sheets most of us grew up charting with, and the transition was not smooth for anyone. I have been working in long-term care enough to remember the before and after. The software is not perfect. It is also not nothing. Here is how it functions in practice and where people tend to make mistakes.
Pointclickcare Cna 25 Revolutionizing Nursing Documentation And Care
Getting started requires an active Pointclickcare account with CNA-level permissions assigned by your facility's administrator. These permissions vary by state and by vendor configuration, so you cannot self-provision access. Once your IT person or clinical director sets you up, you log into the Pointclickcare mobile app on the facility-issued tablet or your own device if BYOD is allowed. The primary workflow during a shift follows a predictable pattern. You open your assignment list, select a resident, and navigate to the relevant tab. Most CNAs spend the majority of their time in the ADL tab, the Behavior tab, and the Vitals section. The system is designed to push documentation in real time. There is no local draft storage. If the tablet loses connectivity, any unsaved entry is gone. That happens more often than you would think in older facilities with dead zones near the linen closets and supply rooms. One thing most beginners miss is that the CNA 25 interface is heavily dependent on how your facility has configured its templates. Some sites use abbreviated CNA forms while others require comprehensive shift notes. I learned this the hard way during my first month using the platform at a 120-bed facility in Ohio. They had a custom template that forced me to document bowel movement consistency using a modified Bristol Stool Scale inside a free-text field instead of the built-in dropdown. The field would not accept anything other than a numerical value from one to seven, but the policy handout we received described a five-point scale. I spent forty-five minutes documenting three residents before I realized I had to enter the numeric equivalent of what the physician order sheet called for. The workaround was to call our charge nurse, get her to override the template restriction, and then update those three records the next morning. Since then I always check the physician's order sheet against the digital template on day one of a new assignment. They do not always match.
The intake and output section deserves special attention because it is where audits catch people. Pointclickcare requires that total I&O is reconciled at the end of every shift. The system will not let you close out a shift without this reconciliation, but it also will not flag mismatches between what you charted and what the nurse's notes show. In one facility I worked at, the automated I&O report consistently showed a negative balance of approximately 150 milliliters for several residents because the oral intake dropdown did not include a 250 ml cup option. The default was 200 ml. I started entering residual amounts manually in the notes section and adjusting the totals during the close-out screen. That kept the reports accurate enough for monthly quality reviews. Behavioral documentation is another area where the platform introduces risk. The behavior tabs pull from the DSM-5 coding structure in some configurations. This means that selecting a behavior code automatically generates a clinical flag in the MDS assessment module. I have seen CNAs who were only trying to note that a resident was occasionally restless inadvertently trigger a behavioral syndrome flag that stayed on the resident's record for ninety days. The fix was to work with our MDS coordinator to adjust the configuration so that certain observation fields do not auto-populate into the MDS dataset. After that change, documentation became much more accurate. There are limitations to the system that vendors will not advertise. The mobile app struggles with batch entry. If you need to document vitals for ten residents in rapid succession, the app forces you to open each resident card individually. You cannot create a spread-sheet style entry screen unless your facility purchases the extended workstation module, which is expensive and usually reserved for nurses. For CNAs on a busy med-pass or turnover shift, this means you are looking at roughly three to five minutes per resident for vitals compared to the thirty seconds it took on paper. Over a twelve hour shift with thirty residents, that is an additional two to four hours of charting time. Some facilities have compensated for this by assigning a float CNA whose only job during peak hours is data entry, but that costs money and staffing varies.
Get the Full Details
The offline mode exists but it is unreliable. Pointclickcare claims offline capability, but in my experience the synchronization process frequently corrupts entries made during disconnected periods. I recommend treating offline mode as a last resort. If you lose connection, stop charting immediately, move to an area with signal, and restart the session. Do not trust that the app is saving locally. It is not consistent enough to rely on. Another practical detail that matters is how the system handles late documentation. Pointclickcare tracks every edit with a timestamp and a user ID. If you document a fall that occurred at 1400 hours but you do not enter it until 2100 hours, the system records the actual event time and the documentation time separately. This sounds like a good thing, and it is, but it also means that if you forget to chart during your shift, you cannot simply backdate the entry to make it look routine. Auditors see the gap immediately. The best practice is to chart as you go, even if it means pausing for thirty seconds between residents. A thirty second pause saves you from a compliance review later. For training purposes, I recommend shadowing someone who has been using the platform for at least two months before attempting independent documentation. The interface changes slightly depending on your facility's version, and most online tutorials are generic. They do not cover the specific quirks of your site's configuration. Watch how your experienced coworkers handle the I&O close-out, how they resolve template mismatches, and which shortcuts they use between resident cards. These practical details matter more than any official guide.
If you need to download the app, go to the Apple App Store or Google Play Store and search for Pointclickcare. The official application is free, but access is controlled by your employer. You cannot register independently. Your facility must have an active contract with Pointclickcare and your role must be mapped to the correct permission set. If you are denied access after being told you would receive it, the issue is almost always at the administrative level, not the technical level. Contact your supervisor and ask them to verify your role assignment in the Pointclickcare admin panel. The platform does have some genuinely useful features that make documentation better than paper. The automatic vital sign trend graphs are visible to the entire care team. When a resident's blood pressure shows a gradual decline over five days, any nurse or therapist can see the trend without pulling old paper charts. The real-time communication feature allows CNAs to flag concerns directly to the attending nurse within the resident's chart, which reduces the delay that used to happen when we had to find a nurse physically on the unit. These improvements are real and they matter for care quality. The system is not a magic solution, but it is an improvement over the alternatives we had. The main complaints from CNAs I have talked to center on three things: the slow response time on older tablets, the mandatory fields that do not always align with actual clinical situations, and the difficulty of correcting errors after a shift is closed. Error correction requires a supervisor override in most configurations, which means you cannot fix a typo without involving someone else. This creates friction and sometimes leads to incomplete documentation because people avoid entering uncertain information rather than dealing with the override process later.
My recommendation for anyone struggling with this system is to keep a small notebook on your person during your first two months. Write down the workarounds you discover as you go. The first shift in a new facility, the second shift, the third shift. Each one reveals a different configuration quirk. By the end of two months you will have a personal reference guide that is more useful than any generic tutorial. After that, you will know enough to train the next person coming in.