What Actually Happens When You Walk Into a Plasma Center
I used to think donating plasma was just sticking your arm out and waiting. It is nothing like that. The process involves needle insertion, anticoagulant mixing, centrifuge separation, and a return phase that keeps your red blood cells going back in while the plasma comes out. Most people leave with a sore arm and a gift card. The medicine inside that plasma? That is where things get serious. Phoenix has some of the highest collection volumes in the country. Not because people are more generous, but because the logistics work. The desert heat keeps demand for IV fluids steady, and the population growth means more trauma cases, more autoimmune treatments, more people needing immunoglobulin. The centers cluster around the I-10 and Loop 101 corridors because that is where the donor pool lives. You will find them in areas like Ahwatukee, South Mountain, and near the West Valley suburbs. It is not random placement. It follows commuting patterns and insurance networks. The plasma itself becomes fractions at processing facilities. Factor VIII, Factor IX, albumin, IVIG. These go into blood products for burn victims, hemophiliacs, people with primary immunodeficiency disorders. A single donation can yield enough material for multiple patients. That is why the centers operate on volume. One person donating every other week does not move the needle much. The system needs consistent repeat donors, and Phoenix has enough of them to sustain regional supply chains.
The Real Process, Not the Brochure Version
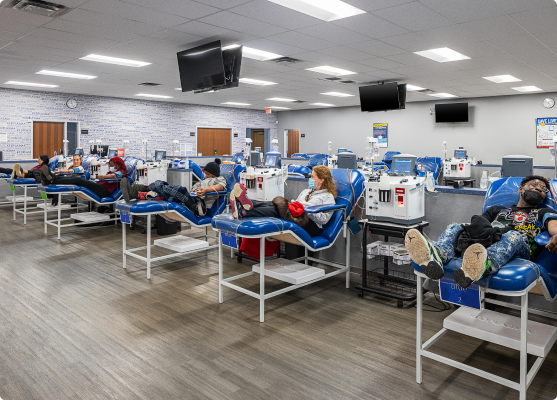
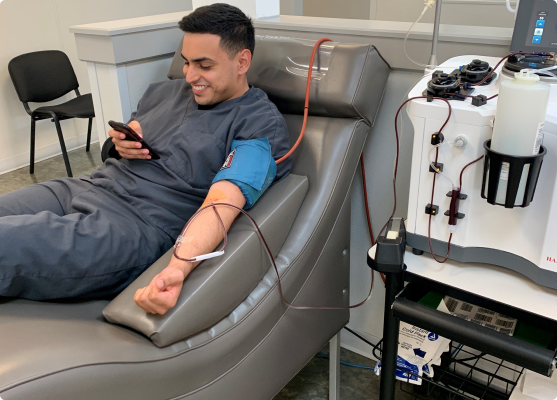
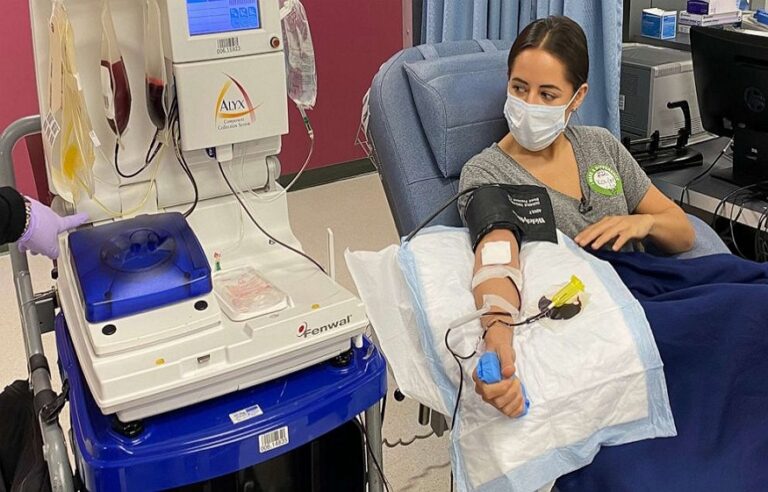
Check in at the front, show your ID, fill out a health questionnaire. Then they take your vitals. Blood pressure, pulse, temperature, hemoglobin check with a finger prick. If your hemoglobin is below 12.5 grams per deciliter, you do not donate. Simple. No argument. They will note it and send you home with advice to eat more iron and come back in a few weeks. After that, you sit in a recliner. The phlebotomist finds a vein in your antecubital fossa, usually the median cubital since it is the most stable. They insert a large bore needle, maybe 16 or 17 gauge. The machine draws blood at about 50 to 60 milliliters per minute, spins it, separates the plasma, and returns the rest. A full donation takes roughly 45 to 60 minutes for first-time donors. Regulars often finish in 35 minutes because the vein is established and the machine runs smoother. I learned the hard way that staying hydrated matters more than most people admit. Not just drinking water the day before, but actually maintaining volume. My first few donations, I showed up after a long drive and barely drank anything. The machines flagged me for low plasma volume three times in one month. They pulled less from me each time, sometimes only 600 milliliters instead of the usual 800 to 900. Once I started drinking 64 ounces the night before and another 16 before the appointment, the runs became consistent and I stopped getting flagged.
Complications That Nobody Talks About
Citrate reaction is the big one. The anticoagulant used during collection is citrate, and it binds calcium in your blood. Some people metabolize it slowly. You get tingling around the mouth, fingertips go numb, you might feel a mild muscle twitch. It is not dangerous in most cases, but it cuts the donation short. The solution is slower infusion rates and sometimes a calcium supplement taken before the appointment. I carry chewable calcium tablets and take two right after checking in. It has kept my reactions minimal over dozens of visits. Vein collapse is another issue that regulars know well. If you keep hitting the same spot, the vein walls scar. I learned this after months of consistent donation in the same center. The tech finally switched me to the other arm because my right antecubital had too much trauma. Rolling the vein became a negotiation instead of a routine insertion. Cross-training your arms, rotating sides, and letting the tech choose the site instead of demanding your usual vein makes a real difference. The lower yield on low-volume days frustrates people, but it is a safety feature. The machine monitors your circulation time and plasma protein levels. If the conductivity drops, it pulls back. You are not losing blood, but you are also not getting the full compensation. The gift card pays the same amount regardless of yield in most centers, which seems backwards until you realize the center is managing inventory for the processing labs. Less plasma collected today means less fractionation downstream, so they have to order from other regions.
Get the Full Details

What the Money Actually Looks Like
Phoenix centers typically pay between 50 and 100 dollars per visit for new donors, with tiered increases for returning regularly. Some places run promotions during slow weeks, pushing it higher. The schedule matters more than the base rate. Donating twice a week is the legal maximum under FDA guidelines, and that is where the real income sits. Most people who rely on this for supplemental income are doing 700 to 900 dollars a month before taxes. The tax form part catches people off guard. You receive a 1099-MISC if you make over 600 dollars in a year. That is taxable income. I stopped tracking it religiously until I got my first form and realized I owed several hundred in self-employment tax on money I thought was just compensation for inconvenience. Set aside 20 to 25 percent if you are doing this consistently. It prevents the April surprise.
When to Avoid It Completely
Recent travel to malaria-endemic areas disqualifies you for four weeks. Active infections, even a mild cold, hold you back until symptoms resolve. Pregnancy and nursing are automatic deferrals. Certain medications like isotretinoin require a three-month wait. The health screening catches most of this, but being upfront saves everyone time. I once hid a minor skin infection because I did not want to miss a bonus week. They found it during the physical exam anyway and refused the draw. I lost the appointment and looked dishonest in the process. Just tell them. Iron deficiency is the most common reason for rejection in the Phoenix area, especially among women. The finger prick hemoglobin test is strict. If you are borderline, taking 18 milligrams of elemental iron daily for three weeks before your next attempt can push you over the threshold. I tracked my own numbers with a home test kit from the pharmacy and adjusted my supplement schedule accordingly. It turned consistent rejections into consistent acceptances.
How the Supply Chain Actually Works
Collected plasma goes to fractionation plants, not hospitals. The major facilities serving the Southwest are in Texas and Massachusetts, though Arizona has seen recent development. Trucks run on fixed schedules, picking up cold-storage containers from each center. The plasma is tested for HIV, hepatitis B and C, syphilis, and other markers before it ever enters the fractionation pipeline. Rejected units are disposed of, but the rejection rate is low, usually under 2 percent of collections. The finished products have shelf lives ranging from months to years depending on the fraction. Albumin lasts the longest. Some immunoglobulin preparations degrade faster. Centers in Phoenix ship out daily during peak collection hours, usually between 10 AM and 2 PM when donor traffic peaks. That timing aligns with truck routes that feed into regional distribution hubs. If you are considering this as a way to support medical supply while earning extra income, the Phoenix market is viable. The demand is real, the centers are numerous, and the process is standardized. It is not glamorous, and your arm will bruise occasionally, but the system depends on people showing up consistently. That is the actual mechanism behind lifesaving medicine, and it runs on repeat donors, not one-time generosity.