Breaking Down the Bony Ring
The pelvis is one of those anatomical regions that looks straightforward on a diagram until you actually need to measure it for clinical or forensic purposes. I spent years doing cadaver dissections and reading obstetric reports, and the distinction between true and false pelvis still trips people up when they're rushing through a practical exam. Most textbooks draw a clean line at the linea terminalis and call it a day. In reality, the boundary isn't always as obvious, especially in elderly specimens where the iliac crests have calcified and the sacral promontory is worn. You need to know what you're looking for before you start measuring, because getting the landmarks wrong throws off every subsequent calculation.
Pelvic Puzzle Decoding The True And False Pelvis
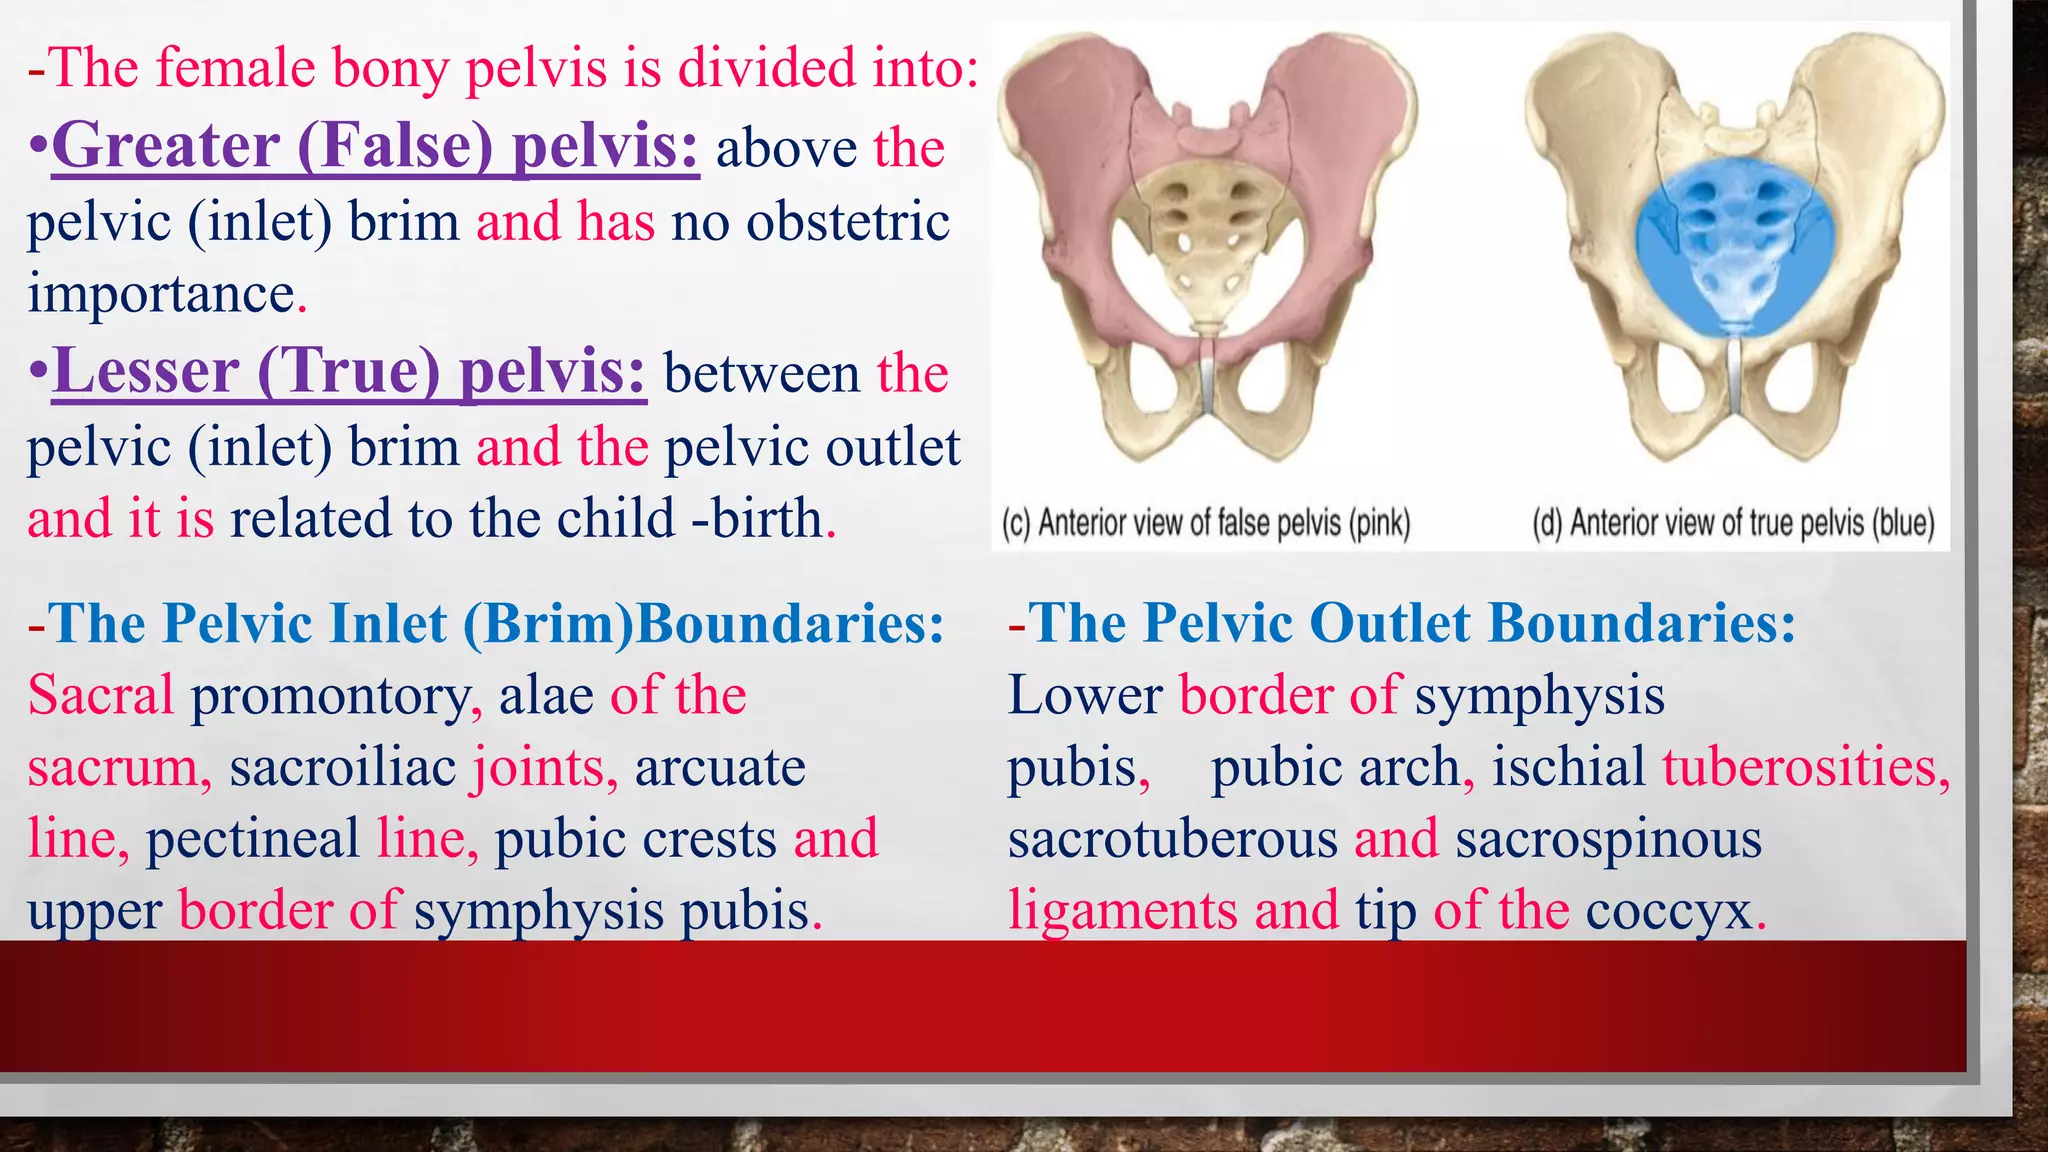
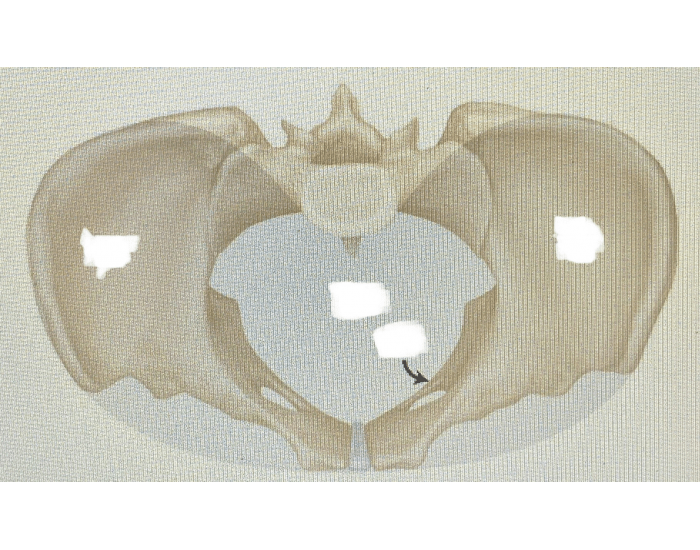
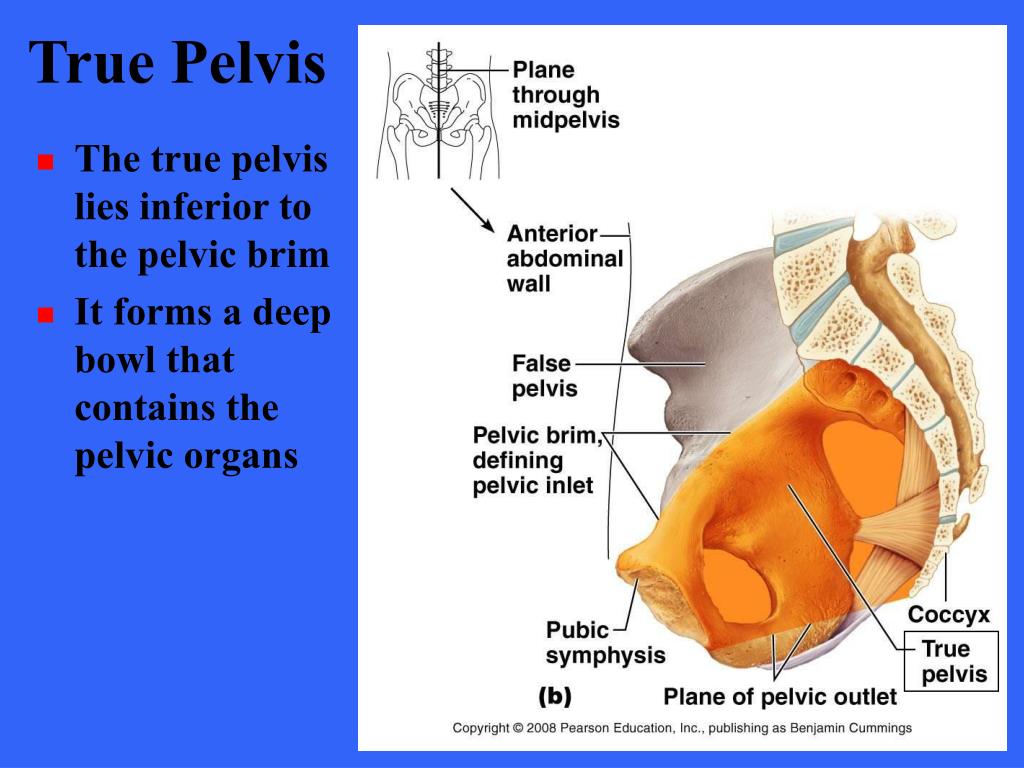
Here is how I actually approach this. Start by identifying the sacral promontory. That's the sharp anterior edge of the S1 vertebral body. Run your finger along the anterior margin of the sacrum and find where it sticks out the most. That point matters because it anchors the entire measurement system. From there, trace the linea terminalis forward. It runs from the promontory down along the arcuate line of the ilium, then along the pectineal line to the pubic crest, and finally to the pecten pubis. Everything above that ring is the false pelvis, or greater pelvis. Everything below is the true pelvis, or lesser pelvis. The false pelvis is mostly empty space bordered by the broad iliac wings. It holds bowel and sometimes an enlarging uterus during pregnancy. The true pelvis is the actual bony canal. It has an inlet, a cavity, and an outlet. Each of those has specific diameters you need to memorize because they determine whether a vaginal delivery is even mechanically possible. I remember a specific case that drove me crazy. A resident was calculating the diagonal conjugate on a patient with a noticeably flat sacrum, and they were getting numbers that didn't match the external measurements at all. The issue was the angle of the promontory itself. On some individuals, the sacrum sits almost vertical rather than curved inward. I told them to skip the diagonal conjugate and go straight to a lateral radiograph with a marker at the symphysis. That cut the guesswork down significantly. The X-ray shows you the actual distance from the symphysis pubis top to the promontory without relying on tactile estimation through soft tissue.
Measuring the True Pelvis Inlet
The inlet has four key diameters. The obstetric conjugate runs from the sacral promontory to the highest point on the posterior symphysis pubis. That is usually the shortest diameter and the one that matters most for delivery. The anatomical conjugate goes from the promontory to the top of the symphysis. The gynecoid conjugate is the diagonal conjugate measured clinically, typically around 12.5 centimeters in an adult female. The transverse diameter of the inlet stretches between the widest points of the linea terminalis on each side. That usually measures around 13 centimeters. The anteroposterior diameter runs from the sacral promontory to the midpoint of the pectineal line. This one is less clinically useful but helps in forensic reconstruction. When I first started learning this, I kept mixing up the true conjugate and the obstetric conjugate. They are not the same thing. The true conjugate runs to the midpoint of the posterior symphysis surface. The obstetric conjugate terminates higher, at the prominent ridge just below that midpoint. That difference is usually about half a centimeter, and in borderline pelvimetry cases, half a centimeter is the difference between a scheduled C-section and a trial of labor.
Get the Full Details
The Outlet Matters More Than People Think
Everyone focuses on the inlet, but the outlet is where most obstructed labors actually happen. The anteroposterior diameter of the outlet runs from the inferior border of the symphysis pubis to the sacrococcygeal joint. It averages about 11.5 centimeters. The transverse diameter of the outlet, also called the intertuberous diameter, runs between the ischial tuberosities. That is usually 11 centimeters in a standard gynecoid pelvis. There is a quick clinical rule here that is worth knowing. If the intertuberous diameter measures less than 8 centimeters, you are dealing with a potentially tight outlet. In those cases, you also need to check the posterior sagittal diameter of the outlet, which runs from the midpoint between the tuberosities to the sacrococcygeal joint. Add those two measurements together. If the sum is less than 15 centimeters, the outlet is too narrow for most term deliveries regardless of what the inlet looks like. I worked with a midwife once who relied entirely on the inlet measurements and missed a tight outlet. The baby's head engaged fine, descended normally, and then arrested at the perineum. The whole situation could have been predicted in five minutes with a simple outlet measurement done during the third trimester exam.
Pelvic Types and What They Actually Mean
The Caldwell-Moloy classification divides pelves into four main types. Gynecoid is the textbook ideal. Round inlet, generous diameters throughout. Android is heart-shaped with a narrow forepelvis and prominent ischial spines. It is more common in males and causes problems because the ischial spines are right in the birth canal path. Anthropoid is elongated anteroposteriorly with a wide transverse diameter. Platypelloid is the flattest type with a wide transverse inlet but dangerously short anteroposterior diameter. The problem with this classification is that real pelves rarely fit neatly into one category. I have seen specimens that were clearly android-gynecoid hybrids, and the classification system does not account for that. A more practical approach is to just measure the actual diameters and compare them to standard reference values rather than forcing a label onto the bone. Reference values for an average adult female: obstetric conjugate should be at least 11 centimeters, transverse inlet diameter around 13 centimeters, interspinous diameter at the level of the ischial spines should be 10.5 centimeters minimum, and intertuberous diameter at least 11 centimeters. Anything consistently below those thresholds warrants a closer look.
Practical Workflow for Students and Technicians
If you are learning this for exams or clinical work, here is the sequence I use. First, identify the sacral promontory and trace the linea terminalis mentally or with a probe. Second, measure or recall the inlet diameters. Third, check the midcavity at the ischial spine level. Fourth, measure the outlet diameters. That covers the full passage from top to bottom. Palpation during a clinical pelvic exam gives you the ischial spines and the sacrum indirectly. You can estimate the concavity of the sacrum and whether the spines are projected inward. You cannot feel the promontory through the anterior fornix in most patients unless the bladder is collapsed, which is why the diagonal conjugate technique exists. It uses the fingers to reach from the inferior symphysis up toward the promontory. One thing that catches people off guard: the male pelvis has the same true and false division. The terminalis exists regardless of sex. The differences are in the overall shape, the width of the inlet, and the angle of the pubic arch. Male pubic arches tend to be under 70 degrees while female arches are usually 80 to 90 degrees or more. That changes the outlet geometry significantly.
Where the System Falls Apart
Pelvimetry by palpation is inherently imprecise. Soft tissue thickness varies between patients. Body habitus makes the exam harder. Obesity alone can render clinical measurement nearly useless. Radiographic pelvimetry is more accurate but involves radiation exposure, so it is not something you order routinely anymore. CT-based 3D reconstruction is far more precise but expensive and usually reserved for complex surgical planning or forensic cases. For routine obstetric care, clinical assessment remains the standard despite its limitations. The World Health Organization and ACOG both recommend against routine radiographic pelvimetry because most women can be managed clinically without it. The minority who actually need precise measurements are the ones with known contractures, previous trauma, or rickets history. If you need reliable outlet measurements on a patient who cannot tolerate a full exam, a lateral radiograph with a radiopaque marker placed at the ischial tuberosities gives you what you need in about thirty seconds. It is faster and more accurate than repeated manual attempts.
Quick Reference Points
Sacral promontory marks the top of the true pelvis inlet. The linea terminalis is the continuous ridge that separates true from false pelvis. The ischial spines sit at the narrowest point of the midcavity. The pubic arch angle determines outlet width. The coccyx can move posteriorly during delivery, which effectively increases the outlet diameter by up to two centimeters in flexible specimens. Keep those landmarks in mind and the rest of the anatomy starts falling into place. The pelvis is not complicated if you build it systematically rather than trying to memorize isolated facts. Measure the inlet, check the midcavity, assess the outlet, and you will have a working understanding that applies across clinical, forensic, and anatomical contexts.