The Numbers Nobody Wants to Discuss First
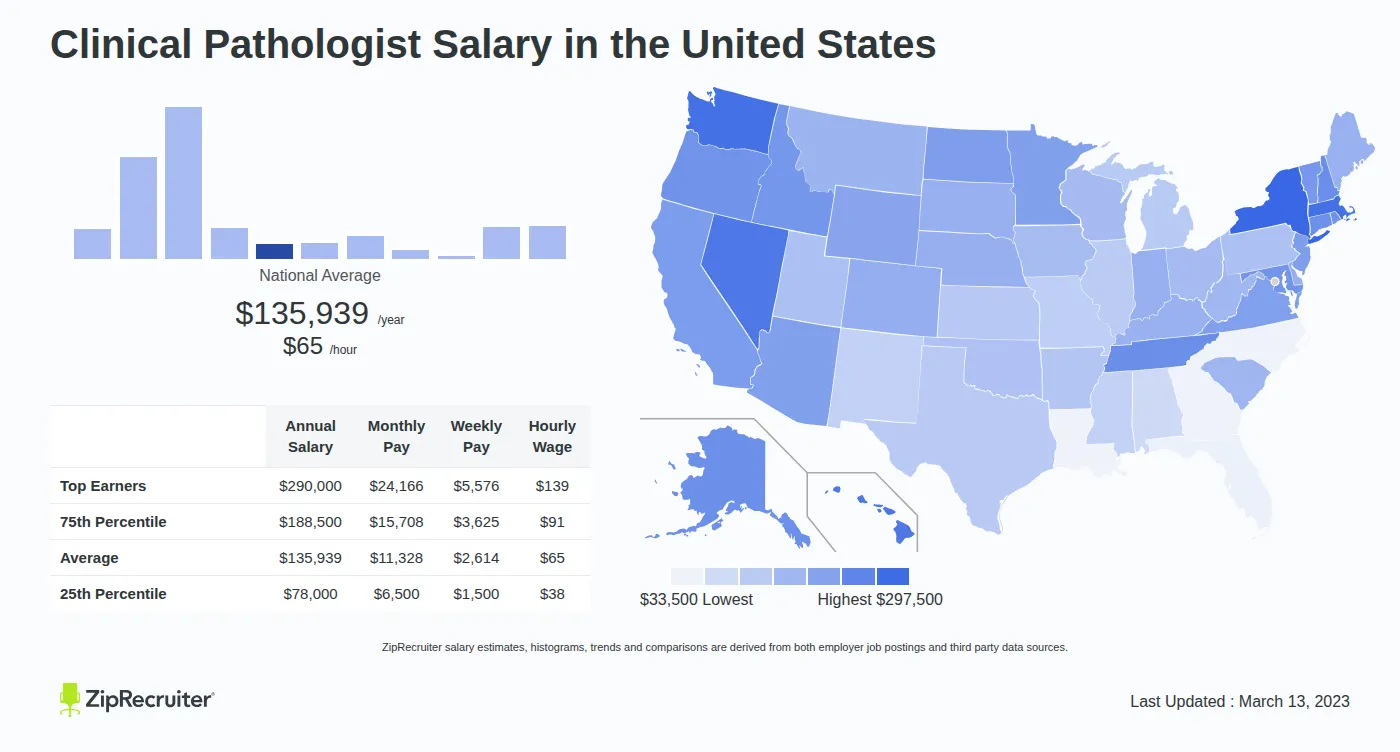
Pathologist salaries are one of those topics where the public perception and the actual numbers are pretty close, which is more than you can say for most medical specialties. According to recent BLS data and physician compensation surveys, the median annual wage for pathologists sits around $305,000 to $330,000 nationally. That puts them somewhere in the middle of the physician income distribution, below orthopedic surgery and dermatology but above family medicine and some other internal medicine subspecialties. The actual number you take home depends on several moving parts that don't show up in the summary statistics. Academic positions tend to pay less than private practice or hospital-employed roles. A dermatopathology subspecialist in a high-volume private lab in Texas or Florida will make significantly more than a general surgical pathologist running a low-acuity service at a rural university hospital. I've seen spreadsheets where the difference between two attending-level pathologists at the same institution was nearly $80,000 purely due to relative value unit (RVU) production and call stipends, not base salary. Subspecialty certification changes the math. Cytopathology, hematopathology, and molecular genetic pathology command higher RVU rates because they're more procedural and technically intensive. Surgical pathology, which is the bread and butter of general pathology training, has lower relative value weighting per case. A pathologist who did a fellowship in dermpath and sees 40 to 60 specimens a day in a busy private practice can clear $450,000 to $550,000 comfortably. Someone doing routine biopsy sign-out at a community hospital with minimal call and no procedural add-ons might be looking at $260,000 to $300,000. Both are fully qualified attending pathologists.
Geographic variation matters more than most people expect. Urban academic centers in expensive coastal cities often pay less than expected because the cost of living adjusts hiring committees' expectations, and the prestige factor attracts people willing to trade income for training volume. Rural and midwestern hospitals frequently offer signing bonuses, loan repayment, and base salaries 15 to 25 percent higher to attract candidates. I once recruited for a position in Nebraska where the advertised range was $380,000 with a $50,000 sign-on bonus because no one locally wanted the job and the regional pipeline was dry. The call component is another hidden variable. Hospital-employed pathologists covering overnight surgical consultations, frozen sections, and autopsies typically receive additional compensation through wRVU bonuses or flat call stipends. A busy metropolitan hospital with a Level 1 trauma center might pay an additional $30,000 to $60,000 annually for call coverage. Autopsy coverage, especially in county medical examiner settings, can add meaningful income but also meaningfully degrades quality of life. I worked a stint covering medicolegal autopsies in a high-volume city and the annual stipend was substantial but the emotional toll made the extra money feel like hazard pay, which it essentially was. Private laboratory ownership or partnership tracks change the trajectory entirely. Large commercial reference laboratories like Quest or LabCorp, or independent multi-specialty groups, often shift compensation toward a productivity model after a ramp-up period. The first year might be a flat salary while you build referral networks and caseload. By year three, partnership potential can push total compensation well above $500,000, but the catch is that you're selling your time and your name. Reference lab pathologists often handle extreme volumes with thin margins per case. The work becomes assembly-line adjacent, and burnout rates climb faster than in hospital-based roles.
What the Numbers Don't Capture
Pathology has one of the lowest malpractice exposure rates among physicians. That's a structural advantage that affects compensation indirectly. Insurance costs for pathologists run a fraction of what surgeons pay. Some smaller hospitals factor this into their compensation models by offering slightly lower base salaries with the expectation that lower liability risk reduces overhead. It's not universal, but it's a real dynamic in private group negotiations. The rise of digital pathology and telepathology has created a new income tier that didn't exist fifteen years ago. Companies like Proscia, Paige, and various telepathology platforms pay pathologists for remote slide review, especially for intraoperative consultations and subspecialty second opinions. This isn't full-time equivalent work but side income that some attendings layer on. A pathologist doing 10 to 15 hours per week of teleconsults might add $40,000 to $80,000 annually depending on the contract rate and volume available in their subspecialty. Billing and coding complexity in pathology is genuinely misunderstood by outsiders. The CPT code structure for surgical pathology versus cytopathology versus special stains creates real revenue differences. A lab that properly captures add-on codes for immunohistochemistry, fluorescence in situ hybridization, and molecular diagnostics can generate substantially more revenue from the same case volume than a lab that bundles everything. Pathologists who understand the coding side and advocate for proper billing can meaningfully impact departmental revenue, which translates to their own compensation in employed or partnership settings. I had a colleague who learned the coding nuances and renegotiated his contract after realizing the hospital was under-coding several of his subspecialty procedures by roughly 12 percent. That alone increased his share by about $35,000 a year.
Get the Full Details

The Downsides and Where the Model Breaks
Pathology compensation models have real weaknesses. The productivity-based system favors high-volume urban centers with academic referrals and complex cases. Rural and community hospital pathologists who manage broader diagnostic responsibilities with fewer subspecialty referrals often see their wRVU numbers suppressed not because they're working less, but because the cases they handle carry lower relative values. This is a structural inequity that doesn't get discussed enough. Another bottleneck is the ceiling on procedural volume. Unlike surgical specialists who can increase income by scheduling more operative cases, a pathologist's output is constrained by the throughput of the lab and the referring physician population. There's only so many biopsies you can read before you start missing details. The marginal revenue of an extra case drops off quickly when accuracy is the product. The administrative burden is also increasing. Quality metrics, peer review requirements, CAP accreditation documentation, and turnaround time pressures all eat into productive hours without always showing up in compensation calculations. Many pathologists report that the effective hourly wage, when you factor in paperwork and meetings, is significantly lower than the salary figure suggests. A $320,000 salary spread across 2,200 work hours plus another 300 hours of unseen administrative work drops the real hourly rate into uncomfortable territory compared to the advertised number.
If you're evaluating compensation in this field, the most honest approach is to look at total annual compensation packages rather than base salary alone. Signing bonuses, RVU productivity thresholds, call pay, and benefit valuation can shift the picture dramatically. A $290,000 salary with modest bonuses and minimal call might net less than a $310,000 position with strong wRVU incentives and structured overtime. The reverse is also true, and some contracts bury poor incentive structures behind attractive base numbers. The field isn't going anywhere. Chronic shortage of pathology residency slots and an aging attending workforce mean demand will stay elevated through at least the next decade. That provides negotiating leverage for new graduates but doesn't automatically translate to higher pay unless they choose the right practice model. The single biggest determinant of your actual earnings will be whether you enter a high-volume private or reference lab setting, pursue a procedural subspecialty, and learn to navigate the billing structure rather than treating it as someone else's problem.