Why Your Revenue Cycle Keeps Falling Apart
I spent three years managing revenue cycle operations at a mid-sized health system in Ohio, and the thing that kept me up at night wasn't the clinical side. It was the gap between patient access registration and the final dollar hitting the bank. Everyone talks about the revenue cycle like it's a linear pipeline, but anyone who has actually worked in this space knows it is a tangled mess of handoffs, missing data, and departments that refuse to talk to each other. The real work happens in the shared service center model, where you consolidate functions that used to live in silos across different facilities. Parallon operates these shared service centers for healthcare systems that want to centralize patient access, billing, collections, and denial management under one roof. The theory sounds solid. The reality is more complicated. I worked with a system that migrated to a Parallon-style model and within six months their days in accounts receivable dropped from 58 to 41. That sounds great until you dig into what actually changed and what broke in the process. Let me walk you through how this model works, what goes wrong, and what I learned doing it.
Parallon Shared Service Center Patient Access Billing Collections Denials Solving The Revenue Cycle Puzzle
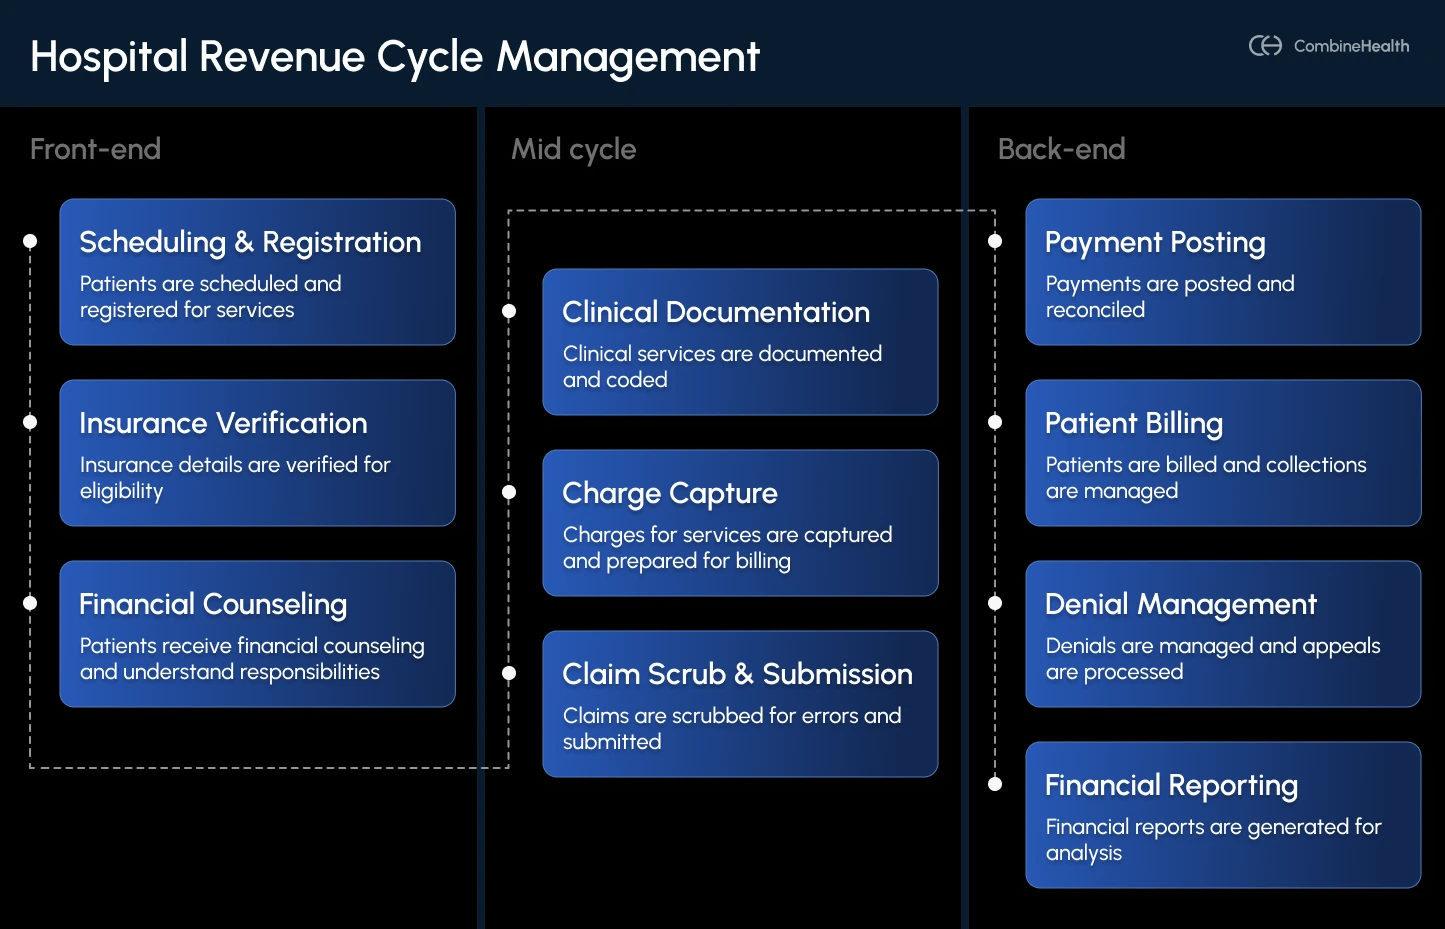
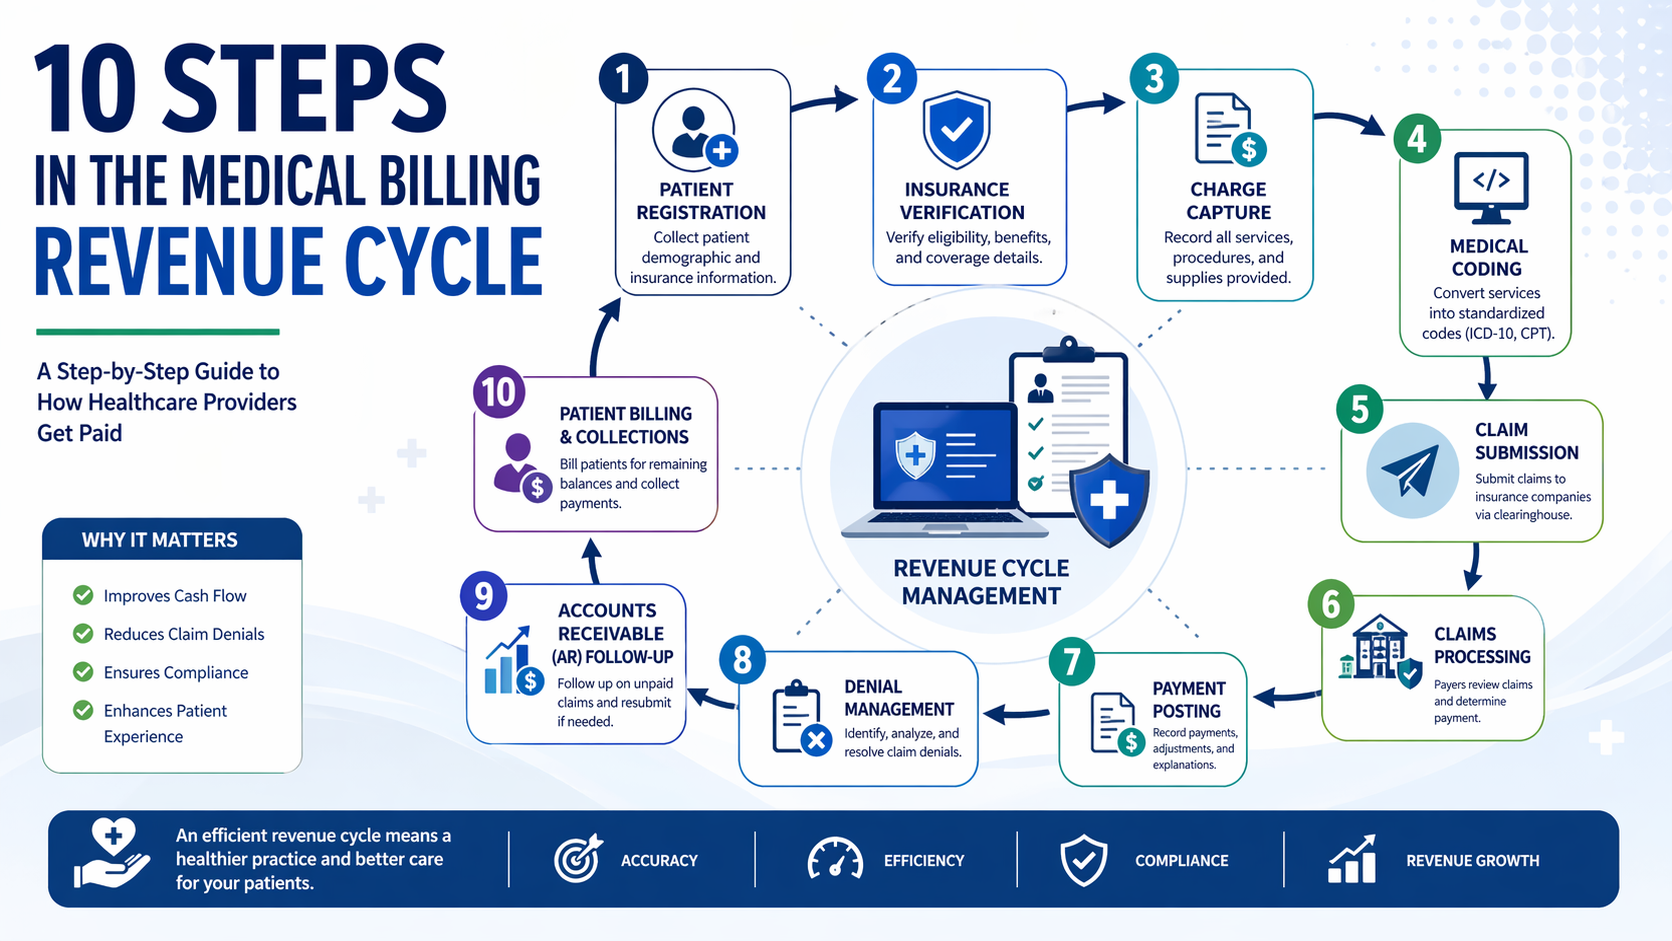
This is the core concept everyone is trying to solve. You have four functions that are supposed to flow into each other but rarely do. Patient access captures demographic and insurance data at the front end. Billing translates clinical encounters into claims. Collections chases unpaid balances. Denials management fights rejected claims. When these functions operate in separate buildings with separate management and separate incentives, information gets lost at every handoff. A shared service center tries to put all four under one operational umbrella. The shared service center model consolidates these functions into a single facility or virtual team. Instead of having registration clerks at ten different hospital campuses and billing staff scattered across three regions, you bring them together. Some companies like Parallon provide this as a managed service. Others build it in-house. The structure matters less than the integration, which is where most systems fail.
How Patient Access Feeds Everything Else
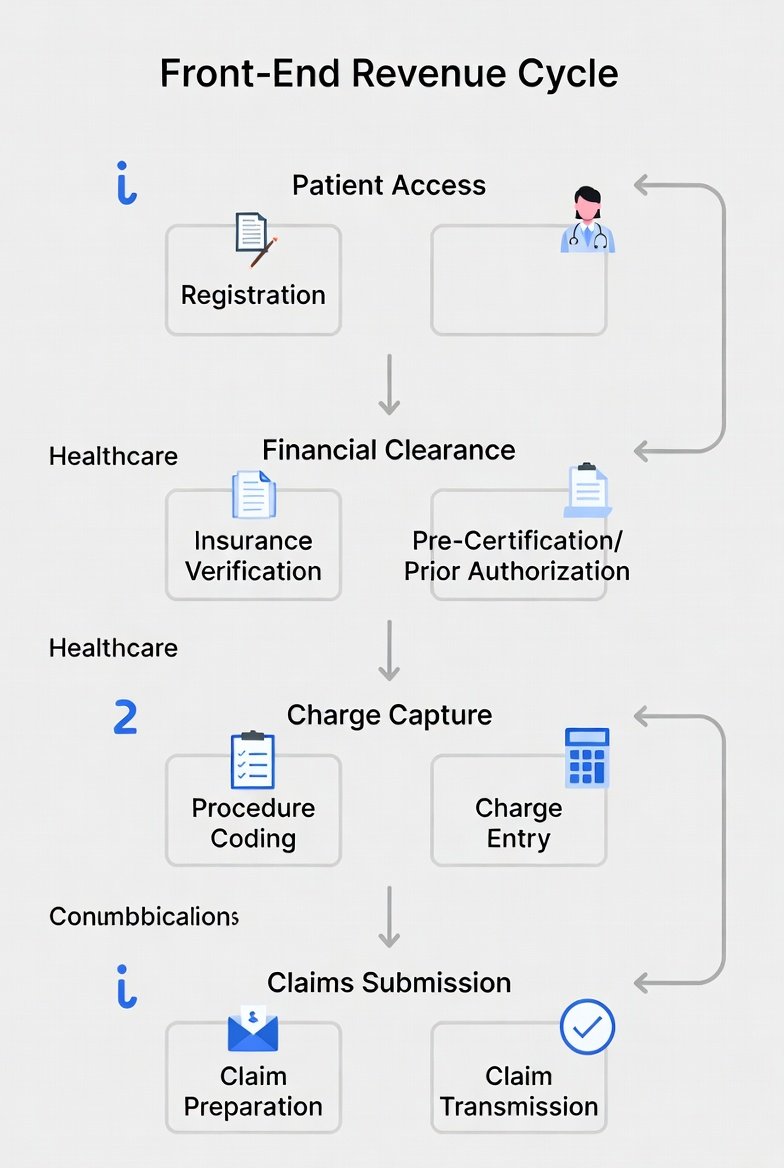
I cannot stress this enough based on actual experience. The quality of your revenue cycle is determined before the patient ever sees a clinician. Bad registration data creates bad claims, which create denials, which create collection attempts on amounts that were never properly captured. At my last organization, we tracked registration errors for six months and found that 23 percent of all denials could be traced back to demographic or insurance verification mistakes made at the point of scheduling or check-in. A shared service center addresses this by standardizing the patient access workflow across all touchpoints. One registration protocol instead of twelve. One training program instead of scattered in-services. Real-time insurance eligibility checks embedded into the registration interface rather than left to individual front desk discretion. This sounds basic but most healthcare systems I have worked with did not have consistent eligibility verification before the visit even started. The edge case that nearly broke our implementation involved self-pay patients who presented with no insurance information and were registered under a default payer code. The billing team processed claims against Medicaid assuming eligibility based on zip code, which generated a denial wave of approximately 400 claims per week. The workaround I implemented required a mandatory financial counseling touchpoint at registration for any patient without verified insurance, with a clearly documented self-pay or charity care designation before the encounter could be finalized. This added about 90 seconds to each registration but eliminated the denial wave entirely.
Get the Full Details
Billing in a Consolidated Environment
When you consolidate billing into a shared service center, the immediate benefit is coder and biller availability. Instead of losing coverage during vacation and sick leave because each location had one billing person, you have a bench of trained staff. The challenge is that billing accuracy depends on clinical documentation quality, and a shared service center billing team often has no visibility into the clinical encounter that generated the charge. I learned this the hard way when our consolidated billing team started seeing a spike in modifier abuse denials from a specific payer. The issue was not with the billers. It was with surgeons at one campus who had developed a habit of appending incorrect surgical modifiers that the local billing staff had been correcting informally without updating the official charge description. Once billing moved to the shared center, those informal corrections stopped. The fix was requiring pre-bill documentation review for any claim with multiple procedural modifiers, which caught the pattern within two weeks. Revenue cycle transparency is another practical benefit. A centralized billing function means you can run denial analytics in real time instead of waiting for monthly reports from individual facilities. You can see which payer is denying what, which service line is generating the most rework, and which registration errors recur most frequently. This data visibility is what makes the shared service center model worthwhile rather than just a cost-cutting exercise.
Collections After Consolidation
Collections is the function most people misunderstand in revenue cycle management. It is not about harassing patients into paying. It is about creating multiple reachable touchpoints across the payment journey, from pre-service estimates to post-service follow-up. A shared service center allows you to standardize the patient communication strategy instead of having ten different approaches across different facilities. Our collections team at the shared center implemented a tiered outreach model. Tier one was automated statements and text reminders within seven days of service. Tier two was a live agent call within fourteen days. Tier three was financial assistance screening for accounts past thirty days. The critical detail was that tier three triggered a referral back to patient access to verify whether the patient's insurance situation had changed since registration. This closed the loop between collections and the front end, which is something most standalone billing departments never do. The counter-intuitive insight here is that external debt collection agencies often recover less money than an in-house shared service center team. I saw this repeatedly. When you hand an account to a third-party collector, you lose the ability to screen for financial assistance eligibility, you lose the context about the patient's history, and you destroy any remaining patient relationship. Our in-house collections recovered 34 percent of accounts sent to agency-level partners versus 18 percent for accounts the agency handled exclusively. The difference was mostly from patients who qualified for charity care but never applied because they did not know the option existed.
Denial Management as a Central Function
Dedicated denial management is where the shared service center model shows its clearest advantage. When denial resolution lives within a billing department, denials get handled as individual claims that need fixing. When it lives in a shared service center, you start seeing denial patterns across the entire system. This is the difference between treating symptoms and diagnosing the disease. I built a denial root-cause analysis framework that categorized every denial into one of five buckets: registration error, authorization failure, medical necessity, coding discrepancy, or timely filing. After ninety days of categorizing roughly 2,000 denials, the distribution was clear. Thirty-one percent were registration errors, twenty-two percent were authorization failures, eighteen percent were medical necessity, fourteen percent were coding discrepancies, and fifteen percent were timely filing. The actionable insight was that eighty-five percent of denials were preventable with front-end process changes. The problem was that the people making those process changes sat in different buildings from the people experiencing the denials. The shared service center puts all four functions in the same operational family, which means the denial team can communicate directly with the registration team about what errors they are seeing. At our center, we held a weekly huddle between denial analysts and patient access leads. This single meeting reduced repeat denials from the same error source by approximately 60 percent over six months. The meeting took twenty minutes. No elaborate reporting structure. Just people who understood the problem talking to each other regularly.

What Breaks in This Model
I need to be straightforward about the limitations because nobody writing about this model talks about them. The shared service center approach fails when the organization treats it as a cost reduction tool rather than a process integration tool. If you move billing and collections to a shared center but keep patient access and denial management scattered across facilities, you have not solved anything. You have just created a new bottleneck at the bottom of the funnel. The second failure mode is staff culture. People who have worked in a specific facility's billing department for years develop relationships with the clinicians and coders at that location. When you consolidate those functions, you lose those informal communication channels. A biller who knows the coding preferences of a specific surgeon can catch documentation issues before they become denials. A consolidated team does not have that knowledge initially. We lost approximately 12 percent of our pre-consolidation denial rate recovery during the first six months because those informal relationships were gone and the formal ones had not yet formed. A third limitation is technology integration. A shared service center only works if all facilities feed into the same revenue cycle platform with consistent charge capture and claim submission workflows. I worked with a system that attempted consolidation while operating three different EHR platforms across its campuses. The shared service center spent more time reconciling data format differences than actually improving revenue cycle performance. In that case, a phased approach would have been better. Consolidate one facility at a time with standardized technology before expanding.
Implementation Steps That Actually Work
If you are considering this model, start with a process audit rather than an organizational chart change. Map every revenue cycle handoff across your current facilities and identify where information is lost. At our system, the biggest gap was between patient access scheduling and clinical registration. Patients scheduled with one insurance plan and checked in with a different plan because the scheduling system did not require insurance verification at booking. Moving billing to a shared center did not fix this because the problem occurred before billing ever touched the account. Phase two should focus on technology standardization. All facilities need to feed into the same claim scrubbing and denial management platform. If you have multiple billing software systems, consolidation will create more work than it solves. This is the step most organizations skip because it requires budget approval and change management that leadership is reluctant to fund. Skip it anyway and the shared service center will struggle. Phase three is the staffing model. Hire or assign a revenue cycle director who has authority over patient access, billing, collections, and denial management. Not a liaison who meets monthly with four separate directors. A single person responsible for the entire flow. Without this accountability structure, each function will optimize for its own metrics rather than the overall revenue cycle. Billing will minimize claim rejections without caring about registration quality. Collections will maximize cash recovery without caring about patient satisfaction. Denial management will appeal aggressively without addressing the root causes that registration could prevent.
Measuring Whether It Actually Works
The metrics that matter are days in accounts receivable, clean claim rate, denial rate by category, first-pass resolution rate, and net collection rate. Track these monthly at the consolidated level, not individually per function. A shared service center that shows improvement in billing efficiency but deterioration in patient access quality is not improving the revenue cycle. It is just moving the problem upstream. At our organization, we measured success by the correlation between registration error rates and denial rates. When registration errors went down, denials went down proportionally. This correlation existed before consolidation but was much weaker because the billing team had no incentive or visibility into registration quality. After consolidation, the correlation strengthened significantly because the same operational team was accountable for both. That is the actual value proposition of the shared service center model. Not cost savings from headcount reduction. Accountability for the full cycle from scheduling to final payment. The model works when you treat it as an integration strategy rather than a consolidation strategy. The people doing the work matter less than the flow of information between them. A well-integrated two-person team outperforms a consolidated fifty-person team that still operates in functional silos. Focus on the handoffs, not the headcount, and the revenue cycle puzzle starts solving itself.