
What Pa In Medicine Actually Means
Pa in medicine stands for Physician Assistant. It is a licensed medical professional who practices medicine as part of a team with physicians. The title has evolved over the years, and you will still hear people say "physician associate" because the American Academy of Physician Assistants changed the preferred terminology in 2022. Both are correct. Both refer to the same role. The abbreviation Pa or PA appears on hospital badges, in clinical documentation, and in prescription pads. The profession exists in a gray space that confuses people who are not inside healthcare. You are not a doctor. You are not a nurse. You are something else entirely, and understanding what that means requires looking at how the role actually functions day to day rather than reading a textbook definition.
Pa In Medicine What Does It Stand For The Definitive Guide To The Physician Assistant Profession
I spent seven years working as a PA in emergency medicine before moving into procedural specialties. The first time a patient asked me directly whether I was "just a doctor," I realized how unclear the public understanding really is. Here is what I learned about the role that no brochure ever explained. Becoming a PA requires completing a master's degree from an accredited physician assistant program. These programs typically run two to three years. They include classroom instruction in anatomy, pharmacology, pathophysiology, and clinical medicine, followed by supervised clinical rotations across multiple specialties. You rotate through internal medicine, surgery, pediatrics, obstetrics and gynecology, emergency medicine, and psychiatry. That breadth is intentional and it is one of the key differences between PAs and physicians. After graduation, you must pass the PANCE, the Physician Assistant National Certifying Exam. This is a computer-based test with over 200 multiple-choice questions. The pass rate hovers around 85 percent for first-time takers. Once you pass, you apply for state licensure. Requirements vary by state. Some states require additional jurisprudence exams. Some have specific application windows. I know this because I watched a cohort mate get stuck in limbo for four months waiting on a single state board to process paperwork that should have taken two weeks.
Maintaining certification requires 100 hours of continuing medical education every two years and recertification every ten years. The NCCPA also requires a continuous certification portal where you log CME credits and pay annual fees. It is tedious but straightforward if you stay on top of it.
Get the Full Details
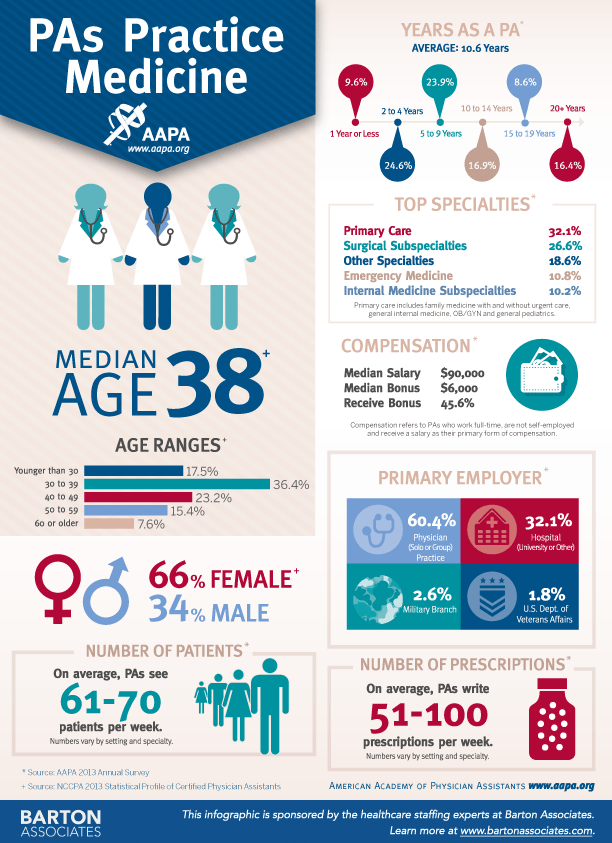
Scope of Practice: What You Actually Do
Your scope of practice depends on three things: state law, your individual certification, and your employing physicians' delegation. In most states, PAs can diagnose illness, develop treatment plans, prescribe medications, and perform procedures. The specifics matter more than the general statement. In California, for example, PAs have fairly broad practice authority with supervising physician requirements that have loosened significantly over the past decade. In New York, the rules are more restrictive and the supervision structure is tighter. I worked in a state with moderate restrictions, and the difference in daily workflow was noticeable. In loose-restriction states, you might independently manage a clinic panel. In tight-restriction states, every note might need a co-sign and every prescription route through a supervisor. Procedural PAs do things like intubate, central line placement, lumbar punctures, joint injections, wound repairs, and assisting in surgery. Medical PAs spend more time on history taking, physical exams, ordering and interpreting labs, and chronic disease management. The split between these two tracks depends entirely on where you work and what your attending allows.
The Reality No One Talks About: Supervision Dynamics
Here is a counter-intuitive point that newcomers never expect. The quality of your practice depends far more on your working relationship with your supervising physicians than on any regulation. I have seen PAs in states with restrictive supervision laws practice with enormous autonomy because their attendings trusted them. I have also seen PAs in permissive states hamstrung by micromanaging physicians who insisted on co-signing everything including routine lab orders. The workaround I developed after my first year was simple and brutal. I documented everything meticulously. Every assessment, every plan change, every conversation with the attending. When the medical record is clear, there is less room for someone to second-guess your clinical reasoning. It sounds obvious but most PAs do not do this consistently until they get burned. I learned this the hard way during my second year. A resident challenged a treatment decision I had made for a community-acquired pneumonia patient. The attending agreed with the resident. My documentation of the patient's response to initial therapy, the culture results, and the rationale for switching antibiotics was detailed enough that when we pulled the chart for a quality review, the attending had to concede the decision was appropriate. That moment shaped how I approach documentation for the rest of my career.
Compensation and Career Trajectory
PA salaries vary widely by specialty, geography, and setting. As of 2024, the national median sits somewhere between 120,000 and 135,000 dollars annually. Surgical subspecialties and procedural roles tend toward the higher end. Primary care and pediatric PAs often sit on the lower end. Rural positions sometimes offer signing bonuses and loan repayment assistance that urban positions do not. Location matters enormously. A PA making 115,000 dollars in a rural Midwest town has a very different life than a PA making 115,000 dollars in San Francisco or New York City. I have seen colleagues move from expensive coastal cities to affordable regions specifically to improve their quality of life without taking a pay cut. The math works in their favor.

Pitfalls and Limitations
The PA profession has real limitations that get glossed over in recruitment materials. Burnout is significant. The workload in hospital-based positions can be crushing, especially in emergency departments and intensive care units. Patient volume expectations are high. Administrative burden from EHR documentation eats into time that should be spent on actual patient care. There is also the ambiguity problem. You are qualified to do many things but not everything. You cannot independently practice medicine in the way a physician can. You cannot close a residency and become an attending physician in your own right. If you hit a ceiling on autonomy and want full independent practice authority, the path is longer and more expensive than staying on the PA track. Insurance reimbursement is another practical issue. Some payer contracts reimburse PAs at a lower rate than physicians. This affects hospital economics and sometimes creates tension between PAs and physician colleagues about revenue generation. It is a structural issue that individual PAs cannot change.
How to Decide If This Is the Right Path
If you want direct patient care, enjoy procedural work or diagnostic reasoning, and do not want to commit to the seven to ten year training pipeline of medical school, the PA route makes sense. It is faster to train. It is less expensive in terms of debt. You enter clinical practice sooner. If you need full autonomous practice authority, want to lead a department, or are drawn to the deep specialty training that comes with residency, you should consider medical school instead. The PA role is not a compromise for people who could not get into med school. It is a distinct profession with its own value proposition. Treating it as a backup plan will hurt you and the patients you work with. I have worked alongside PAs who chose this path deliberately and with clear-eyed understanding of what it entailed. They were excellent clinicians. I have also worked alongside PAs who treated it as a waiting room for a physician career they never pursued. The difference was visible in their work quality and their satisfaction levels. Know what you are signing up for before you enroll in a program.


