What Actually Happens When Your Ear Scleroses
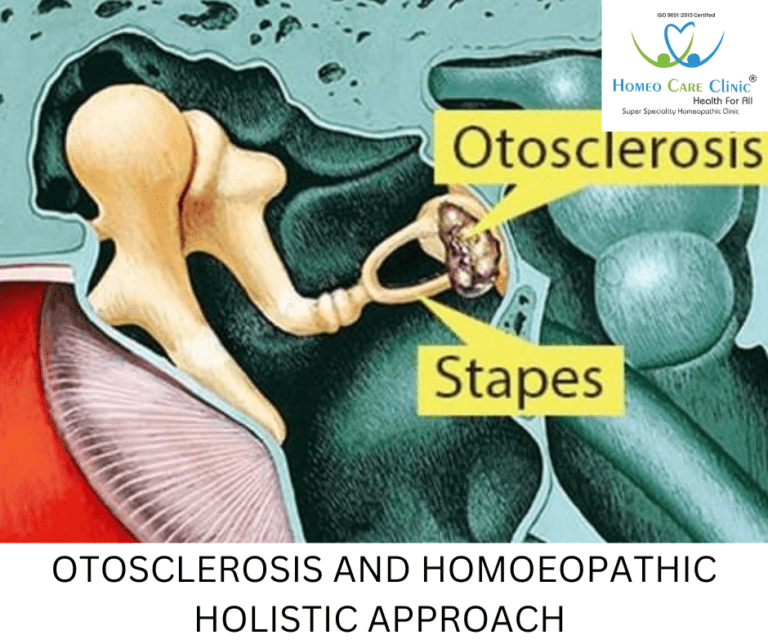
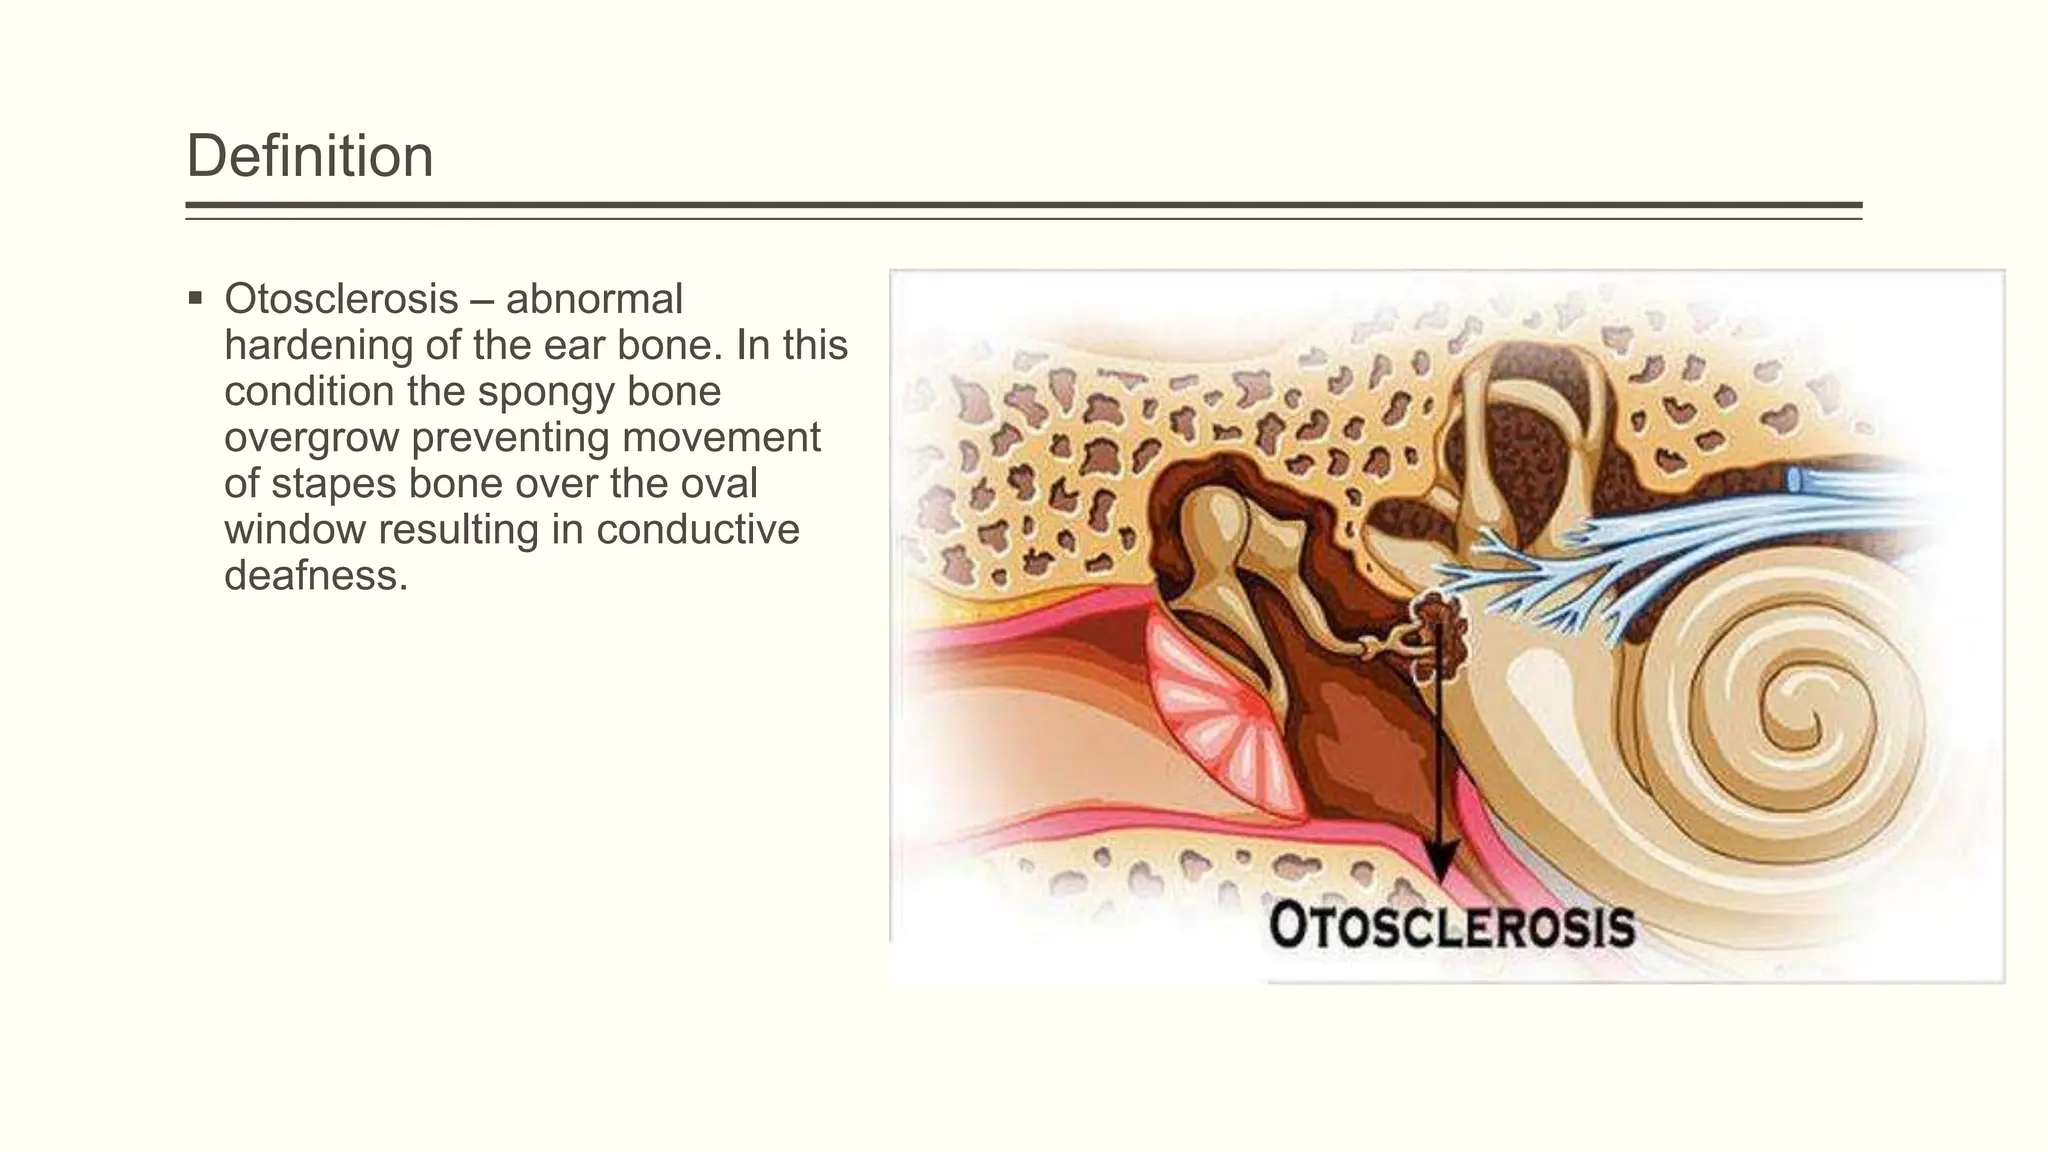
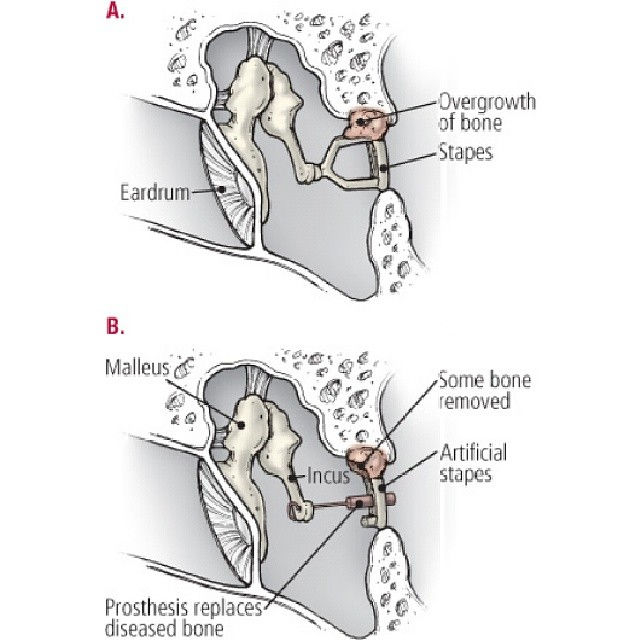
Otosclerosis is a localized bone disorder in the middle ear where normal bone gets replaced by abnormal spongy bone. The most common presentation is fixation of the stapes footplate, which prevents proper sound transmission from the middle ear to the inner ear. It's conductive hearing loss at its core, though mixed loss appears when the disease invades the cochlea. I've seen patients who'd been told they needed hearing aids for years, only to find out their ossicular chain was simply stuck. The fix wasn't amplification, it was mechanical. That's the thing people miss early on.
Otosclerosis Understanding The Condition And Its Treatment Options
The first step is getting the diagnosis right. Pure tone audiometry showing a air-bone gap is the hallmark. Bone conduction usually stays normal unless cochlear involvement is present. Tympanometry typically shows a type As curve because of that stiff ossicular chain. Stapes gush sign during ear examination isn't common but when it's there, it's fairly specific. The real pitfall I keep running into is misdiagnosing it as simple age-related hearing loss or noise-induced loss. Younger patients with unexplained conductive loss need a high index of suspicion. A family history shows up in about sixty percent of cases, and it's autosomal dominant with incomplete penetrance. Women flare worse during pregnancy, which is probably hormonal but nobody's figured out the exact mechanism.
The Surgical Fix
Stapedotomy is the standard procedure now. You make a small window in the vestibule directly and place a prosthesis through it. The old stapedectomy where you removed the entire superstructure is largely gone. Stapedotomy has better outcomes and lower complication rates. Success rates hover around ninety percent for closing that air-bone gap to within ten decibels. One edge case I dealt with recently was a patient whose facial nerve was dehiscent over the stapes. Standard surgical approach was risky because the nerve was sitting right where you'd normally work. I ended up approaching through a transcanal route with a microscope and doing a very careful fenestration medial to the otosclerotic focus. The key was identifying the nerve first with intraoperative nerve monitoring. That patient's gap closed to seven decibels post-op and she avoided facial nerve injury.
Get the Full Details
Non-Surgical Routes
Not everyone is a surgical candidate. Sodium fluoride therapy is worth mentioning because most general practitioners don't know about it. The theory is that fluoride stabilizes the active spongy phase of the disease and slows progression. The typical dose is forty to sixty milligrams of elemental fluoride daily with calcium supplementation. It doesn't reverse existing loss but it can arrest progression in active cases. The evidence is mixed but it's an option worth discussing with someone who isn't operating on them. Hearing aids remain the fallback for people who decline surgery or have mixed sensory-neural loss from cochlear involvement. A standard aid won't help much if the issue is purely conductive, but modern devices with high-gain options can bridge the gap reasonably well. Bone conduction devices are another angle if the outer or middle ear anatomy is unfavorable.
What Actually Goes Wrong
Complications from stapes surgery are uncommon but real. Perilymph fistula happens in maybe one to two percent of cases. Sensorineural hearing loss is the scary one, occurring in roughly one in a thousand procedures. Face nerve injury is rarer still. Round window rupture can happen if you lose your landmark anatomy, which is why preoperative CT imaging matters in revision cases or atypical presentations. The recurrence rate after stapedotomy sits around five percent. Some of that is new otosclerotic focus formation, some is prosthetic displacement. Revision surgery is harder because of scar tissue and altered anatomy. Don't get complacent after the first procedure.
Bottom Line
Otosclerosis is manageable but it's easy to overlook in younger patients. The conductive component is often reversible with surgery if caught before cochlear damage sets in. Get a thorough audiologic workup, consider fluoride if the disease is active and you're not operating, and understand that surgery carries real though low risks. The prognosis for most patients is genuinely good, but only if someone actually checks for it in the first place.