Injection Administration: IV vs IM Techniques
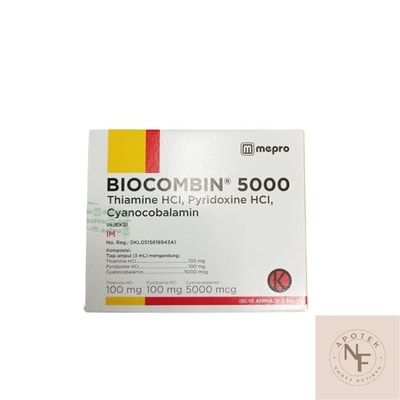
I've spent over fifteen years in clinical practice, and administration of injectable medications remains one of those fundamentals where people cut corners too often. Let me walk through what actually matters when you're working with intravenous or intramuscular routes. When you're reading about injection methods, particularly for products like Biocombin injections, the critical detail most guides miss is that the technique varies significantly depending on whether you're going IV or IM. These aren't interchangeable approaches, and confusing them can lead to serious complications. Intramuscular injection requires understanding the anatomy. The deltoid, vastus lateralis, and ventrogluteal sites each have different absorption rates and comfort levels. For IM administration, you want a 90-degree angle, quick dart-like motion through the subcutaneous tissue, and aspiration before injecting in most cases. The needle length matters enormously here—a 1-inch needle might work for a lean adult's deltoid, but you'd need 1.5 inches for ventrogluteal injection in most patients.
I remember a specific case where someone mixed up the recommended dilution for a particular B-complex injection product. They administered it IM when the formulation was designed for IV use, and the patient developed a sterile abscess that required drainage. The lesson: always verify the manufacturer's specifications for route-specific preparation.
The Practical Differences
IV administration demands sterile technique at a higher level. You're introducing the medication directly into the bloodstream, which means no absorption barrier, immediate bioavailability, but also immediate systemic exposure if there's an adverse reaction. The preparation time is longer—typically 5 to 10 minutes for proper site assessment, tourniquet application, and vein stabilization. With IM injections, absorption is slower but more predictable. The medication depot forms in the muscle tissue and releases gradually. This is why IM is often preferred for certain vitamin B complexes and other formulations where rapid onset isn't necessary or where the medication might irritate veins. One thing beginners consistently underestimate is the angle of insertion for thin patients. A standard 90-degree approach might penetrate too deeply and hit periosteum, causing significant pain. In those cases, a 45-degree angle for deltoid injection in emaciated patients prevents bone contact while still delivering into the muscle belly.
Get the Full Details

Common Pitfalls to Avoid
Aspiration before IM injection remains controversial in some recent guidelines, but for certain medications, particularly those that might be accidentally injected into a blood vessel, aspiration is still recommended. The technique is straightforward: after needle insertion, pull back on the plunger slightly for 5 to 10 seconds. If blood appears, withdraw and restart with a new site and needle. Another frequent error is injecting too rapidly. For IM administration, the general rule is no more than 1 mL per site in adults, and injection should take at least 10 seconds for each milliliter. Rapid injection causes tissue damage and increased pain. With IV push medications, the rate varies by drug, but rushing any injection increases complication risk without benefit. Site rotation matters more than most practitioners acknowledge. Repeated injections into the same area cause fibrosis and scar tissue formation, which alters absorption characteristics and increases discomfort. I typically recommend documenting injection sites and rotating systematically through available locations.
Preparation Details That Matter
Temperature of the medication affects comfort significantly. Refrigerated B-complex solutions cause considerable discomfort when injected at cold temperature. Letting the vial reach room temperature for 15 to 30 minutes before administration reduces pain without affecting stability for most formulations. Z-track technique for IM injection prevents medication leakage into subcutaneous tissue. This involves displacing the skin 2 to 3 centimeters lateral to the injection site before needle insertion, then maintaining that displacement until 10 seconds after withdrawal. It's particularly important for irritating medications and certain vitamin formulations. Needle gauge selection depends on viscosity. For thin aqueous solutions, a 25-gauge needle is typically comfortable, but thicker suspensions might require a 21 or 22-gauge needle to prevent excessive pressure and tissue trauma during injection. Trying to force viscous medication through a narrow needle increases pain and can cause tissue damage.
The real difference between competent and careless administration shows up in patient outcomes. Proper technique reduces complications, improves compliance, and makes the process safer for everyone involved. It's worth spending the extra time to get it right rather than rushing through what should be a methodical procedure.


