Understanding Why Breathing Gets Harder When You Lie Flat
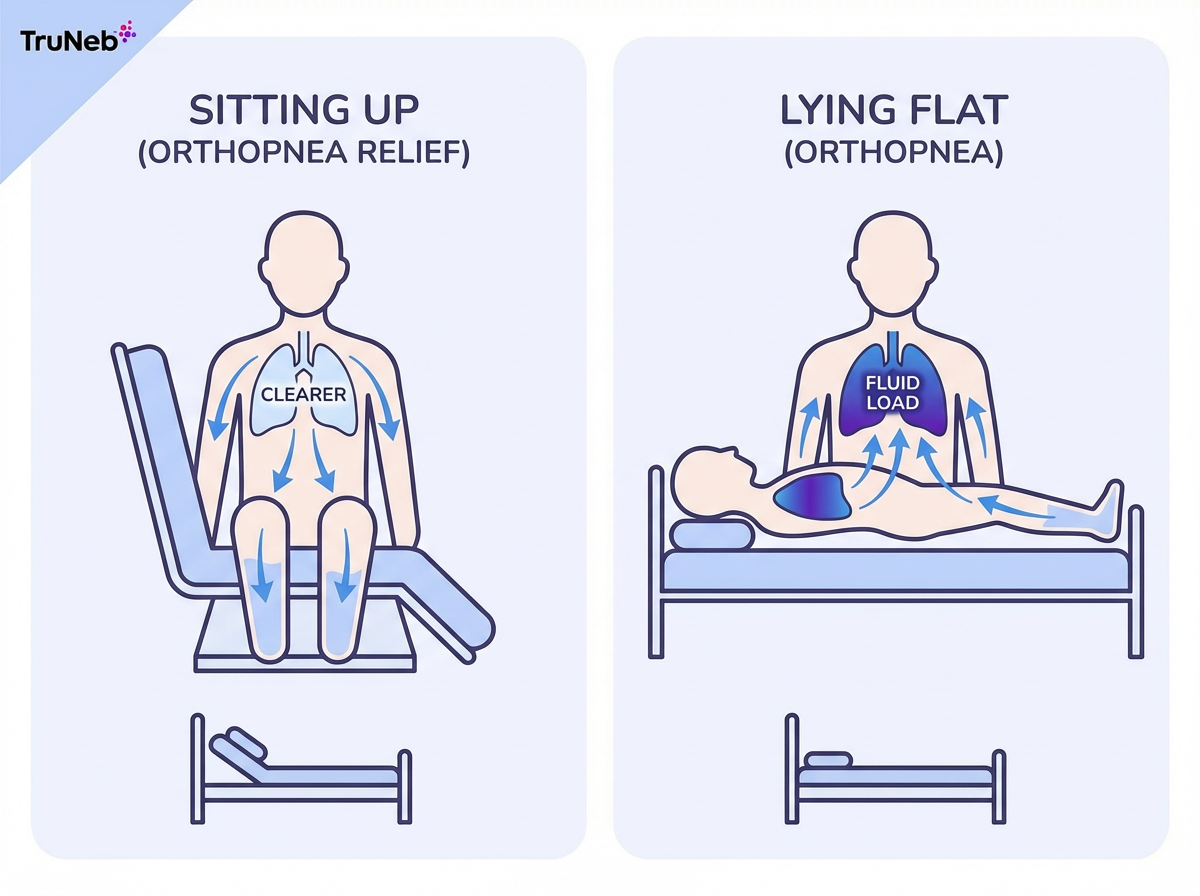
Orthopnea is one of those symptoms that patients describe matter-of-factly without grasping how much trouble it signals. You lie down and suddenly can't catch your breath. You sit up and it eases within minutes. This isn't psychological. It's purely mechanical and hemodynamic, and the physiology behind it is straightforward once you actually think through what happens to blood volume when gravity stops pulling it toward your legs. The primary mechanism is simple. When you're upright, roughly 500 to 800 milliliters of blood pool in the lower extremities and splanchnic circulation due to hydrostatic pressure. Lay flat and that fluid redistributes back toward the central circulation. For a healthy heart, this is no big deal. The heart handles the extra preload, stroke volume adjusts slightly, and nothing dramatic happens. But when the left ventricle is already struggling, that extra volume pushes the pulmonary capillary wedge pressure above a critical threshold, fluid leaks into the interstitial spaces of the lungs, and gas exchange becomes compromised. The result is breathlessness that improves within minutes of sitting upright. I remember one patient who told me he slept in a recliner because his bed felt like it was slowly filling with water every night. He called it acid reflux at first. Turns out he had biventricular heart failure with an ejection fraction in the low thirties, peripheral edema, and orthopnea requiring three pillows just to manage. We started him on a low-dose loop diuretic with a scheduled weight check and his symptom burden dropped dramatically within two weeks. The recliner was a band-aid. The real issue was volume overload the patient was essentially ignoring until it became unbearable.
The Clinical Causes
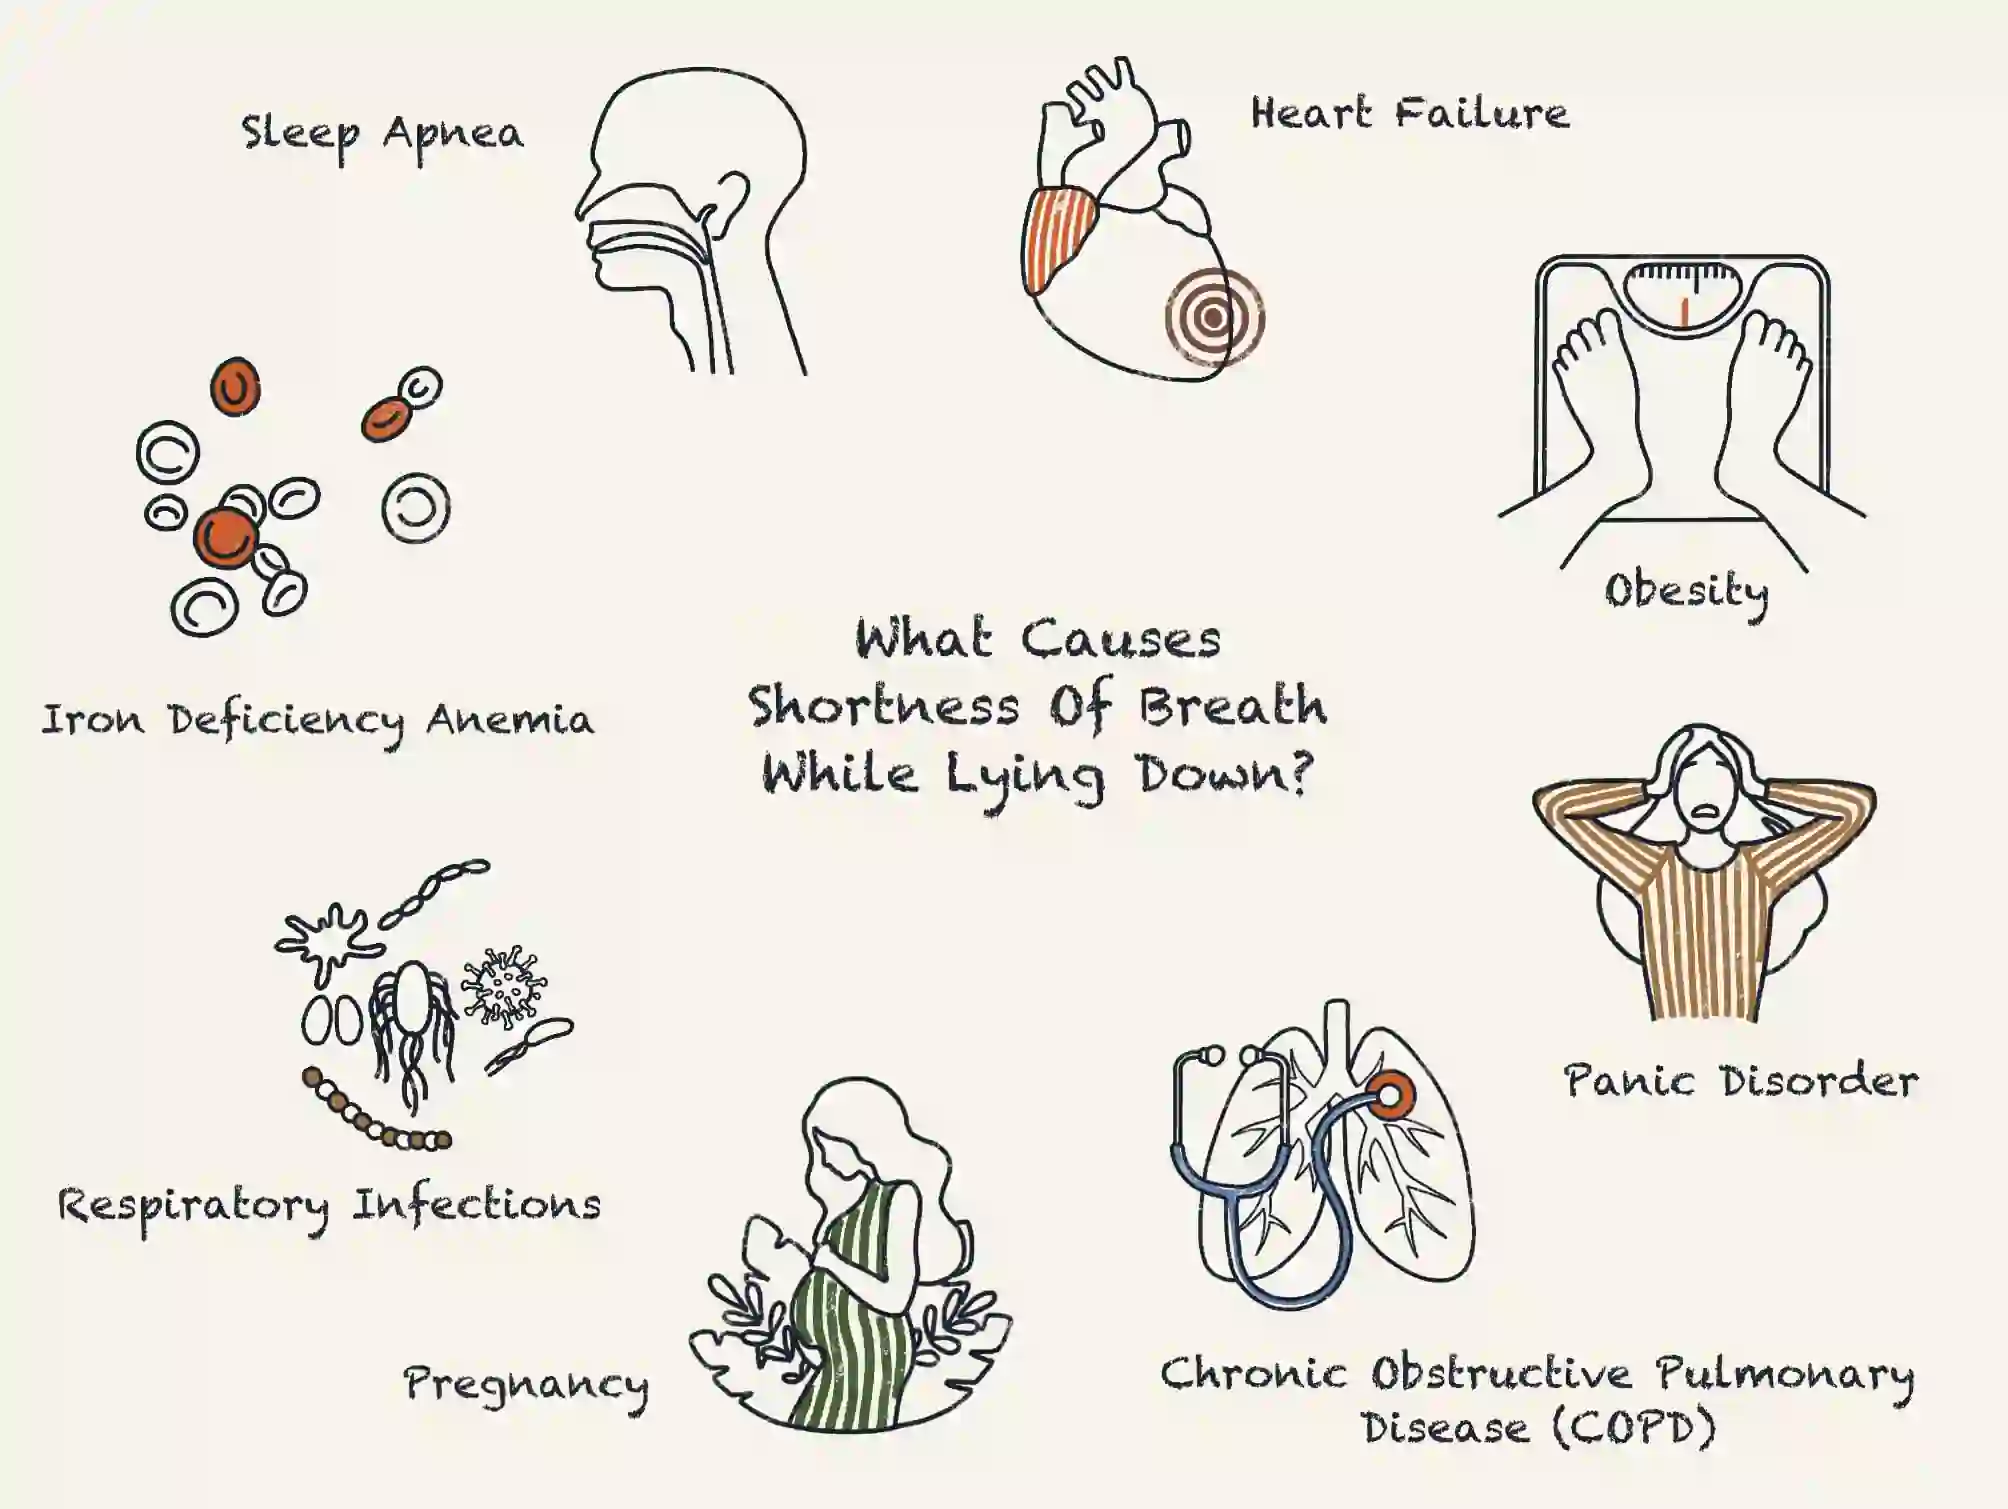
Heart failure is by far the most common cause, particularly left-sided systolic dysfunction. But it's important not to stop there. Any condition that raises left atrial pressure or reduces left ventricular compliance can produce orthopnea. Here are the main categories, listed in order of how often I actually see them in practice. Cardiac causes dominate the picture. Congestive heart failure accounts for roughly 70 to 80 percent of orthopnea presentations in outpatient settings. Aortic stenosis, mitral valve disease, hypertrophic cardiomyopathy, and constrictive pericarditis all reduce the heart's ability to accommodate the venous return that comes with recumbency. Pericardial disease is particularly tricky because the orthopnea here isn't purely about volume overload. It's about restricted filling. Patients with constrictive pericarditis can have relatively preserved ejection fractions but still present with significant orthopnea and elevated jugular venous pressure. The Kussmaul sign, paradoxical septal motion on echo, and a pericardial knock are clues you shouldn't miss if you're evaluating someone who seems to have heart failure with preserved ejection fraction. Pulmonary causes are the second major bucket. Severe COPD and asthma can produce positional dyspnea that mimics orthopnea, though the mechanism differs. In COPD, lying flat pushes the diaphragm upward into a chest cavity that's already hyperinflated. The diaphragm is already flattened and dysfunctional at baseline. Adding abdominal pressure on top of it makes ventilation even less efficient. I've seen patients with end-stage emphysema who couldn't tolerate supine positioning at all, and the only reason wasn't heart failure. It was purely mechanics. Obesity hypoventilation syndrome and severe obesity itself are increasingly common causes too. The weight of the abdomen against the diaphragm in the supine position reduces functional residual capacity significantly. Some of my obese patients needed just a slight head-of-bed elevation and their oxygen saturations improved from 88 percent to 94 percent without any medication change.
Less common but important causes include recurrent aspiration from gastroesophageal reflux, large hiatal hernia compressing the lungs or heart, and neuromuscular conditions like advanced ALS or myasthenia gravis where the diaphragm simply isn't strong enough to handle the positional change. Spinal deformities like severe scoliosis can also limit lung expansion when supine. And in rare cases, pleural effusions cause positional breathing difficulty that isn't true orthopnea but presents similarly enough to confuse the picture.
Get the Full Details

How We Actually Diagnose It
The history is usually sufficient to establish orthopnea. We ask patients how many pillows they need to sleep comfortably. Two pillows or more generally qualifies. The pillow count isn't a perfect metric but it correlates reasonably well with severity. Patients who need to sleep sitting up are in more advanced territory. Physical examination should focus on jugular venous distension, third heart sounds, crackles at the lung bases, and peripheral edema. Liver enlargement and hepatojugular reflux are additional signs of volume overload. If the lungs are clear and there's no edema, you should reconsider whether this is truly cardiac orthopnea or something else entirely. Chest X-ray will show pulmonary venous congestion, Kerley B lines, and potentially cardiomegaly in cardiac cases. Echocardiography is the next step for anyone with suspected heart failure. BNP or NT-proBNP levels help distinguish cardiac from pulmonary causes, though obesity can artificially lower BNP values. Pulmonary function testing with positional measurements can clarify obstructive disease contributions. The paragenic snore test, essentially having the patient record their breathing overnight, occasionally helps differentiate sleep apnea from true orthopnea when the distinction isn't obvious.
I had a case last year where a patient presented with classic orthopnea, elevated BNP, and mild bibasilar crackles. Everyone assumed heart failure. The echocardiogram was normal. The CXR was clear. Turns out the patient had a massive hiatal hernia that was compressing the left atrium when supine. Surgical repair resolved the orthopnea completely. This is why you shouldn't anchor on the first diagnosis that fits, even when the initial workup seems supportive.
Treatment Depends on the Underlying Cause
For heart failure related orthopnea, diuretics are first-line. Loop diuretics like furosemide reduce preload and lower pulmonary capillary pressures. The starting dose matters less than adequate decongestion. I typically start with 40 milligrams of oral furosemide and adjust based on response. Some patients need twice-daily dosing initially. The goal is negative fluid balance until orthopnea resolves and resting weight stabilizes at the patient's dry weight. Gastrointestinal causes require different approaches. Proton pump inhibitors help with reflux-related symptoms. Hiatal hernias may need surgical intervention. COPD management involves optimizing inhaled therapies and ensuring patients aren't smoking. Positional strategies like elevating the head of the bed 30 to 45 degrees provide immediate symptomatic relief while definitive treatment takes effect. Non-adherence to sodium restriction is the single most common reason orthopnea recurs after apparent improvement. I can't stress this enough. Patients will take their diuretics religiously and then consume a high-sodium meal or two and wake up unable to breathe flat again. The sodium retention overrides the diuretic effect within hours. Education about dietary sodium isn't optional. It's part of the treatment.
Red Flags That Demand Urgent Evaluation
New onset orthopnea in someone without a known cardiac history warrants prompt investigation. Paroxysmal nocturnal dyspnea, where the patient wakes up gasping after an hour or two of sleep, indicates more severe volume overload than simple orthopnea. Orthopnea accompanied by chest pain, syncope, or hemoptysis should be evaluated emergently. Unilateral leg swelling suggests possible pulmonary embolism as an alternative or contributing cause. Rapid weight gain of more than two pounds in a day or five pounds in a week alongside worsening orthopnea signals decompensated heart failure that needs aggressive management. There's also a subset of patients where orthopnea doesn't respond to diuretics despite clear volume overload on imaging. This often points toward diuretic resistance, which is common in advanced heart failure. In those cases, adding a thiazide-type diuretic like metolazone for sequential nephron blockade can restore responsiveness. This combination can be quite effective but requires close monitoring of electrolytes and renal function because the potassium and magnesium wasting can be significant. I usually check labs within three to five days after initiating this approach. Orthopnea is a symptom, not a diagnosis. The science behind it is well understood. The challenge is recognizing that it can arise from multiple organ systems and that missing the underlying cause leads to repeated episodes and unnecessary emergency visits. The pillow count is a useful clinical tool, the response to diuretics is informative, and the absence of cardiac findings should push you toward alternative diagnoses quickly rather than spending weeks on a wrong path.