What Actually Happens When the Oregon Medicaid Expansion Funding Gets Messed With
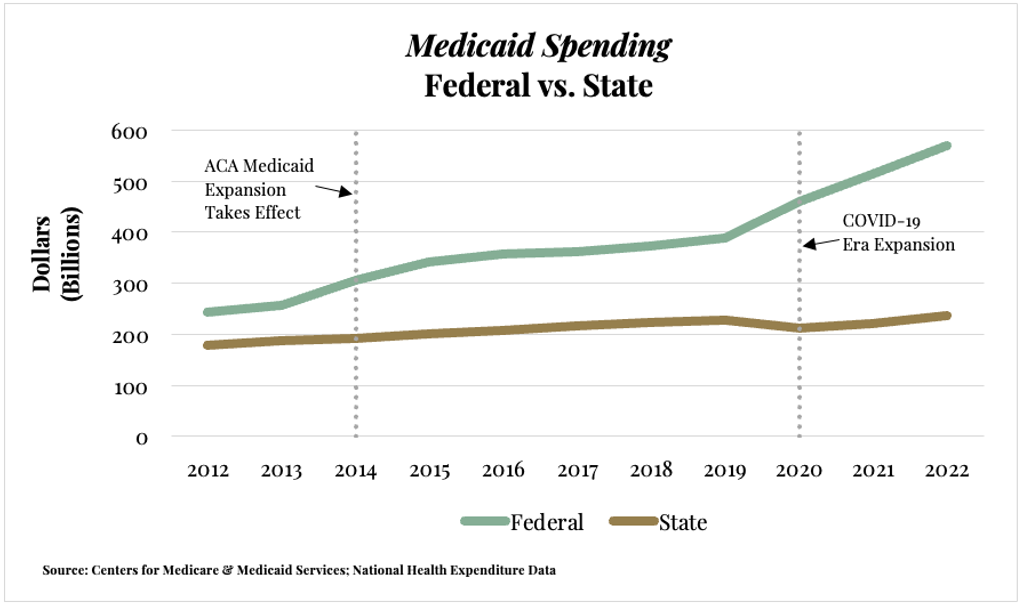
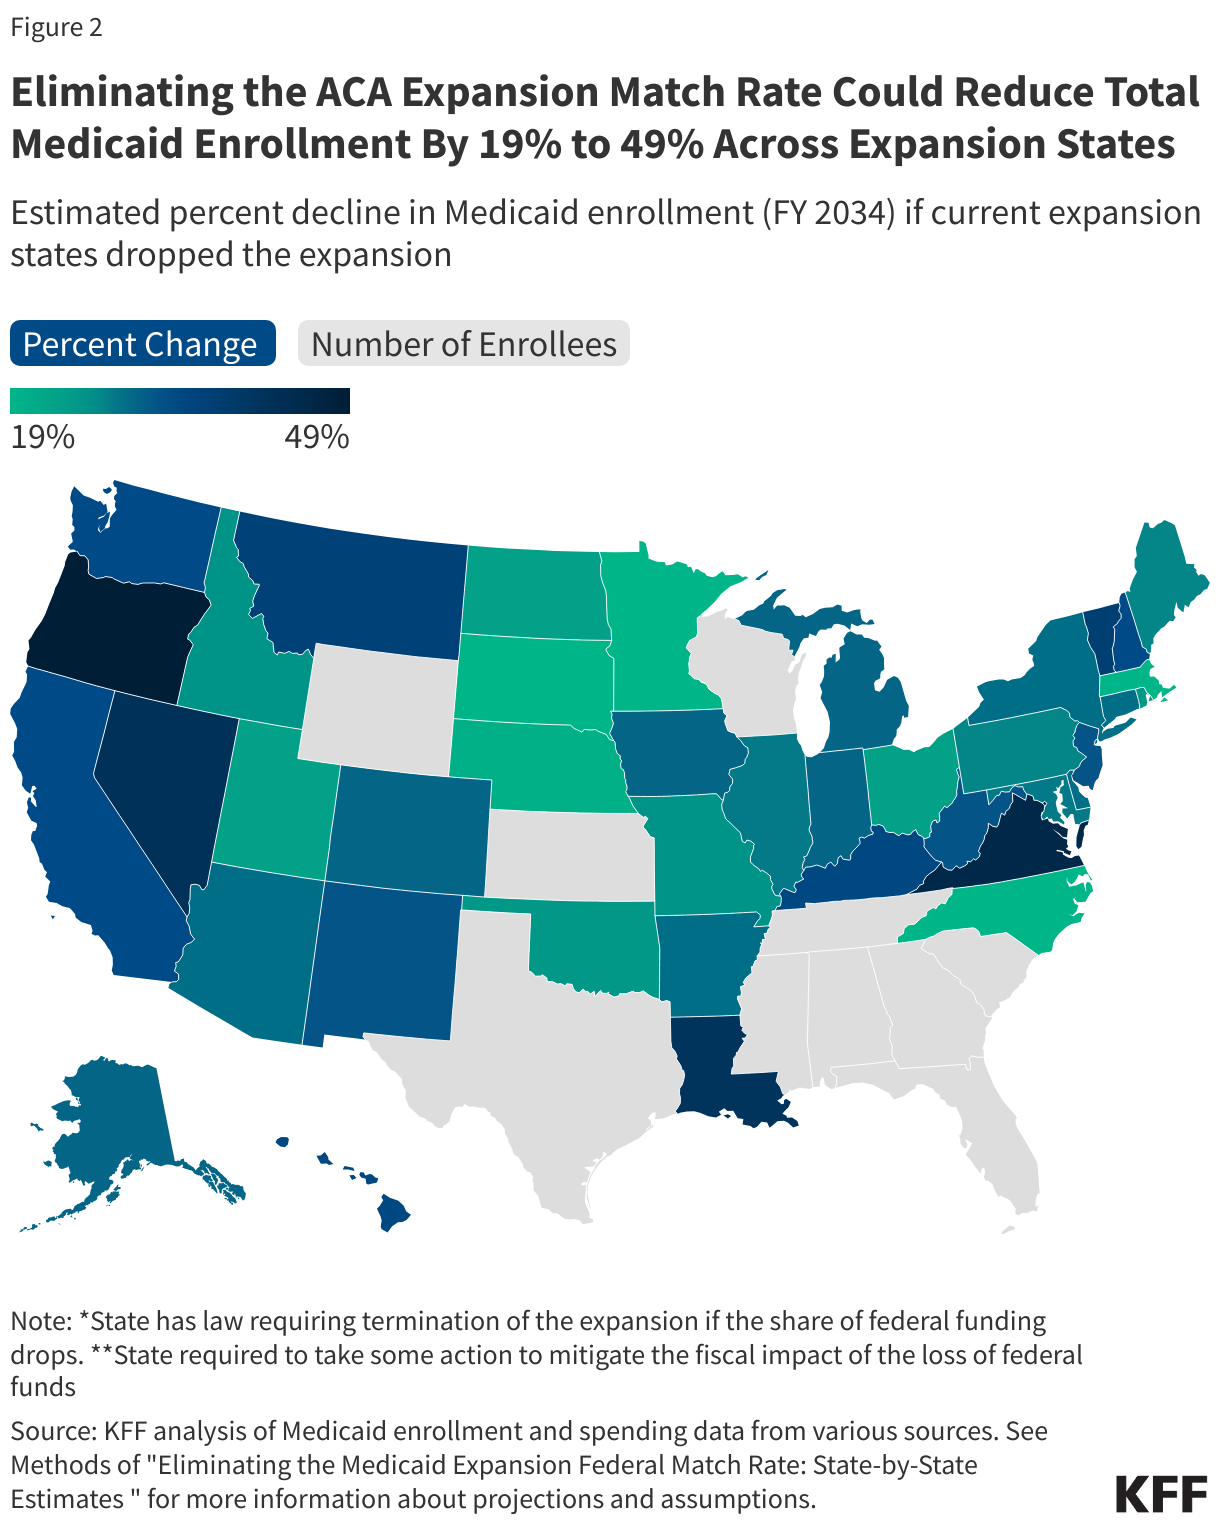
There has been a lot of back-and-forth in Oregon lately about what happens to the state's Medicaid expansion if federal dollars get pulled or reduced. The debate among Oregon health leaders centers on how much coverage would be affected, who would lose insurance, and what the state budget would look like without the current federal matching rate. I have spent years watching these policy discussions play out in real time, and the reality is usually messier than the headlines suggest. The core of the issue comes down to the ACA Medicaid expansion, which Oregon adopted through ballot measure in 2016. Under that expansion, the federal government covers about 90 to 92 percent of the costs for newly eligible enrollees, while the state picks up the rest. That 90/10 split is what made the expansion politically viable for Oregon in the first place. If that federal rate drops — and there have been various proposals over the years that would change it — the math changes fast. When I was working on policy analysis a few years back, I ran into a specific problem with the federal Medicaid match calculations. Oregon has a special situation because of the way the expansion was phased in. The federal rate starts higher and then gradually steps down over a period of years. I kept getting conflicting numbers depending on which federal fiscal year the calculation was anchored to, and the Oregon Health Authority website was not always clear on which year applied. The workaround was straightforward once I figured it out: I stopped relying on the summary pages and went directly to the CMS federal medical assistance percentage tables, then cross-referenced with the Oregon state budget documents that cited specific fiscal years. It took about twenty minutes instead of spending hours going in circles.
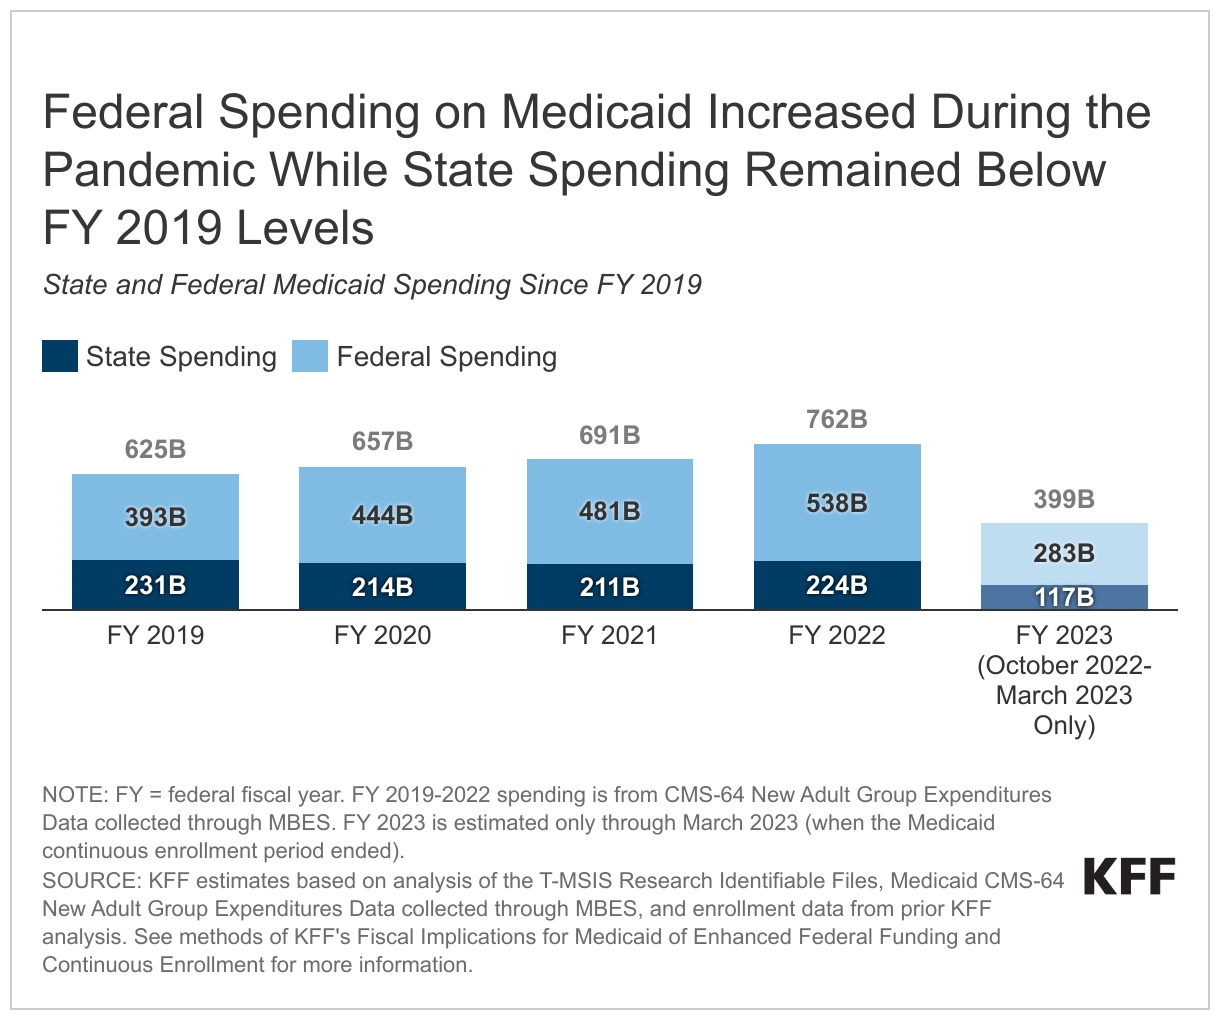
Here is something most people do not realize about this debate. The 90/10 federal share is not just a nice bonus for Oregon. It is structurally embedded in every budget projection the state makes. Hospitals, community health centers, and rural clinics in particular build their financial models around the assumption that expanded Medicaid reimbursement will continue at the current rate. When you cut the federal share even slightly, those institutions do not just absorb the difference. They reduce services or shift costs to privately insured patients, which then drives up premiums for everyone else. The ripple effect is real and it happens within a single budget cycle. Another counter-intuitive thing is that the federal government has occasionally tried to impose work requirements or other eligibility restrictions on Medicaid expansion. Oregon leaders have fought those proposals aggressively, and for good reason. Adding work requirements does not save money in any meaningful way. The administrative cost of verifying compliance, plus the number of people who get dropped from the rolls even when they qualify, ends up costing more than the savings from restricting enrollment. I saw this play out in states that implemented those requirements. The enrollment numbers dropped, but program costs went up because of the added bureaucracy. The federal funding uncertainty itself is the main problem. Oregon has already committed to funding the expansion at the current rate regardless of what happens in Washington. That means if the feds try to change the match or impose new conditions, the state is on the hook either way. The debate among Oregon health leaders right now is less about whether to expand and more about what contingency plans are needed. Options on the table include adjusting the eligibility threshold, redirecting funds from other health programs, or seeking legislative action to protect the expansion from federal changes.
One practical detail that gets overlooked is the difference between the traditional Medicaid population and the expansion population. They are tracked separately in the data, and they respond differently to funding changes. The expansion population is generally healthier and younger, so cutting benefits for that group has different budgetary and clinical consequences than cutting traditional Medicaid. Policy people sometimes conflate the two, which leads to flawed projections. There is also the question of what happens to the unspent federal dollars that Oregon has already committed to on the state side. If the federal rate drops mid-year, the state has already collected premiums and obligated funds based on the original assumption. Those commitments do not simply disappear. The timing mismatch between when the feds announce a change and when it actually takes effect can create a gap where the state is paying more than projected for a full fiscal year before any new rates kick in. If you are following this debate and want to track it yourself, the Oregon Health Authority publishes regular reports on Medicaid enrollment and spending. Those reports are dry but they contain the actual numbers. The federal CMS website has the medical assistance percentage tables that show the official match rates. Cross-referencing those two sources will give you a more accurate picture than any news article will.
Get the Full Details
The bottom line is that the Oregon Medicaid expansion has worked reasonably well under the current funding structure, but it is not self-sustaining if the federal government decides to change the terms. The debate among state leaders is really about how much control Oregon is willing to give up versus how much risk the state budget can absorb. Both sides have valid points, and the outcome will depend on what actually happens in Washington rather than what is currently being proposed.