Understanding Optic Canal Stenosis and Vision Compression
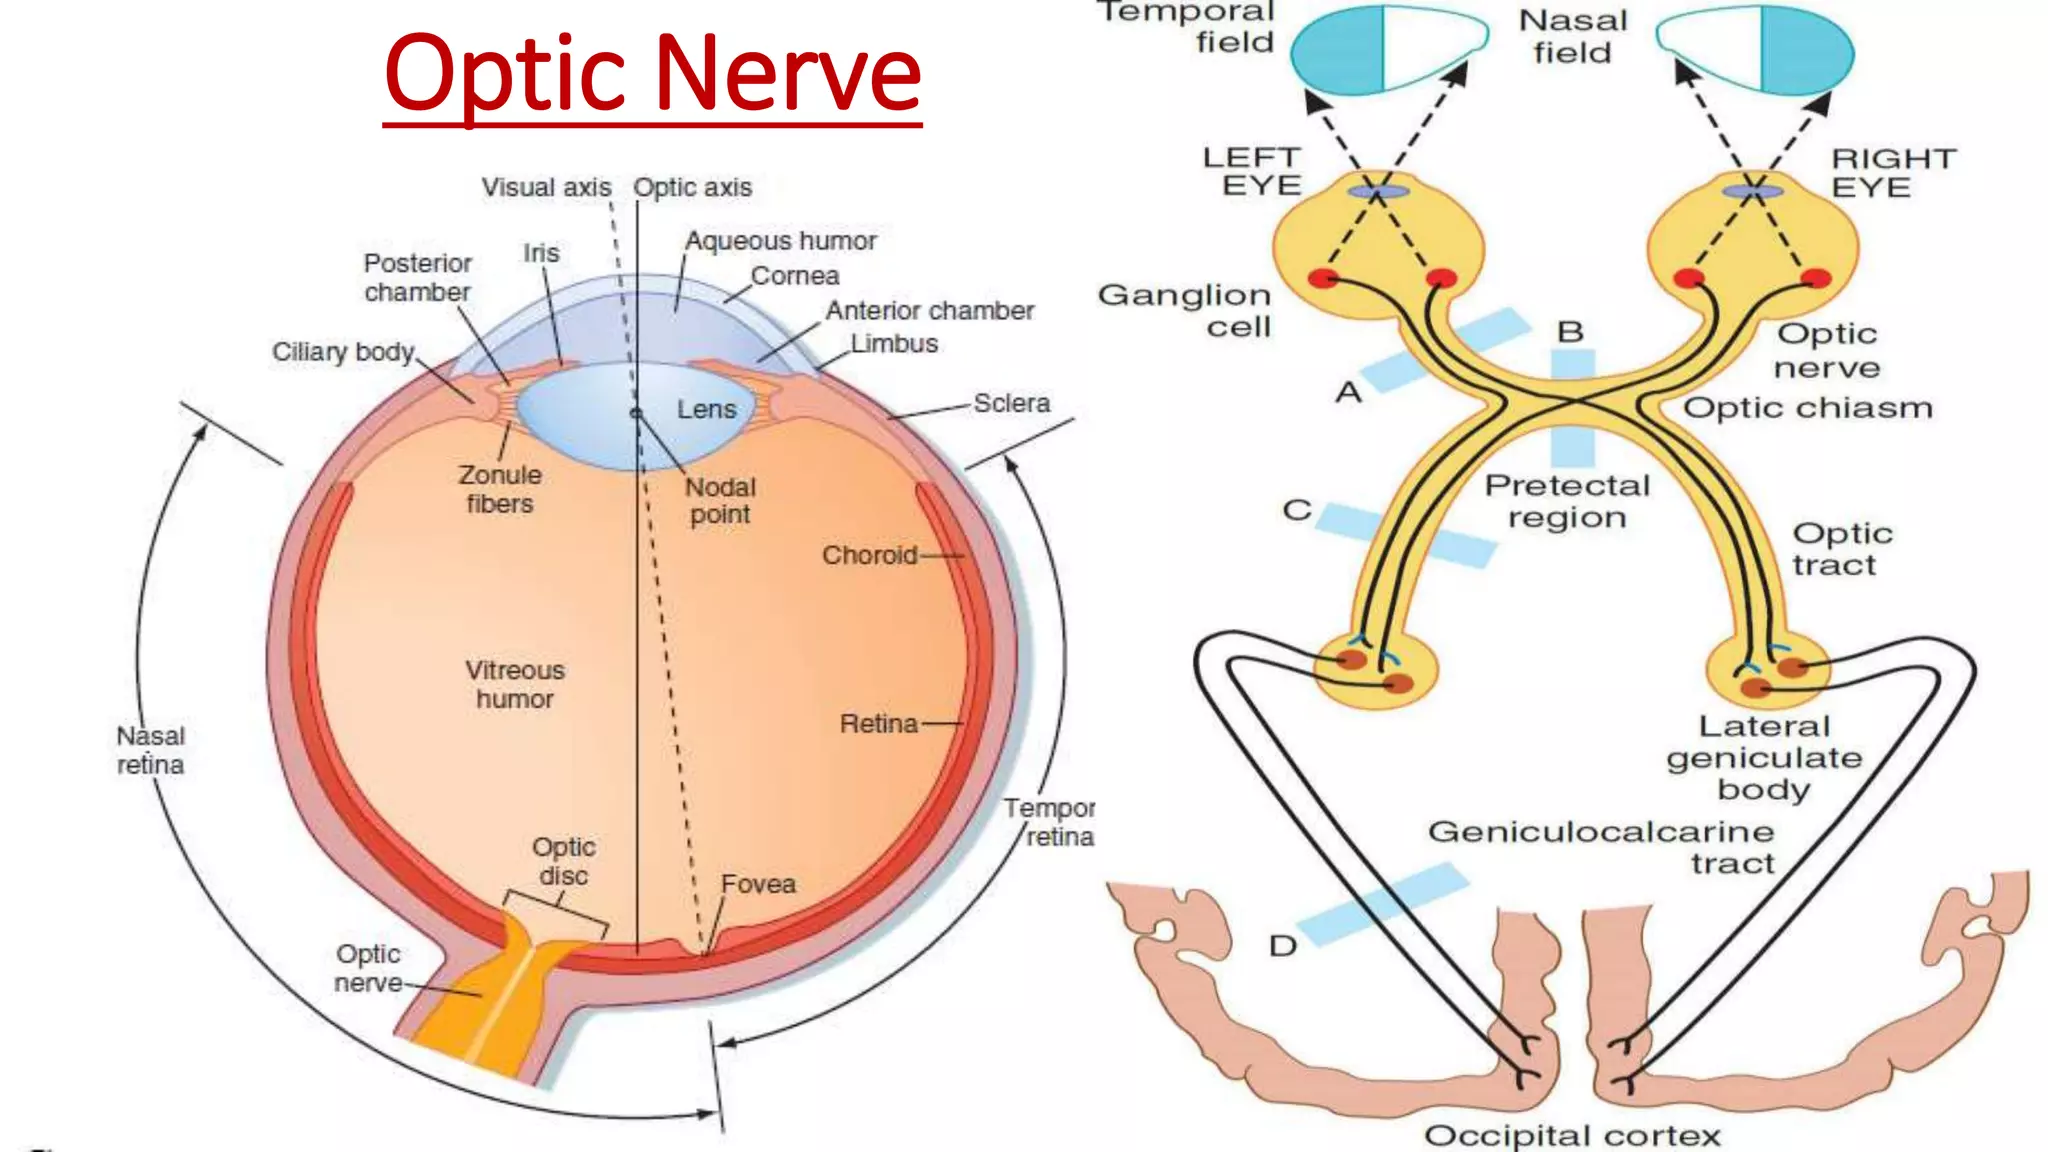
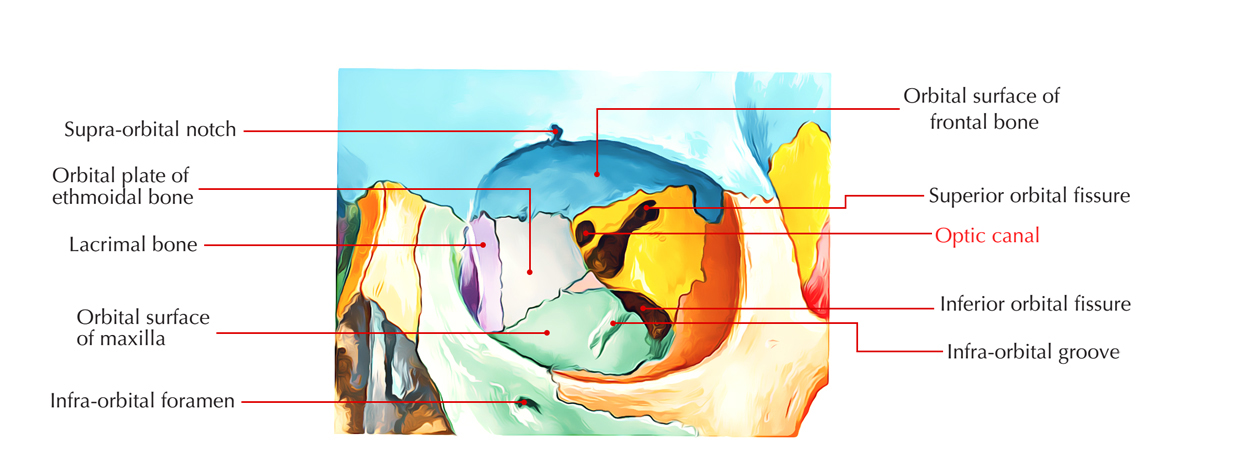
The optic canal is a small bony opening in the sphenoid bone, roughly 7 to 9 millimeters in diameter, that serves as the passageway for the optic nerve and ophthalmic artery. When this space narrows—whether from bone overgrowth, trauma, or a tumor pressing against it—the consequences for vision can be severe and sometimes permanent. I see this come up more often than you'd expect, usually in cases where patients have been misdiagnosed for months because standard eye exams miss the real problem. Pressure on the optic nerve inside that canal is what we call optic canal stenosis when it's bone-related, or compressive optic neuropathy when something else—like a meningioma or aneurysm—is doing the squeezing. The nerve itself doesn't have much room to move. It's tucked tightly inside a bony tube with no give. When that space shrinks even a fraction of a millimeter, intraneural pressure rises, blood flow through the ophthalmic artery gets compromised, and vision starts degrading. It's usually gradual. Patients notice blurred vision, loss of peripheral sight, or a dark spot in one eye and assume it's just aging or screen strain. It isn't. I dealt with a case last year where a 54-year-old woman had been seeing an optometrist for six months for "progressive vision loss." They'd adjusted her prescription multiple times. Nothing helped. She was losing her ability to read road signs while driving. When she finally got a CT scan ordered by an ENT who'd actually listened to her history, we found significant osteoblastic changes narrowing her right optic canal. The bone was growing inward. We worked with neurosurgery and decompressed the canal through an endoscopic endonasal approach. Her vision stabilized but didn't fully return. That's the hard truth about this condition—once the nerve has been compressed long enough to cause axonal damage, recovery is limited. Early detection is everything, and early detection usually requires imaging you wouldn't get from a routine eye exam.
The standard workup starts with visual acuity and visual field testing, but those are late indicators. By the time you see a deficit on a Humphrey perimeter, significant damage may already be present. MRI with contrast is the go-to for soft tissue compression. CT with thin cuts—0.625 millimeter slices through the orbital apex—is essential for evaluating bony stenosis. If you're ordering imaging and only getting a standard orbit CT, ask for dedicated optic canal views. The standard protocol often misses subtle narrowing at the posterior aspect of the canal where the bone is thinnest. Common causes fall into a few buckets. Meningiomas of the tuberculum sellae or planum sphenoidale are the most frequent space-occupying lesions. They grow slowly, often over years, and press on the nerve from the outside. Fractures of the orbital roof or anterior skull base can fragment bone into the canal. Fibrous dysplasia causes abnormal bone growth that encroaches on the space. Thyroid eye disease can cause enlargement of the extraocular muscles that compress the nerve near the canal entrance. Less common but worth knowing: sclerotic metastases from prostate or breast cancer can thicken the canal walls. I once saw a case where a seemingly benign pituitary adenoma was actually a non-functioning macroadenoma causing subtle bony remodeling that nobody caught on the initial scan because they were focused on the gland itself. Surgical decompression is the primary intervention for progressive cases. The two main approaches are transcranial and endoscopic endonasal. The endoscopic route has become the standard for most cases because it avoids brain retraction and has a shorter recovery. But it's not for everyone. If the lesion extends laterally beyond what the surgeon can reach through the nose, or if there's significant vascular involvement, a craniotomy might be necessary. I've seen both approaches work and I've seen both fail when patient selection wasn't careful. One pitfall I want to flag: surgeons sometimes underestimate how much bony removal is needed. The goal isn't to just "make some room." You need to decompress the entire length of the canal where compression is occurring. Leaving even a small band of bone intact can mean the difference between stable vision and continued decline.
Conservative management applies to mild, non-progressive cases. Serial imaging every three to six months, visual field monitoring every three months, and managing any underlying systemic condition. Steroids can help temporarily reduce inflammation around the nerve but they don't treat the mechanical compression. I've watched patients cycle through dexamethasone bursts with temporary improvement, then relapse when the dose tapered. It's a bridge, not a solution, and some patients get stuck on that bridge for months waiting for surgery they should have had earlier. The biggest mistake patients make is assuming vision problems are eye problems. They stay in the optometry and ophthalmology loop for months or years. The optic canal sits behind the eyeball, deep in the skull base. A dilated fundus exam can show optic disc swelling or pallor, which are clues, but they're not diagnostic. The actual compression happens proximal to where most eye doctors look. If you have unexplained progressive vision loss—especially if it's unilateral or asymmetric—and your eye doctor can't find a retinal or refractive cause, push for a neuroimaging referral. Don't accept another prescription change as an answer. Recovery timelines vary. Some patients see improvement within weeks of decompression if the compression was recent. Others plateau quickly and the gains they make are modest. I had a patient whose pre-op visual field had a 40-decibel defect and post-op it dropped to 20 decibels of loss. That sounded like progress on paper but functionally he could barely see anything in that eye. The numbers don't always tell the whole story. What matters is whether the progression has stopped and whether functional vision is stable enough for daily life.
Get the Full Details

There's no prevention for most causes. Genetic conditions like fibrous dysplasia can be identified early with screening if there's family history. Trauma-related stenosis is unavoidable in its acute phase but surgical timing can limit permanent damage. For tumor-related cases, regular imaging surveillance in patients with known skull base lesions is the closest thing we have to early detection. If you've been told you have a meningioma near the optic pathway, don't skip your follow-up MRIs. That's how you catch compression before it becomes irreversible.