Why We Still Use Mnemonics in the ER (And Why OPQRST Actually Matters)
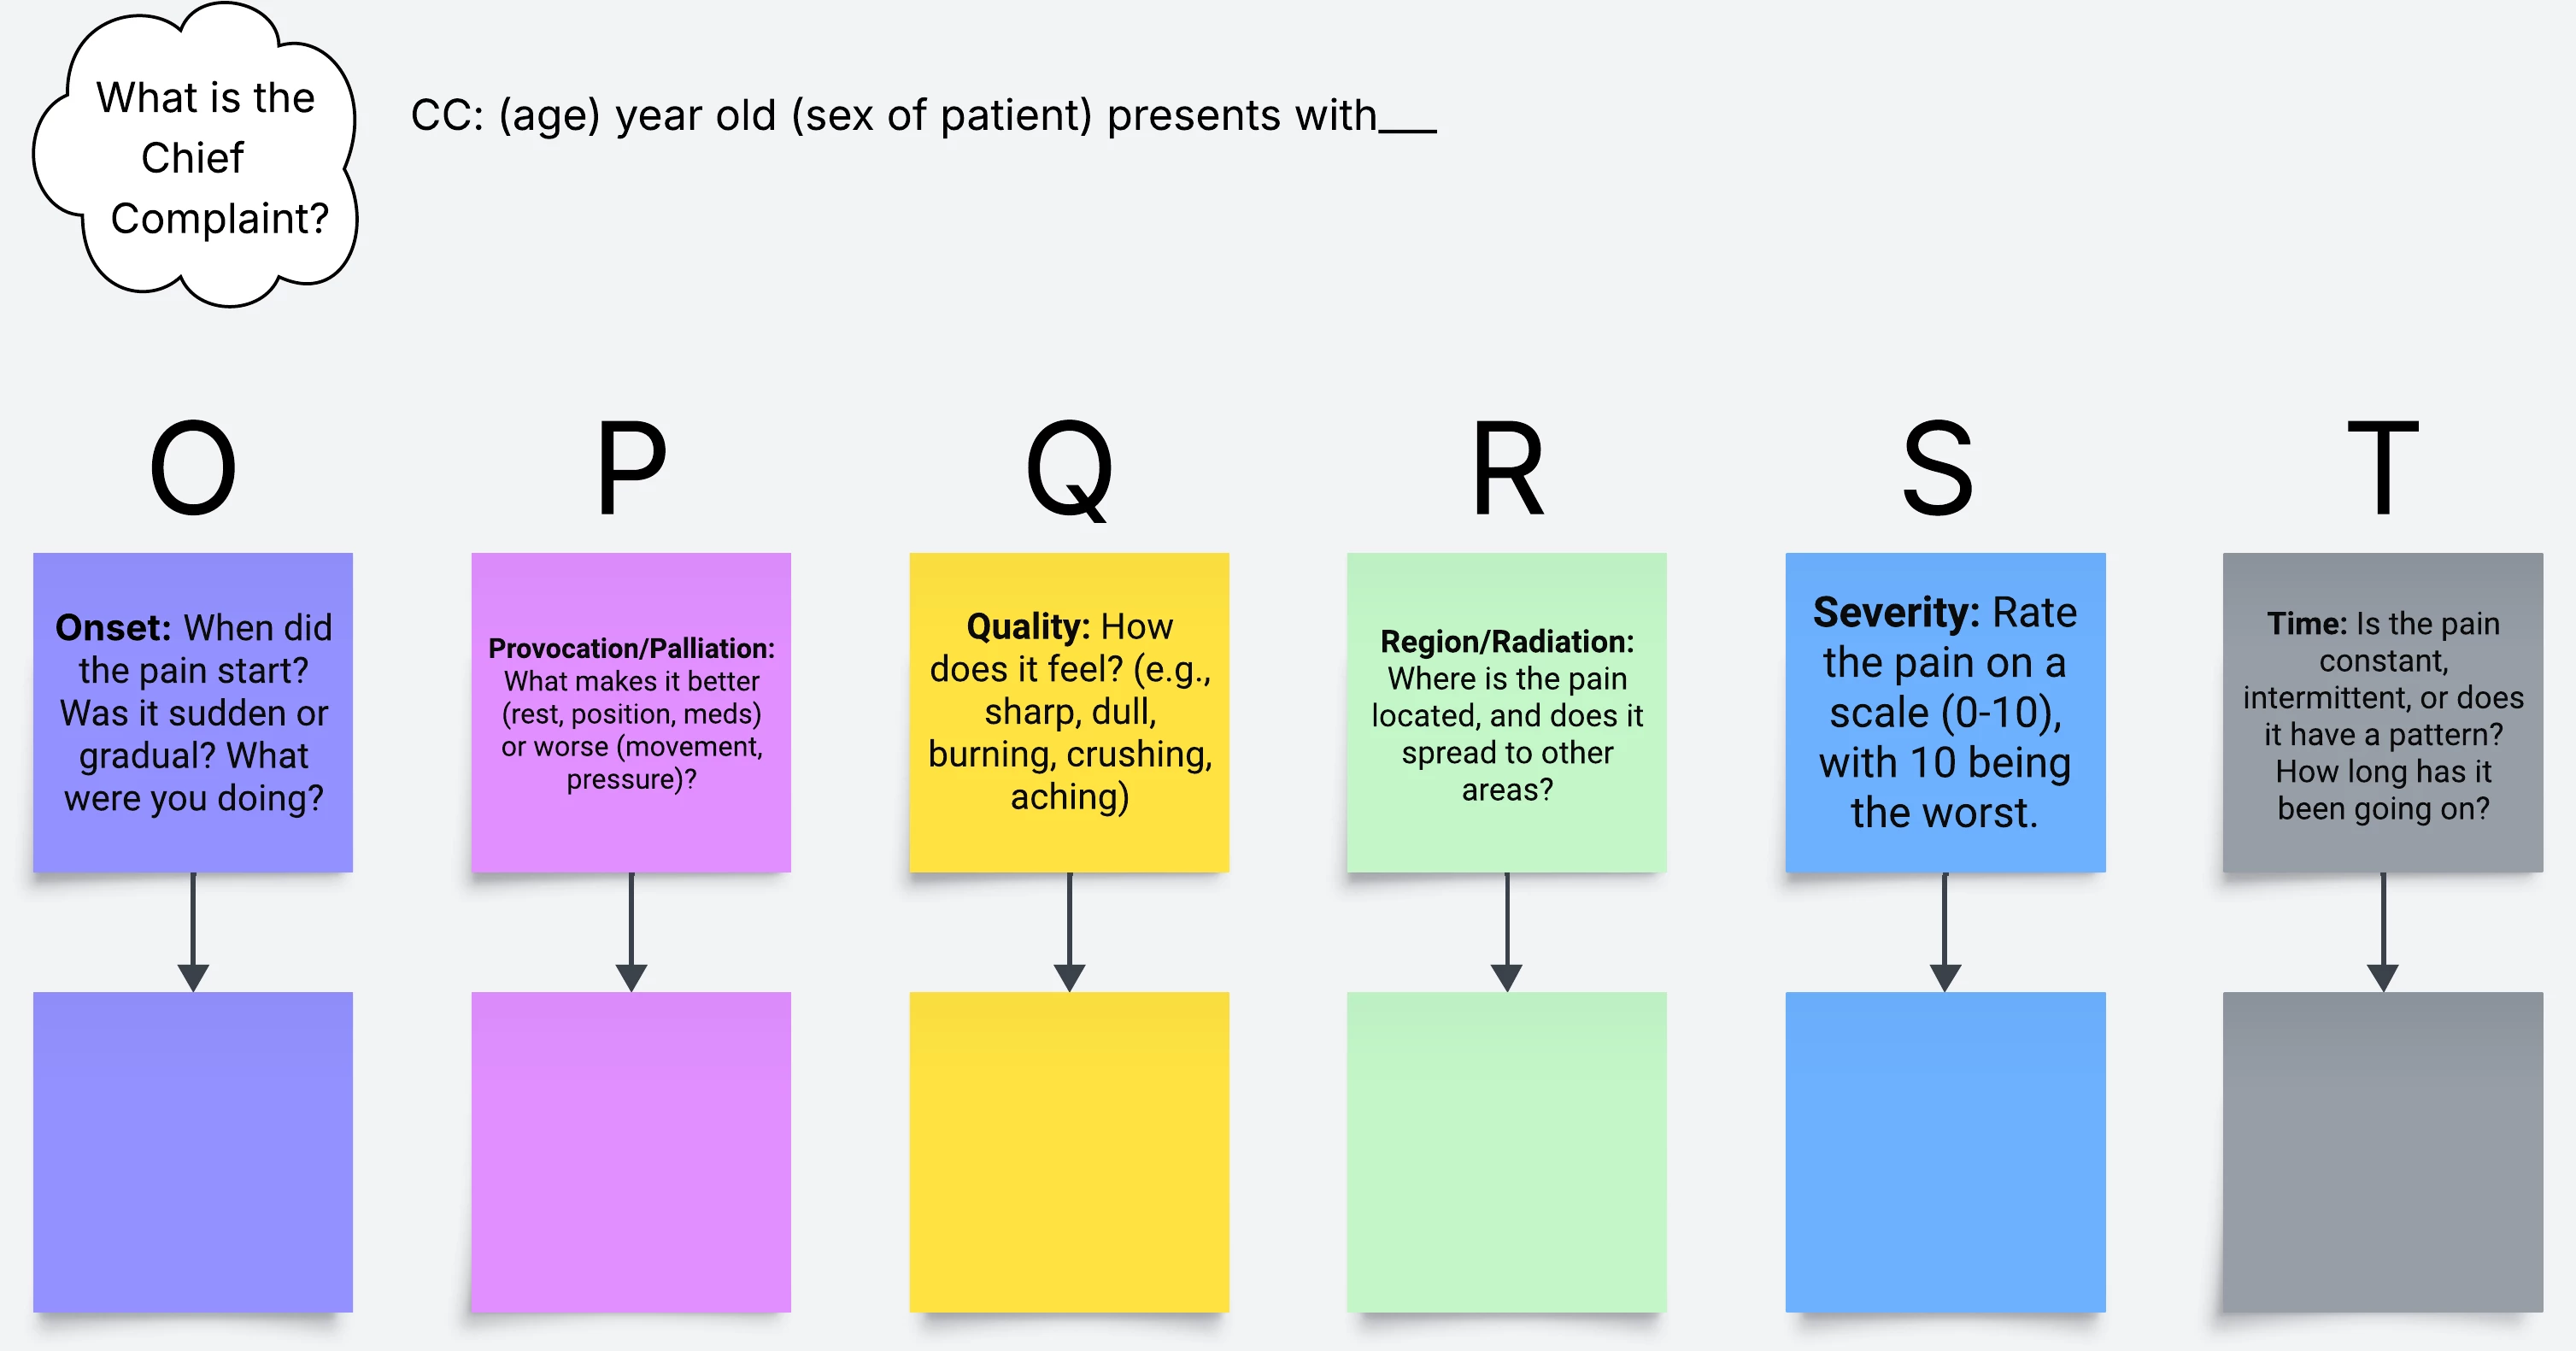
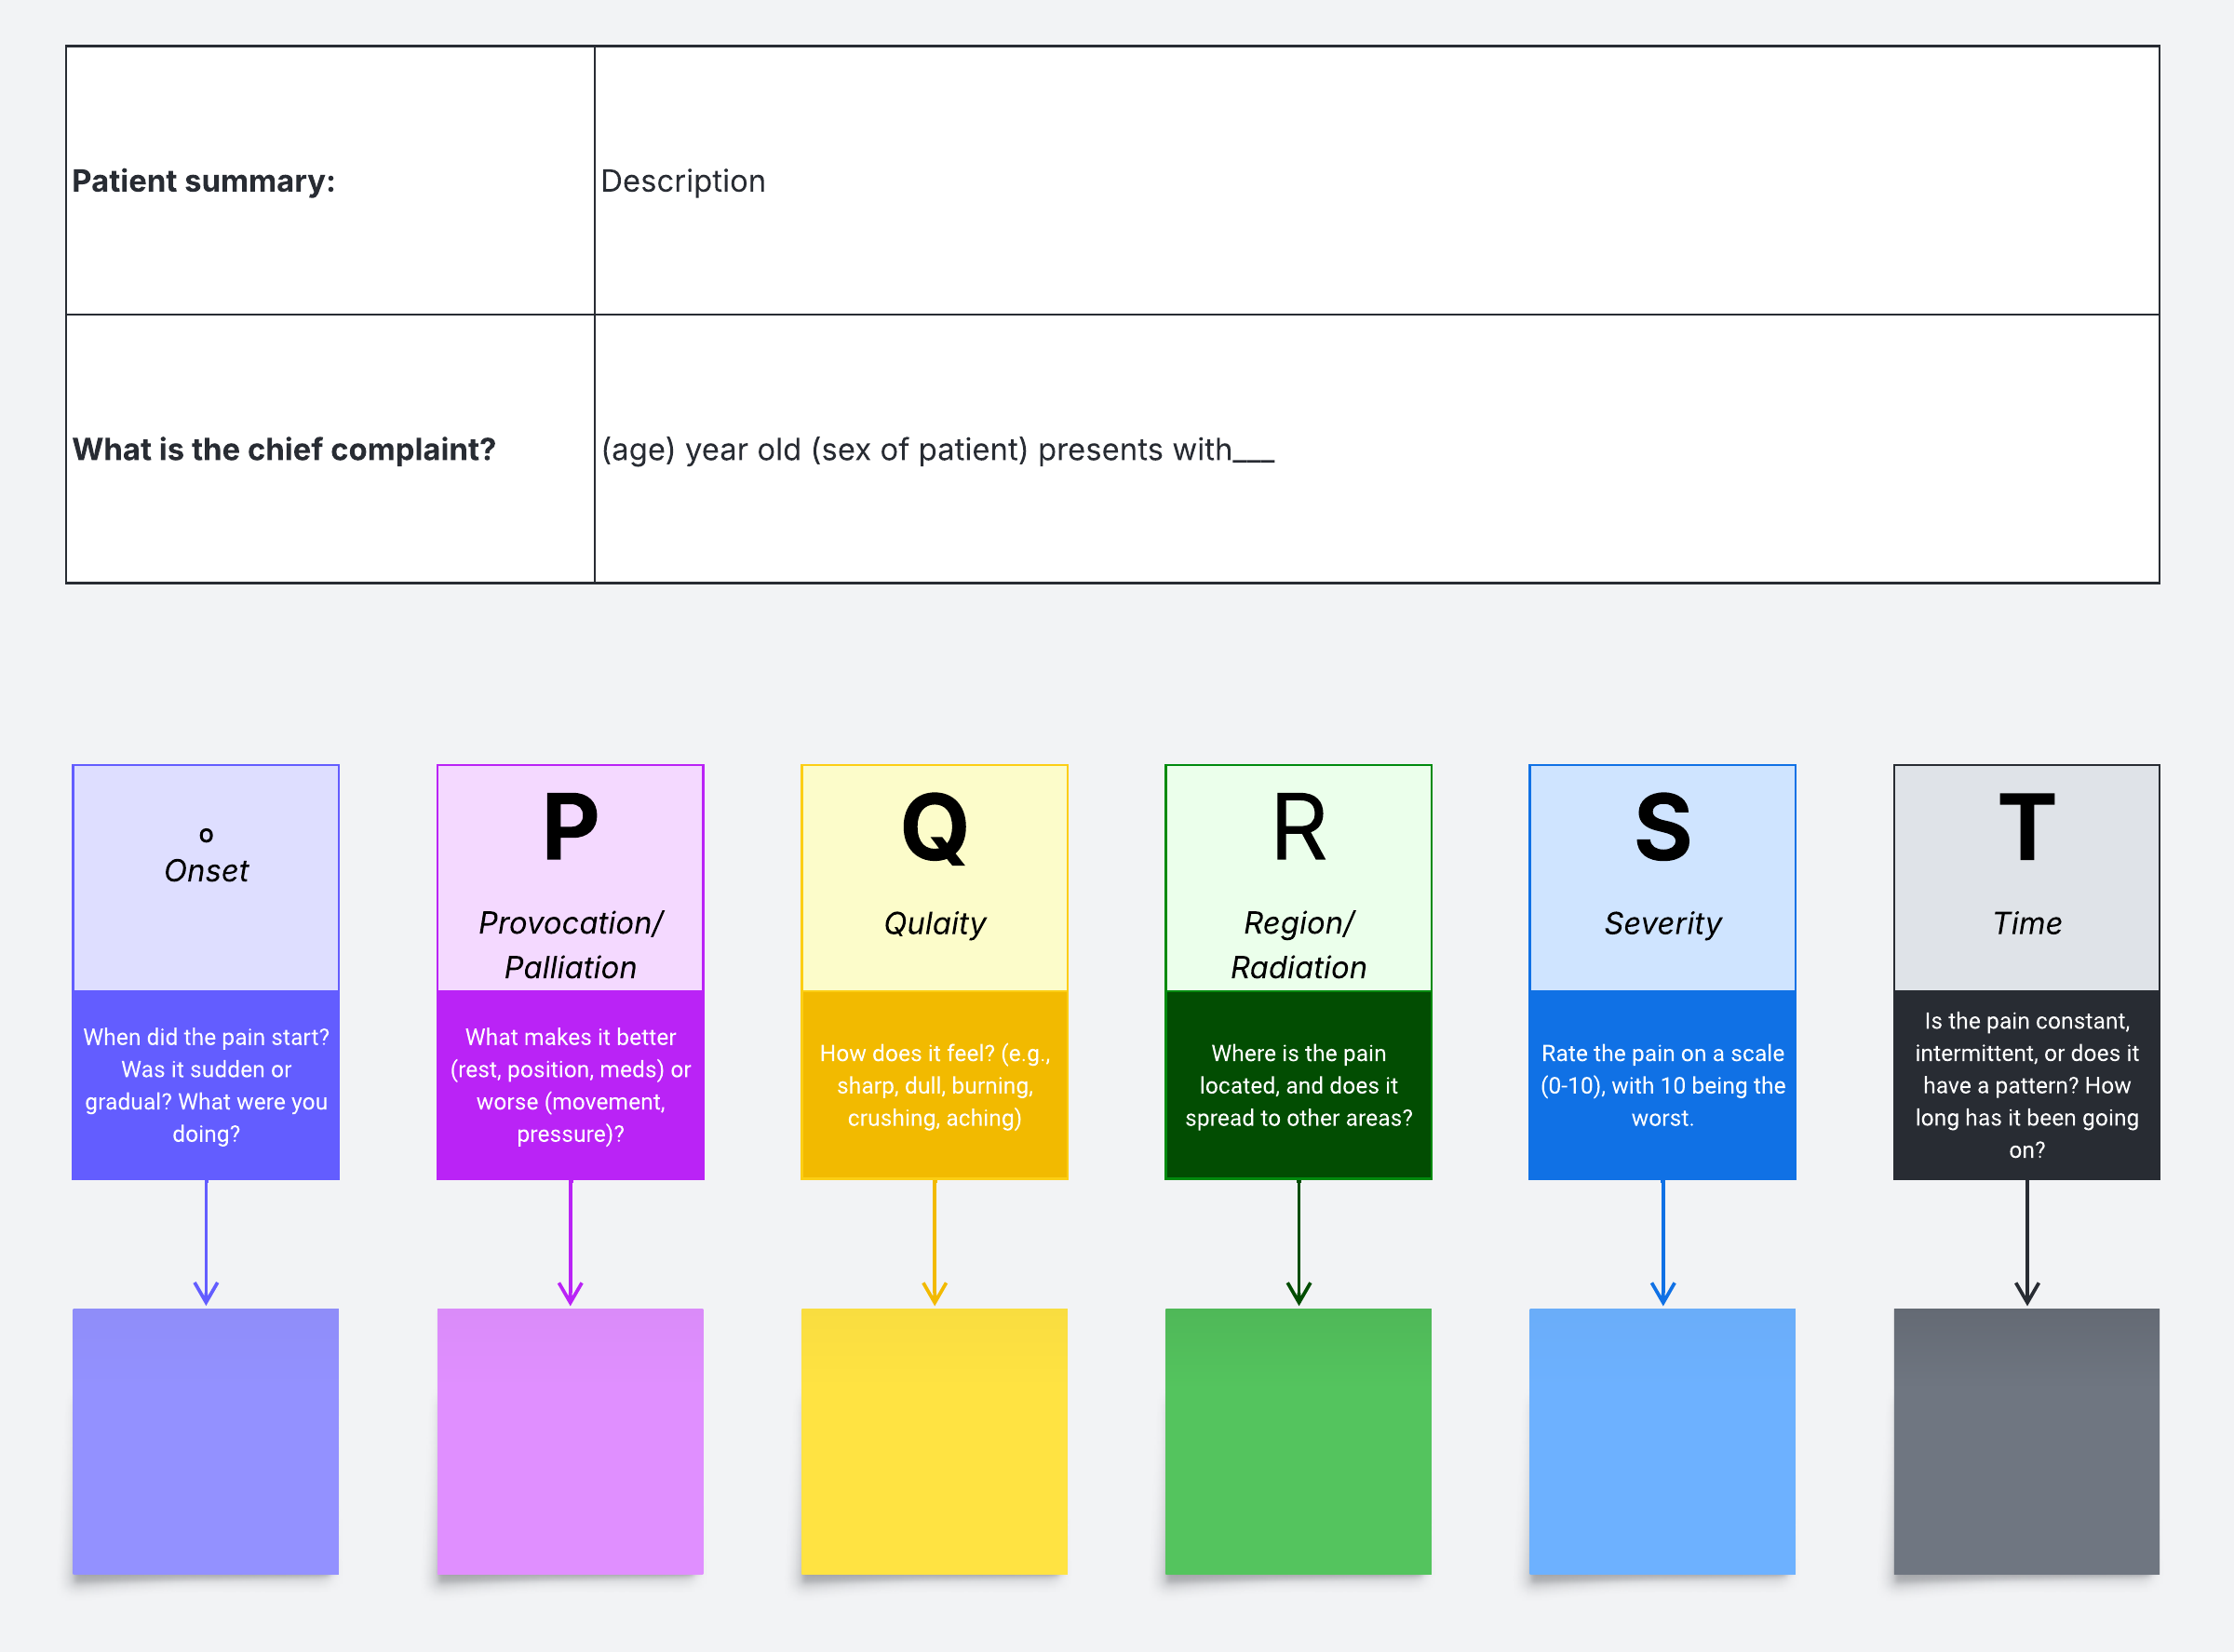
I spent roughly eight years in the emergency department before moving into clinical education. The shift happened because I was tired of watching fresh grads try to assess a chest pain patient by running through a massive checklist while the monitor beeped louder and louder. They knew the algorithm but they couldn't prioritize. That gap is what OPQRST was designed to fill. OPQRST isn't some revolutionary new framework that replaces comprehensive history taking. It's a rapid pain assessment tool. It stands for Onset, Provocation/Palliation, Quality, Radiation/Region, Severity, and Time. When I taught it to residents during my education years, I kept stressing one thing that most textbooks skip: this isn't meant to be read to the patient verbatim. It's a mental structure for you. You're not saying "Okay, let me assess your provocation and palliation factors." You're asking "What makes it better or worse?" while simultaneously noting whether leaning forward helps, or whether movement changes the character of the pain.
Opqrst Unveiled The Ultimate Framework For Rapid Accurate Patient Assessment In Emergency Medicine
The title sounds grandiose, and I get why someone would package it that way for clicks. But here's what actually happens when you use OPQRST correctly in a busy ED. You walk into a trauma bay or a treatment room and within two to three minutes you've categorized the chief complaint enough to start your differential and your workup in parallel. That's the real value. Not the acronym. The speed at which it structures your thinking so you can act. Let me walk through how it works in practice, with actual examples rather than textbook definitions. O — Onset: This is where most people rush. Onset doesn't mean "when did the pain start?" That's Time, not Onset. Onset is about the quality of the beginning. Did it hit like a truck? Did it creep up over hours? A patient who says "I was fine and then it just happened" has a different clinical picture than someone who says "It started as indigestion three days ago and just got worse." The former raises immediate suspicion for something catastrophic — aortic dissection, ruptured aneurysm, pulmonary embolism. The latter is more likely infectious or inflammatory. I remember one night shift where a patient came in with what seemed like straightforward gastritis. His onset had been gradual over four days. I asked the right follow-up questions during the O phase and found he'd had a similar episode six months prior that resolved on its own. That pattern changed everything about how I approached his workup.
P — Provocation/Palliation: This is the most underutilized part of the entire framework. Most clinicians ask "Does anything make it better?" and move on. But the specific things that aggravate or relieve pain are diagnostically powerful. Pleuritic pain that worsens with deep inspiration points toward pulmonary involvement. Pain that improves when the patient lies still and draws their knees up screams peritoneal irritation — think perforated viscus or appendicitis. Conversely, pain that worsens with movement and the patient can't find a comfortable position is more likely musculoskeletal or colicky. I had a case last year involving a 52-year-old female who presented with epigastric pain. She kept saying NSAIDs helped, which initially made everyone think peptic ulcer disease. But during the P assessment, I noted she also felt better leaning forward. That single detail — the positional palliation — shifted my thinking toward pancreatitis or pericarditis. An ECG and lipase ordered based on that observation confirmed acute pericarditis. The NSAID relief was a red herring. Q — Quality: Words matter here. "Sharp" and "stabbing" and "tearing" carry different weights than "dull," "aching," or "cramping." A patient describing their pain as "the worst headache of my life" or "like being stabbed" immediately elevates your urgency level. But quality isn't just about the word choice — it's about whether the description matches the expected pathology. I once worked with a patient who described his chest pain as "a heavy elephant sitting on my chest." Classic anginal description. But he also kept saying it felt "burning" and improved with antacids. The quality mismatch — heavy pressure versus burning — made me order a troponin anyway. It was negative, but the combination of risk factors and the initial quality description warranted it. Don't let palliation alone convince you to skip the workup. R — Radiation/Region: Region is where the pain is. Radiation is where it travels. These are different things and both matter. Gallbladder pain sits in the right upper quadrant but radiates to the right scapula. Renal colic starts in the flank and moves toward the groin. Cardiac pain can radiate to the jaw, the left arm, or neither — and absence of radiation doesn't rule out cardiac origin, especially in women and diabetics. I've seen too many young clinicians miss inferior wall MIs because the patient only complained of epigastric discomfort without any classic radiation. The region was wrong for their mental model of heart attacks. That's a dangerous gap.
Get the Full Details

S — Severity: This is the most controversial component because pain is subjective and numeric scales are imperfect. A 10 out of 10 doesn't always mean 10 times more serious than a 4 out of 10. But severity still has utility, especially when tracked over time. The real question isn't "what number is it?" It's "has it changed?" And more importantly, "what does this level of pain mean for this patient's baseline?" An elderly diabetic woman who rates her pain as a 3 out of 10 with new onset shortness of breath is a much higher risk presentation than a 22-year-old marathon runner who rates a pulled muscle as an 8 out of 10. Severity without context is noise. T — Time: This covers both the duration and the temporal pattern. Is the pain constant? Intermittent? Colicky? Progressively worsening? I've lost count of the number of biliary colic patients who came in saying their pain started "a while ago" and had been coming and going for days. The time component in OPQRST forces you to pin down: hours, days, weeks. A kidney stone patient with colicky pain that comes in waves over 12 hours needs different imaging and different disposition than someone with constant flank pain for three weeks, which might suggest something entirely different like a renal mass or chronic obstruction.
How I Actually Use OPQRST at the Bedside
Here's the thing that no tutorial video will tell you: OPQRST works best when you don't go through it sequentially like a robot. In a real emergency department, you're gathering information from multiple sources simultaneously — the nurse's vital signs, the monitor readings, the patient's appearance, the mechanism of injury if trauma. OPQRST is your organizing framework, not your script. My personal workflow looks like this. I enter the room, observe the patient for five seconds — are they lying still or squirming? Are they diaphoretic? Guarding? That observation alone gives me early clues about Onset and Quality before I even ask the first question. Then I start with a direct question about what brought them in today, which naturally leads into Onset. While they're describing the onset, I'm already thinking about Region and Radiation. I ask about aggravating and relieving factors next, which covers P. I might ask about the character of the pain mid-conversation rather than as a formal question. Severity I usually address after we've established the pattern. Time I circle back to at the end, often confirming what I already have from the triage notes and the patient's own timeline. The whole structured assessment takes me roughly 90 seconds to two minutes for a straightforward case. For a complex trauma or undifferentiated shock patient, it's more like three minutes interspersed with interventions. That's the speed advantage. You're not delaying care to fill out a form. You're using a mental model to organize the chaos.
Common Pitfalls That Beginners Keep Making
I see the same mistakes over and over in trainees and even in attending-level clinicians who haven't updated their approach in years. The biggest one is treating OPQRST as a replacement for a full history and physical. It isn't. It's a rapid assessment tool for the pain component of the chief complaint. If a patient presents with abdominal pain, OPQRST helps you characterize that pain. It doesn't replace the abdominal exam, the lab work, the imaging, or the consideration of non-abdominal causes. I had a resident once who was so focused on getting a perfect OPQRST assessment that she missed a pelvic exam finding in a female patient with abdominal pain. The OPQRST was textbook. The diagnosis was an ectopic pregnancy. The pain assessment was accurate but insufficient. That's a dangerous combination. Another pitfall is anchoring on the first answer. A patient says their pain is "sharp" and you stop thinking about differential diagnoses that present with dull pain. Pain quality can change. A myocardial infarction can present atypically in up to 30 percent of women and 40 percent of elderly patients. Diabetes alters pain perception. Neuropathy changes quality descriptions. Don't let the first quality descriptor close your brain to other possibilities.

The third pitfall is underestimating the Time component. "It's been hurting for two days" is not the same as "It started at 3 AM today and has been constant since." The timeline changes your urgency, your imaging choices, and your disposition decisions. Two days of worsening RUQ pain with fever is cholangitis until proven otherwise. Two days of constant RUQ pain without systemic symptoms is more likely biliary colic or even hepatitis. The difference matters for admission versus discharge.
Where OPQRST Falls Short
I want to be blunt about the limitations because I've seen people treat this framework as a magic bullet and it hasn't served them well. OPQRST is designed for pain assessment. It doesn't help much with non-pain chief complaints. If a patient comes in with shortness of breath, syncope, or altered mental status, you need different frameworks — START for triage, ABCDE for stabilization, different history templates for non-pain presentations. Using OPQRST as a universal assessment tool is like using a screwdriver to hammer a nail. It might work in a pinch, but you're doing it wrong. It also assumes the patient can communicate. For pediatric patients, geriatric patients with dementia, intubated patients, or those with language barriers, OPQRST becomes much harder to apply accurately. I've had to adapt the framework significantly in these populations — using observational proxies for Quality and Severity, relying on caregivers for Onset and Time, and using visual analog scales modified for developmental level when possible. The core structure remains useful, but the application changes.
There's also the cultural and individual variation in pain expression that OPQRST doesn't account for. Some cultures encourage stoicism. Some individuals describe visceral pain as "pressure" rather than "pain" at all. A patient who says "my chest feels tight" during an MI is giving you quality information through OPQRST, but you have to know how to translate that into clinical action.
A Real Edge Case From My Practice
About two years ago, I was covering a late-night shift when a 45-year-old male presented with "upper abdominal discomfort." He rated it as a 4 out of 10, said it had been coming and going for a week, and denied any aggravating factors. His OPQRST assessment looked completely benign. Normal vitals. No radiation. Mild quality. The obvious workup would have been GI-directed. But I noticed something during the assessment that OPQRST itself didn't capture. He kept rubbing his left shoulder while describing the pain. Not the abdomen. The shoulder. I asked him directly about it and he said he'd been attributing it to sleeping funny. That observation — combined with the fact that his discomfort seemed to worsen slightly with each deep breath he took, even though he'd initially denied any respiratory component — pushed me to order an ECG and troponin despite the deceptively mild OPQRST profile. Result: inferior wall MI with pericardial involvement. The shoulder rubbing was referred pain from diaphragmatic irritation. The subtle respiratory variation was pleuritic overlap. None of those findings were captured by a standard OPQRST interview because the framework doesn't explicitly include observation and pattern recognition. That's where clinical experience supplements the mnemonic. OPQRST gets you organized. Your eyes and ears and pattern-matching ability keep you from missing what the framework might overlook.
Practical Application Tips
If you're learning this for the first time, here's what I recommend. Don't memorize the acronym and try to force it onto every patient. Instead, internalize the six categories and practice applying them casually during your assessments. Start with straightforward cases — abdominal pain, chest pain, headache — where the framework fits naturally. Then gradually expand to trickier presentations where the categories overlap or seem incomplete. Use OPQRST alongside other tools, not instead of them. Pair it with vital signs interpretation, physical exam findings, and basic diagnostics. A complete assessment in the emergency department is never just one thing. The framework is one lens, not the entire scope. Practice documenting your OPQRST findings concisely. I've seen colleagues write paragraphs about pain assessment that contain almost no actionable information. "Patient reports pain that is sharp in character, rated 7/10, started suddenly, radiates to the back, worsened by movement, improved slightly with rest" can be condensed to "acute onset sharp RPQ pain, 7/10, radiates to back, worsened by movement." The clinical content is identical. The chart is more useful. Speed in documentation matters when you're managing multiple patients simultaneously.
Finally, teach this to your patients too. When you ask about onset, provocation, quality, radiation, severity, and time, you're not just gathering data — you're engaging the patient in their own assessment. A patient who understands why you're asking about whether the pain changes with position is more likely to give you accurate, detailed information. That collaboration improves the quality of your OPQRST assessment dramatically compared to interrogating a passive subject. The framework isn't ultimate. It isn't perfect. It won't save every patient on its own. But used correctly, in the right context, alongside clinical judgment rather than replacing it, OPQRST is one of the most efficient tools we have for rapid pain assessment in the emergency setting. The real skill isn't knowing the acronym. It's knowing when to apply it, how to adapt it, and when to look beyond it.


