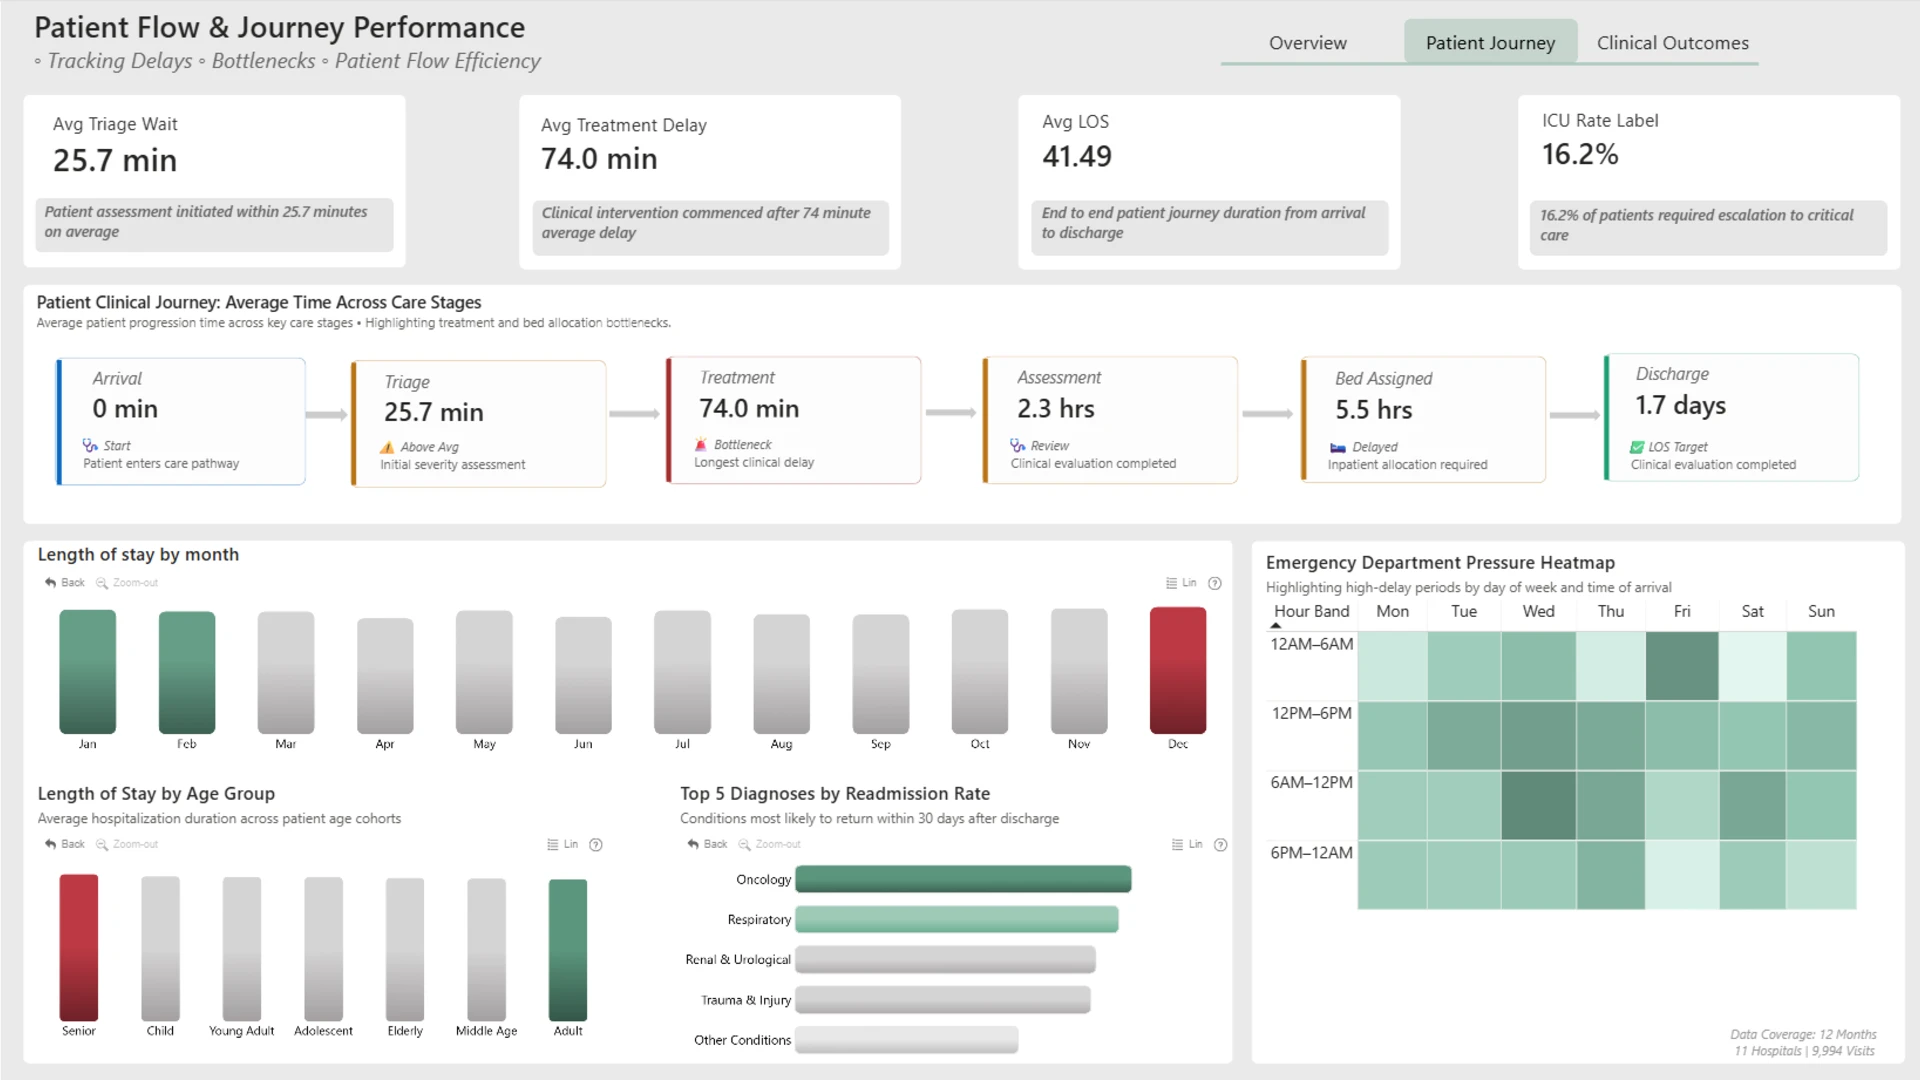
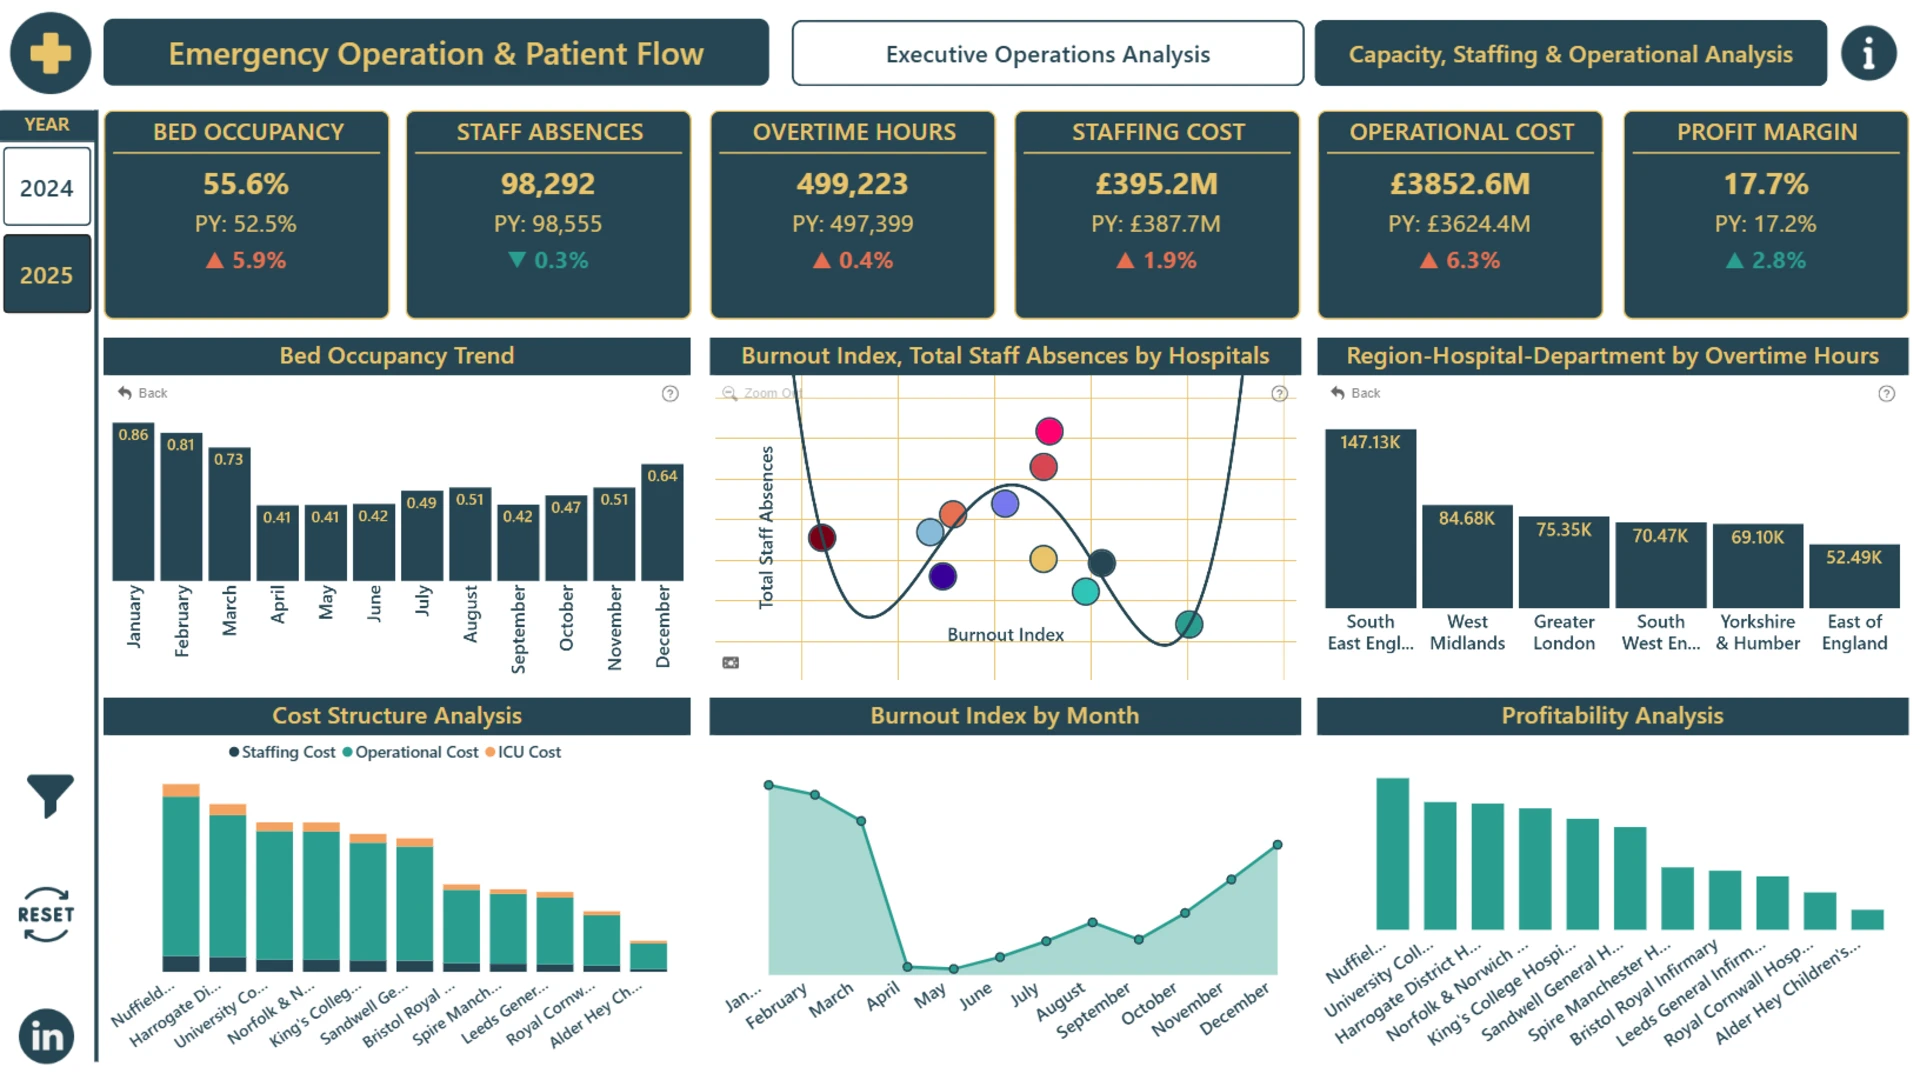
Building a Real-Time OPD and Emergency Dashboard Actually Works, But Most People Break It
I spent about three years dealing with hospital ops dashboards across four different facilities before I figured out the parts that actually matter. What we're looking at here is a system that tracks OPD active calls in real-time, feeds emergency response metrics, and tries to give you a single view of hospital operations. Most implementations fail within six months. I'll explain why and how to avoid that. The core idea is straightforward. You have call queues from the OPD department, ambulance and emergency response timers, bed occupancy numbers, and staff availability. The dashboard pulls all of that together. The reveal part everyone talks about is usually the real-time refresh mechanism. Most places I see use polling every 10 to 30 seconds. That works fine until you have multiple departments feeding data simultaneously, then your database starts choking on concurrent queries. The working approach I ended up using involved a combination of WebSocket pushes for critical emergency data and batched HTTP requests for routine OPD metrics. Emergency call status changes needed sub-3-second latency. OPD queue lengths could tolerate 15 to 20 second refreshes without anyone noticing. Separating those two data flows reduced our database load by roughly 60 percent.
Data architecture matters more than the visual design. I watched a facility in Gujarat invest heavily in fancy animated dashboards while their underlying API layer was making sequential database calls. The result was a dashboard that looked great but showed data that was 45 seconds to 2 minutes stale during peak hours. Peak OPD hours in Indian hospitals typically run from 9 AM to 1 PM and again from 4 PM to 7 PM. Your system needs to handle the surge, not just average load. The technical stack I recommend is not complicated. Node.js or Go for the ingestion layer, a proper message queue like RabbitMQ or even Kafka if your scale demands it, and a time-series database for historical trending alongside your relational database for current state. PostgreSQL with TimescaleDB extension handled our needs without breaking a sweat. Redis for caching the live dashboard state kept response times under 200 milliseconds even during heavy load. One specific problem I ran into that still comes to mind happened during a monsoon season surge. We had a hospital where emergency calls spiked by 340 percent over a two-hour window due to waterlogging across the city. The dashboard's alert threshold was set based on normal operating parameters. Every single alert fired at once. The nursing staff got notification fatigue within 12 minutes and started ignoring them entirely. I had to implement a cooldown and grouping mechanism that bundled related alerts into a single notification with a priority score. It cut false urgency by about 70 percent and actually got the right people looking at the right problems.
Implementation Details That People Skip
Most teams jump straight into building the frontend charts. That is backwards. Start with your data sources and figure out how each piece of information gets into your system. OPD calls come from your telephony or appointment scheduling platform. Emergency calls come from your dispatch system. Bed status comes from your admission-discharge-transfer system. Each of these has different update frequencies and reliability characteristics. Your emergency response timer is the most critical metric on the dashboard. This counts from the moment an emergency call is received to the moment the ambulance departs, and then from departure to patient handover at the facility. I have seen hospitals claim average response times of under 8 minutes when they were actually measuring from call receipt to ambulance arrival at the scene, which is a completely different number. Make sure your definitions are documented and consistent. A difference of 3 to 4 minutes in how you measure can make your metrics look dramatically better or worse depending on which convention you use. OPD active call tracking requires integration with your call management system. If you are using a basic IVR setup, you will need to pull call logs and current queue positions through an API or direct database read. If you have a proper CTI integration, you get real-time call state changes. The gap between these two approaches is massive in terms of dashboard accuracy. IVR-based systems typically have a 10 to 30 second delay between an actual call event and when your dashboard reflects it.
Get the Full Details
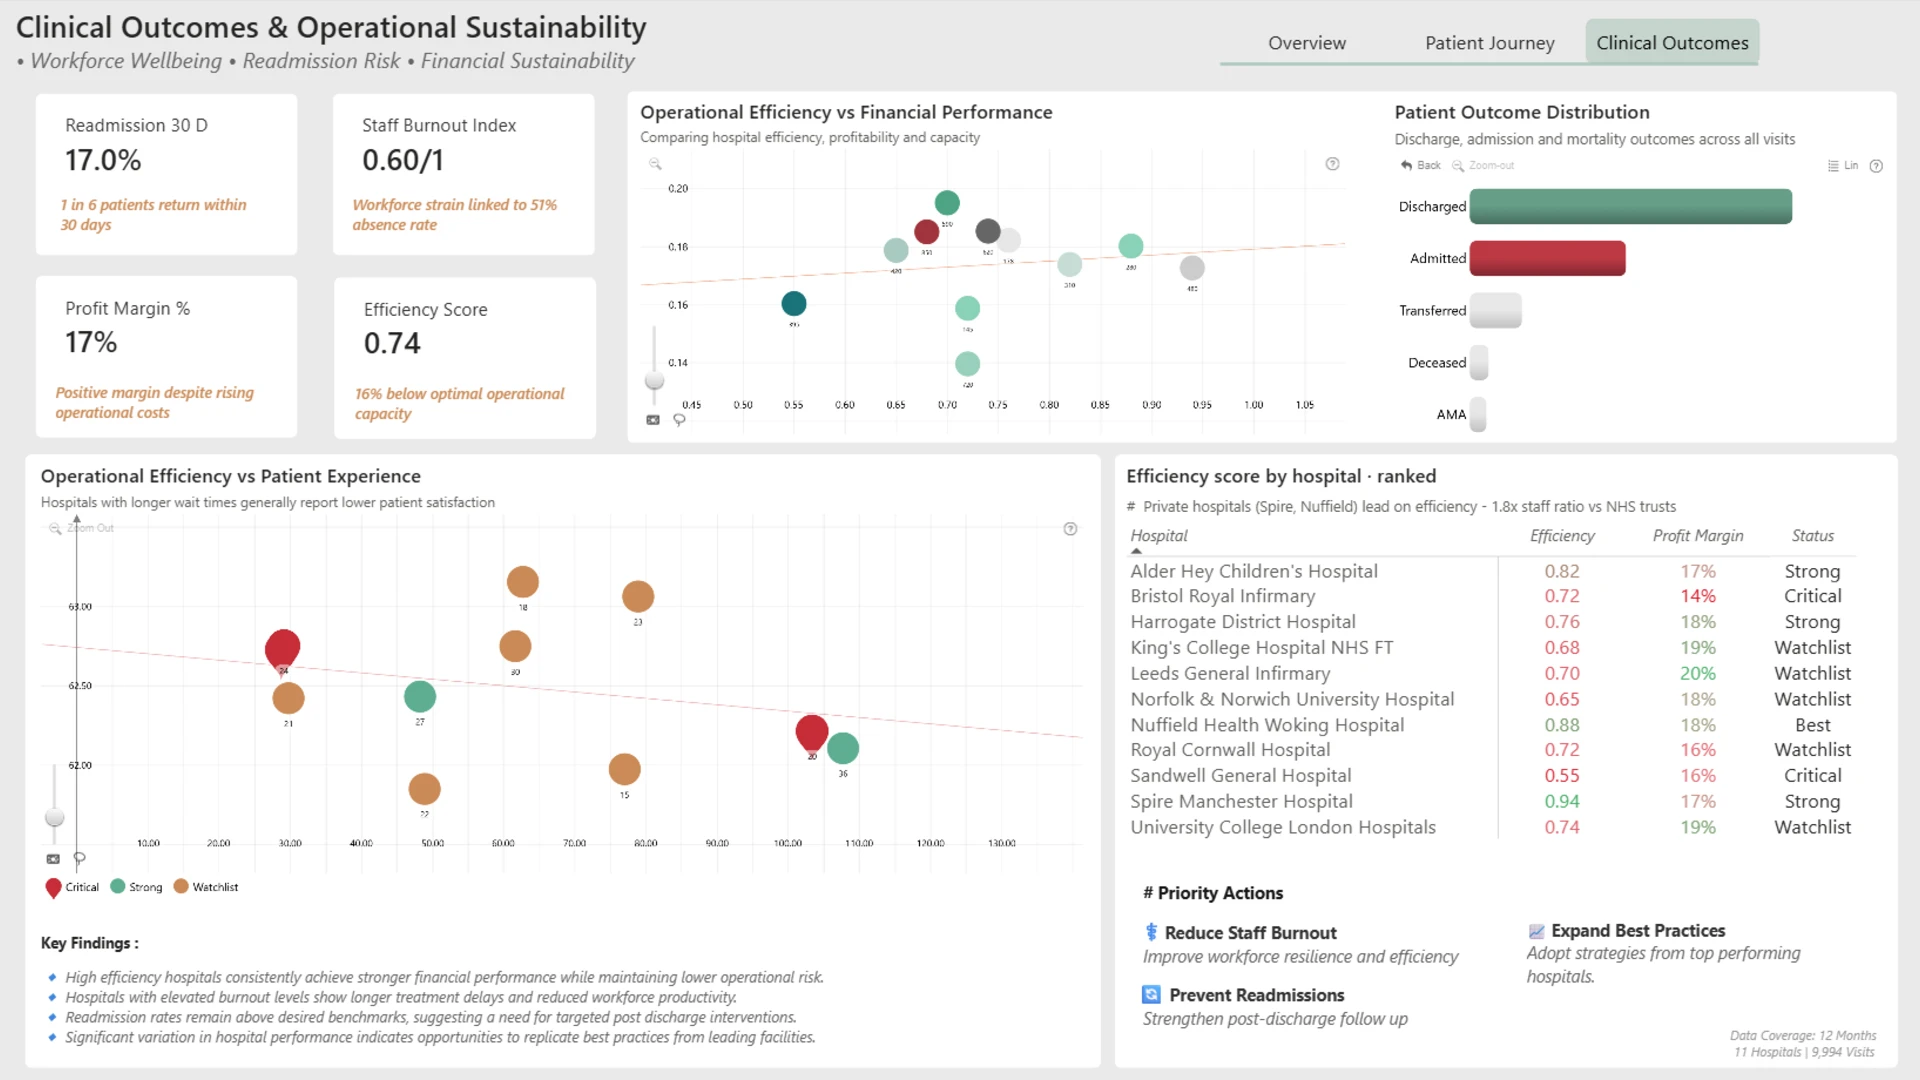
Staff allocation display is another area where people waste time. Showing which doctors are available is useful but only if your availability data is accurate. I saw one implementation where doctor availability was manually updated by the front desk. By the time someone remembered to update it, the information was already 3 to 4 hours old. Automation through your appointment system or a simple check-in checkout flow from your staff mobile app reduced that lag to near zero.
Pitfalls and Where These Systems Break Down
Real-time does not mean instant. Network failures happen. I have had dashboards go blank during power fluctuations because the WebSocket connection dropped and the automatic reconnection logic was not robust enough. Implement exponential backoff with jitter for reconnections. A simple reconnect attempt every 5 seconds will create a thundering herd problem if your entire dashboard infrastructure goes down and comes back up simultaneously. Data consistency across multiple sources is another constant headache. Your OPD system might say a patient is in queue position 3 while your emergency system shows that same patient was brought in via ambulance. These are not necessarily errors. They are different systems capturing different moments in the patient journey. Your dashboard needs to handle and display these discrepancies clearly rather than trying to force a single narrative. A small status indicator showing which system provided which piece of information goes a long way toward preventing confusion during actual emergencies. Security cannot be an afterthought. This dashboard shows real-time operational data that could be misused. I have seen facilities put these dashboards on public-facing screens in lobbies without proper access controls. Limit dashboard access to authenticated users on the internal network. If you need external access for administrators, use a VPN or a separate isolated network segment. Patient data on this dashboard should never be visible in raw form. Aggregate and anonymize.
The cost reality is that a properly built system of this type runs between 8 to 15 lakhs for a mid-size hospital implementation, excluding ongoing maintenance. The biggest hidden cost is not the software. It is the integration work with your existing hospital management system, telephony platform, and emergency dispatch software. Each integration point adds 2 to 4 weeks of development and testing. Plan your timeline accordingly. A 6-month project timeline is realistic for a full deployment with proper integration. Anything claiming 8 weeks is cutting corners that will cost you later. Download links and ready-made packages exist but I would approach them with caution. Most off-the-shelf hospital dashboard solutions are built for generic use cases and do not handle the specific integration requirements of Indian hospital workflows. The OPD call management patterns, emergency triage classifications, and reporting formats are quite different here compared to Western systems. If you do use a base package, budget 40 to 60 percent of your total project cost for customization and integration work. The metrics that actually move the needle are call abandonment rate in OPD, average emergency response time from dispatch to arrival, bed turnover time, and staff-to-patient ratio during peak hours. Everything else on the dashboard is nice to have but will not change how your hospital operates. I have seen teams spend weeks building beautiful visualizations for metrics that nobody checks after the first month. Start with the four metrics above and add complexity only when you have a clear reason for it.