How Omeprazole Actually Works When You Take It Seriously
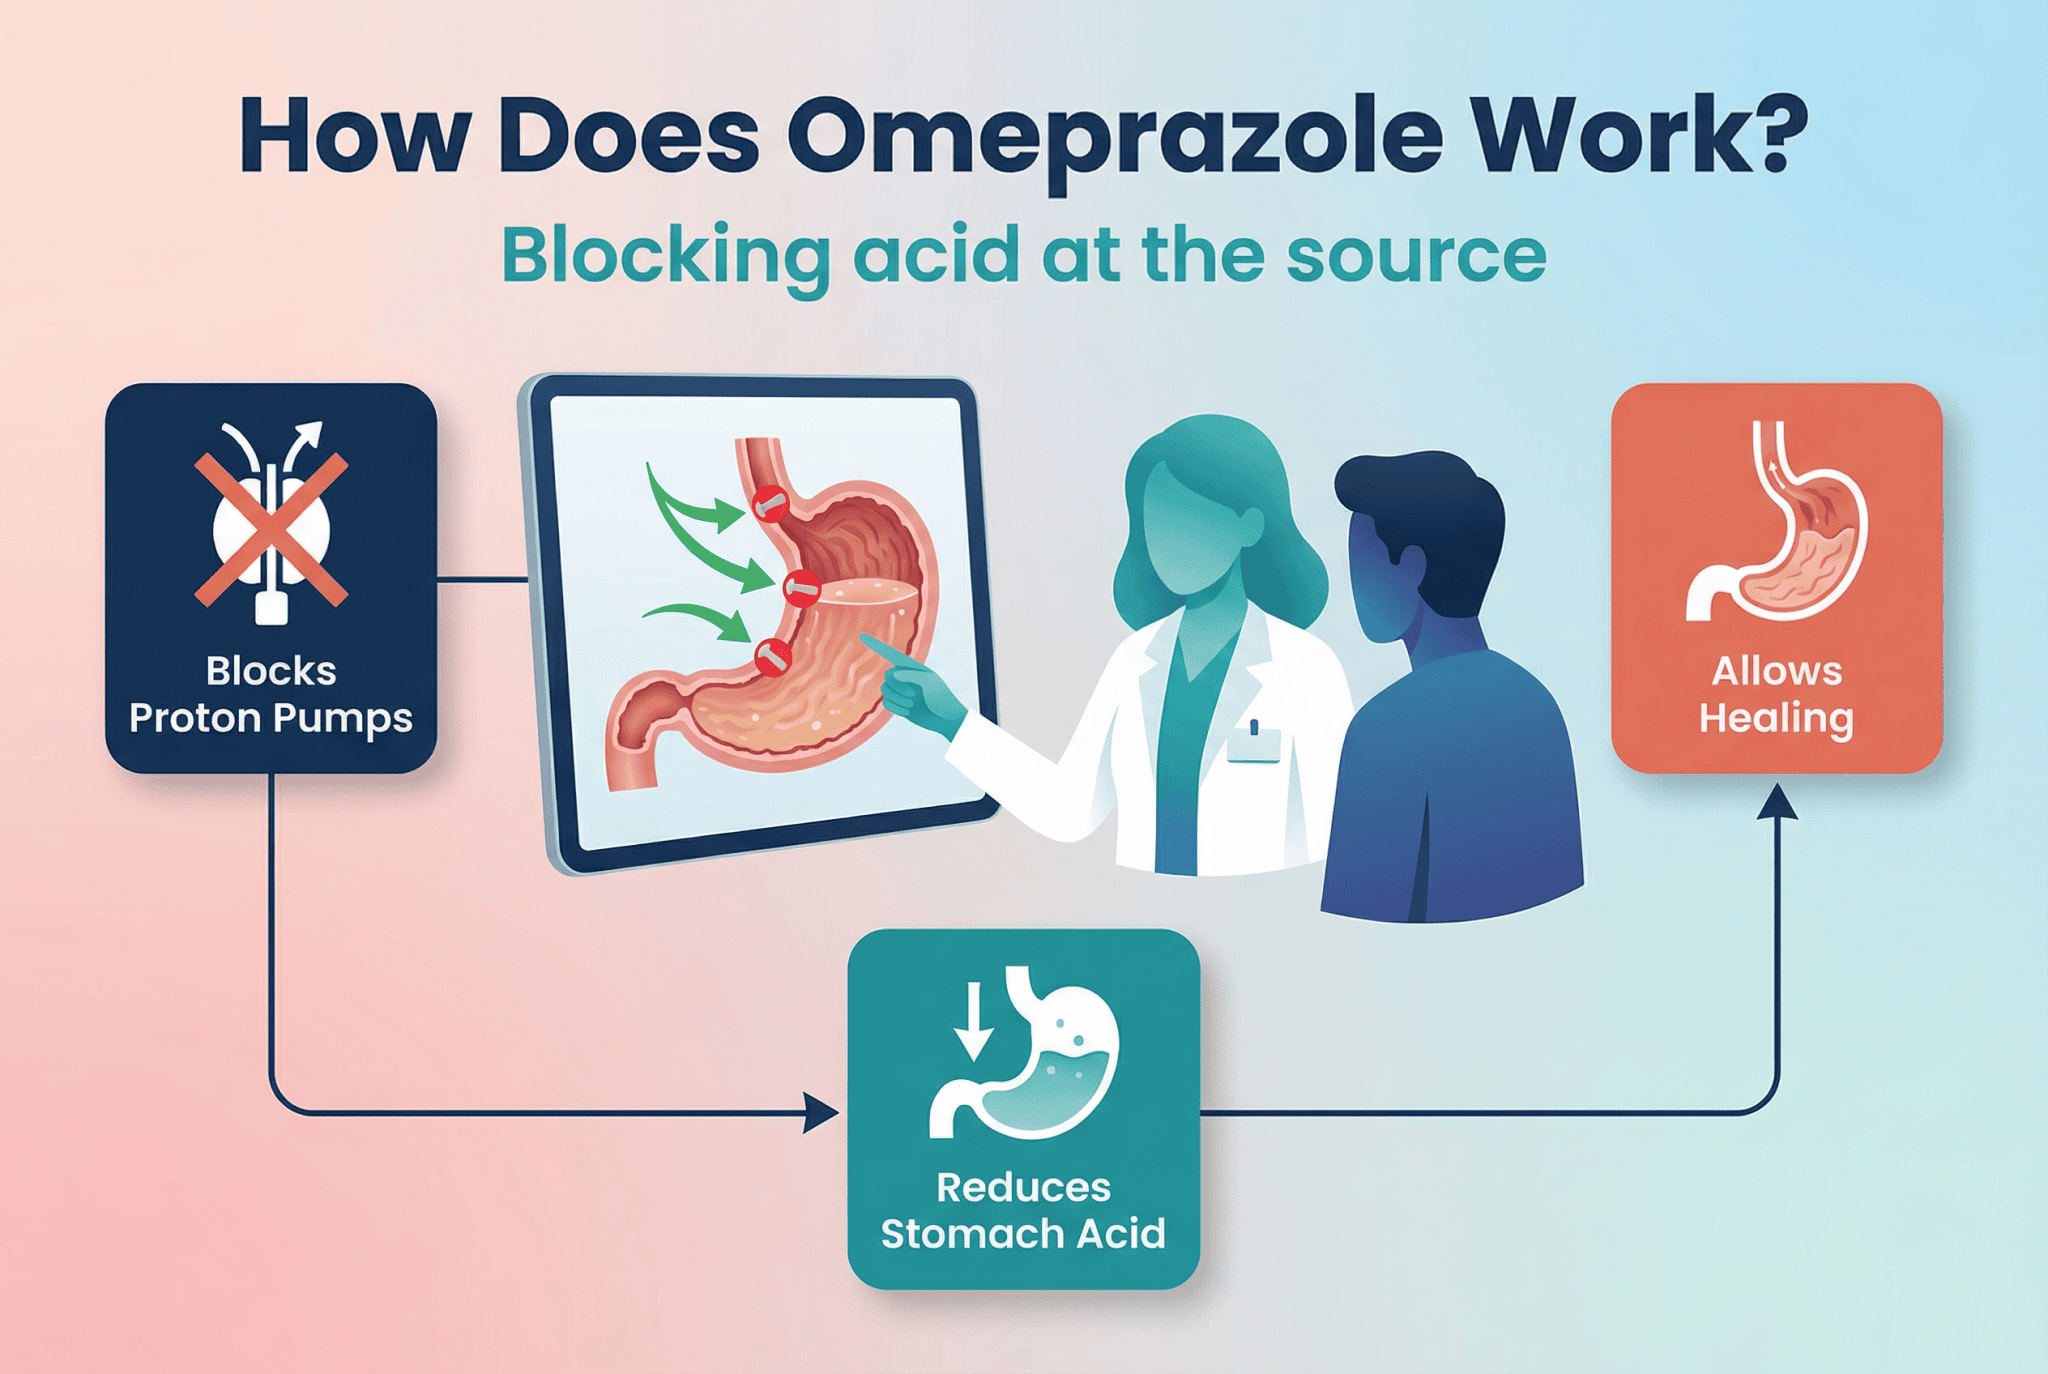
Omeprazole is a proton pump inhibitor. It shuts down the H+/K+ ATPase enzyme in your stomach's parietal cells. That enzyme is the final step in acid production, so blocking it reduces gastric acid output by roughly 90 to 95 percent. That's why it works better than antacids or H2 blockers for most people with persistent reflux. Antacids neutralize acid already in the stomach. Omeprazole stops the acid factory from running in the first place. I've been managing GERD off and on for years, and I learned the hard way that omeprazole has a specific administration window that most people ignore. The drug needs an acidic environment to dissolve properly because it's enteric-coated. If you take it with a large meal or right after eating, the pill sits in a pH-neutral or alkaline stomach and doesn't break down at the right time. I was taking it after dinner every night for months and wondering why my breakthrough symptoms were getting worse. My gastroenterologist explained that the pill should be taken on an empty stomach, ideally thirty to sixty minutes before your first meal of the day. I switched to morning dosing before breakfast and my daytime heartburn dropped dramatically within a week. Another thing people don't tell you: omeprazole doesn't work immediately. It takes about three to five days of consistent dosing to reach steady-state suppression because you have to inhibit enough proton pumps before you feel relief. Some people take it once, feel nothing, and stop. That's not how the drug works. You need to give it a proper trial period of at least fourteen days at the standard over-the-counter dose of twenty milligrams once daily before judging whether it's effective for you.
There are also interaction issues worth knowing. Omeprazole inhibits the CYP2C19 enzyme, which means it can raise the blood levels of certain medications like clopidogrel, diazepam, and warfarin. If you're on any of those, talk to your doctor before starting omeprazole. It can also reduce absorption of medications that require an acidic environment to dissolve, like ketoconazole and iron supplements. I found that out when my routine iron panels started looking worse despite no change in diet. Taking my iron supplement two hours apart from omeprazole fixed the issue.
The Real Limitations Nobody Talks About
Omeprazole is effective, but it's not a permanent fix. The standard OTC course is limited to fourteen days, repeated no more often than every four months, because long-term use carries real risks. Studies have linked prolonged PPI use to increased rates of C. difficile infection, magnesium deficiency, bone density loss, and potentially kidney issues. The risk isn't massive for most people, but it exists, and it grows the longer you stay on the drug. Rebound acid hypersecretion is another issue I ran into myself. After finishing a fourteen-day course, my acid production spiked back above baseline for about a week. This happens because your stomach's ECL cells upregulate gastrin release in response to the prolonged acid suppression, and when the drug clears, your body overcorrects. I solved this by tapering: switching to an H2 blocker like famotidine for a few days instead of stopping cold turkey, then tapering that off as well. It wasn't perfect, but the rebound was much milder than if I'd just stopped. Also worth noting: omeprazole does not heal an already damaged esophagus faster than other PPIs. It's the prototypical PPI, but esomeprazole and pantoprazole do essentially the same thing. If you're paying out of pocket, compare prices. Generic omeprazole is usually the cheapest option by a wide margin, and it's bioequivalent to the branded versions for most patients. I switched from brand-name Prilosec to the generic and saved about sixty dollars a year with no difference in symptom control.
Get the Full Details

If your symptoms don't improve after two weeks of proper dosing, or if you need to run courses repeatedly without relief, that's a signal to see a doctor rather than self-managing further. Persistent acid symptoms can indicate a hiatal hernia, Barrett's esophagus, or another condition that omeprazole alone won't address. The drug is a management tool, not a diagnostic endpoint.